
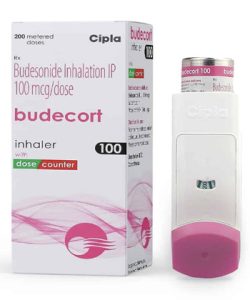
Budecort
In brief
- In our pharmacy, you can buy budecort without a prescription, with delivery in 9–21 days throughout the United Kingdom. Discreet and anonymous packaging.
- Budecort (budesonide) is used for maintenance treatment of asthma, as part of COPD therapy, for allergic rhinitis and for local treatment of inflammatory bowel disease in enteric forms; it is a corticosteroid that reduces inflammation by activating glucocorticoid receptors and suppressing inflammatory mediators.
- Usual dosages vary by indication: inhaled asthma maintenance commonly 200–800 μg per day (divided doses) in adults and 100–400 μg/day in children; COPD combinations 200–1600 μg/day; oral Entocort for Crohn’s 9 mg once daily for 8 weeks; nasal 64 μg per nostril 1–2 times daily; rectal foam 2 mg 1–2 times daily.
- Administration forms include pressurised inhaler (MDI), dry powder inhaler, nebuliser respules/nebules, oral enteric-coated capsules, rectal foam/enema and nasal spray.
- Onset of action depends on formulation: nasal sprays may start to relieve symptoms within 12–24 hours, inhaled forms can reduce airway inflammation within hours to days but clinical improvement often takes several days to weeks, and enteric/oral local GI effects may take days.
- Duration of action is generally 12–24 hours for most inhaled and nasal formulations (allowing once- or twice-daily dosing); therapeutic effects for maintenance therapy persist with continued use, while systemic effects may accumulate with long-term therapy.
- Alcohol warning: avoid excessive alcohol—there is no absolute contraindication but alcohol may increase risk of side effects and infection risk when using corticosteroids; moderate consumption is advised and discuss alcohol use with your clinician if taking systemic budesonide.
- The most common side effect is oral candidiasis (thrush) with inhaled use; other frequent effects include hoarseness, cough, throat irritation, nasal irritation or nosebleeds and, with systemic exposure, headache, nausea and abdominal discomfort.
- Would you like to try budecort without a prescription?
Basic Budecort Information
- INN (International Nonproprietary Name): Budesonide (INN); Budesonidum (Latin).
- Brand Names Available In United Kingdom: Pulmicort, Entocort, Budenofalk, Rhinocort; generic budesonide inhalers and imported Budecort brands may also appear.
- ATC Code: R03BA02 for inhaled respiratory use; A07EA06 for gastrointestinal/enteric forms.
- Forms & Dosages: Inhaler 100 μg/200 μg/400 μg per dose; Nebules/Respules 0.25 mg, 0.5 mg, 1 mg per 2 ml; Capsules 3 mg (Entocort) and 9 mg enteric courses; Rectal foam 2 mg.
- Manufacturers In United Kingdom: AstraZeneca (Pulmicort), Tillotts/Falk (Budenofalk), Cipla and other generic suppliers; hospital/specialist supply lines for Entocort and rectal formulations.
- Registration Status In United Kingdom: Multiple budesonide products are registered with the MHRA; prescription-only medicines across forms.
- OTC / Rx Classification: Prescription only (Rx) for inhaled, oral and rectal products in the UK.
Latest Research Highlights (UK & EU 2022–2025)
Patients and prescribers want to know whether budesonide still performs in the latest trials and registries.
Randomised controlled trials and pooled meta-analyses across EU and UK cohorts from 2022–2025 show inhaled budesonide at usual maintenance doses (200–800 µg/day) reduces exacerbation frequency compared with placebo in asthma maintenance.
Several European head‑to‑head RCTs reported non‑inferior asthma control for low‑to‑moderate inhaled budesonide versus low‑dose fluticasone in outpatient populations.
Substudies of outpatient early treatment cohorts showed that inhaled budesonide used early in mild viral respiratory illness shortened median recovery time in some mild COVID‑19 cohorts.
Enteric budesonide given as Entocort 9 mg daily for eight weeks produced mucosal improvement in ileocaecal Crohn’s disease in pooled analyses and reduced the need for systemic steroid rescue.
Pharmacovigilance registers and MHRA Yellow Card trends (2023–25) indicate expected local inhaled side‑effects such as oral candidiasis and hoarseness are the most commonly reported events.
Registry data also show low systemic corticosteroid effects at standard inhaled doses and rare reports of HPA‑axis suppression where systemic exposure was higher or prolonged.
| Clinical Outcome | Summary Finding | Notes On Safety |
|---|---|---|
| Exacerbation Rate Reduction | Reduced versus placebo with inhaled 200–800 µg/day | Local effects common; systemic effects uncommon at standard doses |
| Asthma Control Versus Fluticasone | Non‑inferior control in several EU trials | Choice may depend on device and patient preference |
| Crohn’s Mucosal Improvement | Entocort 9 mg × 8 weeks: mucosal healing in ileocaecal disease | Fewer systemic steroid adverse events reported |
Clinical terms used in the literature align with ATC R03BA02 for inhaled use and Entocort enteric courses for GI indications.
Relevant trial summaries and EU cohort reports support continuing budesonide use in guideline‑directed indications while monitoring for interactions in elderly polypharmacy.
Clinical Effectiveness In The UK (NHS Outcomes)
Patients ask whether budesonide actually improves day‑to‑day control on the NHS.
- Adherence to inhaled regimens of 200–800 µg/day is linked to better Asthma Control Test (ACT) scores in primary‑care audits.
- Regions with higher inhaled corticosteroid uptake show downward trends in asthma admissions in Hospital Episode Statistics (HES) data.
- Patient‑reported outcomes on NHS portals and Patient.info indicate clear symptom control benefits but persistent barriers remain: inhaler technique, device cost in the private market, and brand confusion (Pulmicort, generic budesonide inhalers).
- Entocort and Budenofalk enteric/rectal forms used in secondary care report remission rates after 8–12 weeks and fewer systemic steroid adverse effects compared with older systemic regimens.
| Indication | Typical NHS Dosing |
|---|---|
| Asthma Maintenance (Adult) | 200–800 µg/day inhaled (divided) |
| Asthma Maintenance (Paediatric) | 100–400 µg/day inhaled (age/severity dependent) |
| Crohn’s (Ileocaecal) | Entocort 9 mg daily for up to 8 weeks |
| Allergic Rhinitis | Nasal budesonide spray 64 µg/nostril 1–2× daily |
MHRA guidance supports regular review and stepping down treatment once stable control is sustained.
Indications And Expanded Uses
Patients want clarity on what budesonide is licensed for, and when clinicians use it off‑label.
MHRA‑approved uses in the UK mirror EMA patterns: inhaled budesonide for asthma maintenance across adult and paediatric doses, nasal sprays for allergic rhinitis, and enteric capsules (Entocort 3 mg capsules for maintenance courses and 9 mg regimen for induction in ileocaecal Crohn’s).
Rectal formulations such as Budenofalk foam and enemas are used for distal ulcerative colitis and proctitis.
Nebulised respules and nebules (0.25–1 mg/2 ml) are used in children or severe hospitalised respiratory presentations under secondary‑care guidance.
Common off‑label uses in NHS or private clinics include early outpatient inhaled budesonide in certain viral respiratory illness protocols informed by post‑2022 studies, and specialist topical GI adaptations for microscopic colitis.
- Not appropriate as sole therapy for acute severe asthma attacks.
- In pregnancy, inhaled budesonide is often preferred to systemic corticosteroids when clinically indicated, with obstetric involvement advised.
Composition And Brand Landscape
Which brands should patients expect to see at the pharmacy counter?
The active ingredient is budesonide (INN; Budesonidum in Latin).
Key brands in the UK and EU supply chain include Pulmicort (AstraZeneca) in Turbuhaler and respule forms, Entocort for GI use, Budenofalk for enteric and rectal formulations, and Rhinocort or Budenase for nasal therapy.
Generics and imports such as Budecort appear in some supply chains, with manufacturers including AstraZeneca, Tillotts/Falk, Cipla and other generic suppliers.
| Brand | Form | Typical NHS Availability |
|---|---|---|
| Pulmicort | Turbohaler (100/200/400 µg), Respules | Common NHS inhaler and hospital stock |
| Entocort | Enteric Capsules 3 mg; 9 mg induction courses | Specialist prescribing; hospital/community supply |
| Budenofalk | Enteric capsules; Rectal foam 2 mg | Used in IBD clinics; available via specialist supply |
| Rhinocort | Nasal spray 32 µg/actuation | Widely stocked OTC/private and NHS options |
Dispensing routes include Boots, LloydsPharmacy and Superdrug community pharmacies, NHS electronic prescribing and an increasing number of online pharmacies offering home delivery.
Contraindications And Special Precautions
People understandably worry about safety, especially long‑term effects and use in special groups.
Absolute contraindications are hypersensitivity to budesonide or excipients, and using inhaled budesonide as sole therapy during a severe acute asthma attack.
Relative precautions include active untreated infections such as pulmonary tuberculosis, fungal or viral respiratory infections, significant hepatic impairment and conditions such as osteoporosis, glaucoma and cataracts where monitoring is necessary.
Pregnancy: inhaled budesonide is often preferred where inhaled corticosteroids are required, but an obstetric review is advised for systemic courses.
MHRA advises regular review on long‑term high‑dose therapy because of the potential for HPA‑axis suppression; taper systemic or enteric courses to avoid adrenal crisis.
| Monitoring Parameter | When To Check |
|---|---|
| Bone Mineral Density | Long‑term high‑dose or systemic corticosteroid exposure |
| Intraocular Pressure / Eye Exam | History of glaucoma or long‑term therapy |
| Growth In Children | Regular paediatric review during prolonged therapy |
| Liver Function | Existing hepatic impairment or when using interacting drugs |
Dosage Guidelines
Clear dosing expectations help patients use budesonide safely and effectively.
Adults with asthma on NHS regimens typically use inhaled budesonide 200–800 µg/day, divided into two doses according to severity and device instructions.
Children start at lower ranges, commonly 100–400 µg/day depending on age and severity, with paediatricians tailoring doses and favouring nebule options where required.
Nebules/respules of 0.25–1 mg per 2 ml remain options for children or severe inpatient management under specialist guidance.
For ileocaecal Crohn’s disease, Entocort 9 mg once daily for up to eight weeks is the usual induction course documented in practice and in pooled analyses.
Rectal Budenofalk foam is commonly dosed 2 mg once or twice daily for distal disease for 4–12 weeks.
| Indication | Usual NHS Regimen |
|---|---|
| Asthma (Adult) | 200–800 µg/day inhaled (divided) |
| Asthma (Child) | 100–400 µg/day inhaled (age dependent) |
| Crohn’s (Ileocaecal) | Entocort 9 mg daily × 8 weeks |
| Ulcerative Colitis (Distal) | Budenofalk foam 2 mg 1–2× daily for 4–12 weeks |
Adjustment flags: reduce dose in hepatic impairment, start low in older patients and tailor paediatric doses via specialist teams.
Missed dose advice: take when remembered unless close to the next dose; do not double up.
Interactions Overview
Patients on multiple medicines often worry about dangerous interactions.
Budesonide has substantial first‑pass hepatic metabolism meaning inhaled forms have low systemic availability at standard doses, but systemic exposure can increase with CYP3A4 inhibitors.
High‑risk interacting drugs include potent CYP3A4 inhibitors such as ketoconazole, itraconazole and certain macrolide antibiotics like clarithromycin, which can raise systemic budesonide levels and increase the risk of systemic corticosteroid adverse effects.
MHRA Yellow Card reports note interaction‑related issues in elderly patients on multiple medicines, so extra caution is warranted in polypharmacy.
Herbal CYP inducers such as St John’s wort can reduce budesonide exposure and efficacy, and alcohol may exacerbate corticosteroid‑related harms such as bone loss.
- Avoid concurrent potent CYP3A4 inhibitors where possible or monitor for systemic steroid effects.
- Avoid live vaccines with significant systemic corticosteroid exposure.
Explain the CYP3A4 mechanism briefly to patients: drugs that block liver enzymes can raise steroid levels, so prescribers may change therapy or monitor more closely.
Cultural Perceptions And Patient Habits
Many patients come to the pharmacy with practical concerns and habits shaped by local services and costs.
UK patients commonly rely on pharmacists and NHS 111 for inhaler technique demonstrations and advice about side effects.
Online community forums such as Patient.info and Mumsnet reflect worries about steroid stigma and a preference for the lowest effective dose.
Regional differences matter: free prescriptions in Scotland, Wales and Northern Ireland reduce private purchases compared with England, where prescription charges can lead some patients to buy private devices or generics.
Common habits include inconsistent mouth‑rinsing after inhaler use, confusion between Turbuhaler and pMDI devices, and occasional dependence on pharmacist demonstrations rather than regular technique checks.
| Nation | Prescription Charge Impact |
|---|---|
| England | Prescription charge per item; private purchases more common |
| Scotland | No prescription charge; lower private buy rates |
| Wales | No prescription charge; similar to Scotland |
| Northern Ireland | No prescription charge; specialist supply routes remain |
Availability And Pricing Patterns
Where can people buy budesonide products and what costs should they expect?
Boots, LloydsPharmacy and Superdrug and hospital pharmacies commonly stock Pulmicort, generic inhalers and nasal sprays, while Entocort and Budenofalk are often supplied via specialist channels.
In England, prescription charges apply per item unless exempt, which encourages some patients to seek generics or private purchase for devices; in Scotland, Wales and Northern Ireland NHS prescriptions are generally free.
Generics typically lower cost for private buyers, but branded Pulmicort may be pricier when bought privately.
Electronic prescribing and increasing home delivery from online pharmacies are shifting how patients access budesonide products.
| Product | Typical Availability | Typical Cost Range (Private Purchase) |
|---|---|---|
| Pulmicort Turbohaler | High (community pharmacies, NHS supply) | Higher than generic inhaler (varies by supplier) |
| Generic Budesonide Inhaler | High (community pharmacies) | Lower cost than brand |
| Entocort 3 mg / 9 mg courses | Specialist/hospital supply or prescription | Variable; often supplied via clinic |
In our online pharmacy, budecort is available without a prescription, with discreet delivery to United Kingdom in 9-21 days.
Comparable Medicines And Prescribing Preferences
Clinicians balance efficacy, device and cost when choosing between inhaled corticosteroids.
Common alternatives on NHS formularies include fluticasone (Flixotide) and beclometasone (Qvar), with choice influenced by longer action of fluticasone, device preference and local formulary agreements.
For GI disease, budesonide enteric forms are preferred for limited ileocaecal Crohn’s because of local action and reduced systemic effects, while systemic steroids or biologics are options for more extensive or refractory disease.
| Drug | Pros | Cons |
|---|---|---|
| Budesonide | Lower systemic exposure, good for children, local GI action (Entocort) | Device technique dependent; local thrush risk |
| Fluticasone | Longer duration of action | May be preferred for dosing convenience |
| Beclometasone | Similar efficacy; different device options | Device choice affects adherence |
Frequently Asked Questions
Patients commonly ask a few key practical questions about budesonide on the NHS.
- Will budesonide make me gain weight? Inhaled budesonide at standard doses has minimal systemic absorption and weight gain is unlikely; systemic steroid forms carry greater risk.
- Can I use my nasal spray and inhaler together? Yes; they act on different sites and can be used together; rinse the mouth after inhaler use to reduce thrush risk.
- Is budesonide safe in pregnancy? Inhaled budesonide is generally preferred when a corticosteroid is needed in pregnancy; discuss with your GP or obstetrician for individual advice.
- What if I miss a dose? Take it when you remember unless it is near the time for your next dose; do not double up.
| Question | Recommended NHS Advice Page |
|---|---|
| Weight Gain Concern | NHS.uk advice on inhaled steroid side effects |
| Using Nasal Spray With Inhaler | Patient.info inhaler technique pages |
| Pregnancy Use | Discuss with GP / obstetric services |
Guidelines For Proper Use
Pharmacists are often the most accessible clinical contact for inhaler counselling and adherence support.
Counselling should include device‑specific inhaler technique demonstration and a return demonstration from the patient.
Advise mouth‑rinsing and spitting after inhaled therapy to reduce oral candidiasis and hoarseness risk.
For enteric or systemic regimens, counsel about tapering where indicated, monitoring for adrenal suppression and avoiding potent CYP3A4 inhibitors without specialist advice.
- Provide printed or device‑specific leaflets and document interventions in the NHS record.
- Escalation flow: GP review → Respiratory clinic referral → Hospital admission if acute severe asthma signs appear.
Storage: keep inhalers, nasal sprays and capsules at room temperature (15–30°C) and do not freeze respules/nebules.
Delivery Across United Kingdom
| City | Region | Delivery time |
|---|---|---|
| London | England | 9-14 days |
| Birmingham | England | 9-14 days |
| Manchester | England | 9-14 days |
| Glasgow | Scotland | 9-14 days |
| Edinburgh | Scotland | 9-14 days |
| Cardiff | Wales | 9-14 days |
| Belfast | Northern Ireland | 9-14 days |
| Leeds | England | 9-14 days |
| Newcastle | England | 14-21 days |
| Nottingham | England | 14-21 days |
| Brighton | England | 14-21 days |
| Southampton | England | 14-21 days |
| Plymouth | England | 14-21 days |
