
Buspirone
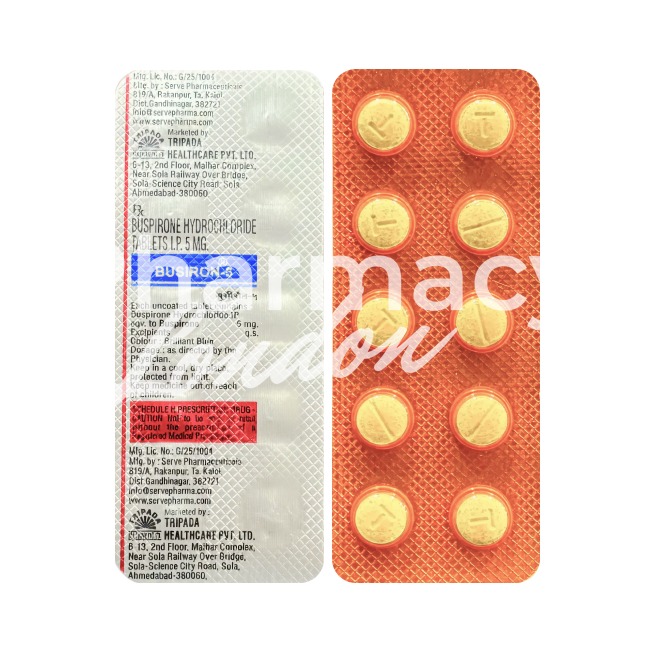
In brief
- Buspirone is a prescription-only medicine (POM) in the UK.
- Buspirone is used primarily to treat generalised anxiety disorder (GAD) and may be used as an adjunct in depression; it acts as a partial agonist at 5-HT1A (serotonin) receptors with moderate affinity for dopamine D2 receptors.
- Usual adult dosing starts at 5 mg two or three times daily, usually 15–30 mg daily in divided doses, with a maximum of 45 mg/day.
- Buspirone is administered orally as tablets (commonly 5 mg and 10 mg, usually blister-packed or in bottles).
- Buspirone is not effective acutely; some patients notice initial effects within 1–2 weeks, with therapeutic benefit generally assessed after 2–4 weeks of treatment.
- The clinical anxiolytic effect of a single dose typically lasts several hours (dosing is usually twice or three times daily); the drug’s plasma half-life is short (around 2–3 hours), so effects are maintained by regular dosing.
- Avoid alcohol while taking buspirone or use with caution — alcohol can increase dizziness, drowsiness and impairment of concentration or coordination.
- The most common side effect is dizziness; other frequent effects include headache, nausea, nervousness, dry mouth and drowsiness.
- Would you like to try buspirone without a prescription?
Basic buspirone information
- INN (international nonproprietary name): Buspirone
- Brand names available in the United Kingdom: Buspar and generics from manufacturers such as Teva, Mylan and Sandoz (5 mg and 10 mg scored tablets).
- ATC code: N05BE01
- Forms and dosages: oral tablets 5 mg and 10 mg.
- Manufacturers: Teva, Mylan, Alvogen and Sandoz (generics).
- OTC / Rx classification: Prescription-only medicine (POM) in the UK.
Legal status and availability in the UK
Buspirone is a prescription-only medicine in the UK, and generics are dispensed most commonly.
In our online pharmacy, buspirone is available without a prescription, with discreet delivery to the United Kingdom in 9–21 days.
Clinical effectiveness in the UK
In NHS primary care, buspirone is used as an alternative to benzodiazepines or when SSRI side effects limit tolerability.
Buspirone gives modest symptom reduction in GAD after four to eight weeks, especially in patients with excessive worry rather than panic attacks.
Clinicians often select buspirone for patients at risk of dependence or for those whose jobs require alertness, such as HGV drivers.
It causes less sedation than benzodiazepines, and discontinuation due to adverse effects is infrequent.
- Typical starting regimen: 5 mg two to three times daily.
- Not suitable for acute relief; scheduled dosing is required.
- Useful as part of a benzodiazepine‑tapering plan in primary care.
| Outcome | Typical finding |
|---|---|
| Time to effect | 2–4 weeks for initial improvement |
| Discontinuation rate | Infrequent |
| Common side effects | Dizziness, headache, nausea |
MHRA oversight remains active; clinicians and pharmacists are encouraged to record Yellow Card reports where clinically significant adverse reactions occur.
Indications and expanded uses
Patients want to know when buspirone is appropriate and when it is not.
- Licensed use: short-term management of anxiety disorders and relief of anxiety symptoms, with or without accompanying depression; prescription-only medicine.
- Common off‑label uses in NHS/private clinics: Adjunctive use with antidepressants for residual anxiety or depressive symptoms, and selective use during benzodiazepine‑tapering strategies.
Buspirone is not routinely used for panic disorder, obsessive‑compulsive disorder or post‑traumatic stress disorder because licensing and evidence do not generally support those indications.
Clinicians may consider buspirone where SSRIs cause intolerable sexual side effects, using it adjunctively under review.
Checklist for clinicians considering off‑label use:
- Confirm primary diagnosis and prior treatments tried.
- Discuss slower onset and need for scheduled dosing with the patient.
- Avoid combination with MAO inhibitors and review hepatic/renal function if impairment is present.
- Document informed consent for off‑label use and set review dates at 4–8 weeks.
Contraindications: concomitant MAO inhibitor use and known hypersensitivity to buspirone.
Composition and brand landscape
Patients often ask what is inside the tablet and which brands are available locally.
The active substance is buspirone, commonly supplied as buspirone hydrochloride in scored oral tablets.
Tablet strengths seen in UK pharmacies are 5 mg and 10 mg scored tablets, with blister packaging more common than bottles.
| Brand | Manufacturer / source | Typical pack sizes |
|---|---|---|
| Buspar | Originator brand | 5 mg, 10 mg; 30–60 tablets |
| Generic buspirone | Teva, Mylan, Sandoz, Alvogen | 5 mg, 10 mg; 30–60 tablets |
- Packaging: blister packs of 30–60 tablets are typical in the UK.
- Substitution: pharmacists commonly dispense generics in line with NHS dispensing policies.
Contraindications and special precautions
Patients and carers frequently ask who should not take buspirone.
Absolute contraindications:
- Known hypersensitivity to buspirone or any tablet excipient.
- Concomitant use with monoamine oxidase (MAO) inhibitors due to risk of hypertensive reactions.
Relative cautions:
- Moderate to severe hepatic or renal impairment — start low and titrate slowly or avoid in severe impairment.
- Elderly patients — increased sensitivity; begin at lower doses such as 5 mg twice daily and monitor closely.
- Pregnancy and lactation — use only if clearly needed and after specialist advice.
Lifestyle advice:
- Although less sedating than benzodiazepines, buspirone may still cause dizziness or drowsiness; advise caution with driving and machinery until response is known.
- Avoid excess alcohol as it may increase CNS effects.
Monitoring: Consider baseline liver and renal checks in comorbid patients and review concomitant medicines for CYP3A4 interactions.
Dosage guidelines
One of the main practical questions is how to start and adjust buspirone safely.
| Dosing item | Recommendation |
|---|---|
| Starting dose (adults) | 5 mg two to three times daily, increased every 2–3 days |
| Usual dose range | 15–30 mg daily in divided doses, titrated by response |
| Maximum dose | 45 mg daily |
| Elderly / hepatic / renal impairment | Start lower (for example 5 mg twice daily) and titrate more slowly; severe hepatic impairment may contraindicate use |
Adherence notes:
- Not suitable for PRN use; scheduled dosing is required for steady plasma levels and clinical benefit.
- If a dose is missed, take as soon as remembered unless it is close to the next dose, in which case skip and do not double up.
Paediatric use: not generally approved and requires specialist paediatric psychiatric input if considered.
Interactions overview
Patients frequently ask whether buspirone mixes safely with their other medicines or alcohol.
| Drug/class | Effect | Action |
|---|---|---|
| MAO inhibitors | Risk of hypertensive reactions | Contraindicated — do not combine |
| Strong CYP3A4 inhibitors (e.g. some macrolides, azole antifungals) | Increased buspirone plasma concentrations | Exercise caution; consider dose adjustment and monitoring |
| CYP3A4 inducers | Reduced buspirone levels and effect | Monitor clinical response; dose adjustment may be needed |
| Alcohol / sedatives | Possible additive CNS depression | Avoid excess alcohol and use caution with other sedatives |
Clinicians should remain vigilant when combining buspirone with strong CYP3A4 modulators.
Comparable medicines and prescribing preferences
Patients commonly ask how buspirone stacks up against SSRIs, benzodiazepines and other options.
NHS first‑line pharmacotherapy for GAD usually prioritises SSRIs or psychological therapies such as CBT.
Buspirone is often chosen as a benzodiazepine‑sparing option or when SSRI side effects limit tolerability.
- Pros of buspirone: lower dependence risk, less sedation, useful for patients needing alertness at work.
- Cons of buspirone: slower onset of action and less evidence for panic disorder or comorbid depression compared with SSRIs.
- Benzodiazepines: fast symptom relief but higher dependence and fall risk in the elderly.
| Medicine class | Onset | Dependence risk | Suitability for elderly |
|---|---|---|---|
| Buspirone | 2–4 weeks | Low | Suitable with lower starting doses |
| SSRIs | 2–6 weeks | Low | Generally suitable with monitoring |
| Benzodiazepines | Minutes–hours | High (dependence risk) | Less suitable due to fall risk |
Frequently asked questions
- How long before buspirone works? Expect initial improvement around two to four weeks, with fuller benefit potentially taking longer.
- Can I drive while taking buspirone? Most people can drive, but avoid driving if you feel dizzy or drowsy after a dose.
- Is buspirone addictive? Buspirone has a much lower dependence risk than benzodiazepines and withdrawal is uncommon.
- What if I miss a dose? Take it when you remember unless it is close to the next dose; do not double the dose.
Definitions: PRN means 'as needed' dosing; buspirone is not PRN and requires scheduled dosing.
Regulatory reminder: buspirone is a prescription‑only medicine in the UK; typical dosing is 5–10 mg two to three times daily.
Guidelines for proper use
Pharmacists play a central role in safe initiation and adherence counselling for buspirone.
Key counselling points for pharmacists:
- Confirm that the prescription aligns with MHRA‑specified indications and allergy history.
- Explain scheduled dosing and emphasise that buspirone is not effective as an immediate 'as‑needed' treatment.
- Set expectations for onset (two to four weeks), and discuss common side effects such as dizziness, headache and nausea.
- Advise avoidance of MAO inhibitors and moderation of alcohol, and to report serious events via the MHRA Yellow Card scheme.
- For elderly patients, discuss fall risk mitigation and start at lower doses with careful titration.
Practical dispensing tips:
Provide a written dosing schedule, offer a simple reminder plan using the NHS patient portal if available, and explain that generic substitution may occur per NHS dispensary policy.
Delivery across the United Kingdom
| City | Region | Delivery Time |
|---|---|---|
| London | England | 9–21 days |
| Birmingham | England | 9–21 days |
| Manchester | England | 9–21 days |
| Glasgow | Scotland | 9–21 days |
| Leeds | England | 9–21 days |
| Liverpool | England | 9–21 days |
| Edinburgh | Scotland | 9–21 days |
| Bristol | England | 9–21 days |
| Sheffield | England | 9–21 days |
| Leicester | England | 9–21 days |
| Coventry | England | 9–21 days |
| Nottingham | England | 9–21 days |
| Newcastle | England | 9–21 days |
| Cardiff | Wales | 9–21 days |
| Belfast | Northern Ireland | 9–21 days |



