
Celebrex
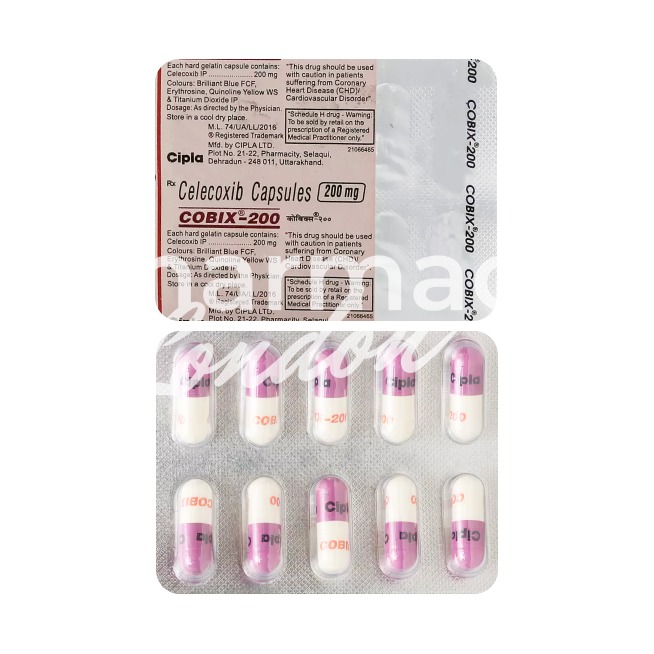
In brief
- In our pharmacy, you can buy Celebrex without a prescription, with delivery across the United Kingdom in 9–21 days; discreet and anonymous packaging is available.
- Celebrex (celecoxib) is used to treat osteoarthritis, rheumatoid arthritis, ankylosing spondylitis, and acute pain (including menstrual pain); it is a selective COX‑2 inhibitor that reduces prostaglandin synthesis to relieve pain and inflammation.
- Usual dosages vary by indication: osteoarthritis 200 mg once daily or 100 mg twice daily; rheumatoid arthritis 100–200 mg twice daily; ankylosing spondylitis 200 mg once daily or 100 mg twice daily; acute pain/menstrual pain initial 400 mg then 200 mg if needed on day 1, then 200 mg twice daily.
- Administered orally as capsules (100 mg and 200 mg).
- Analgesic effect usually begins within 30–60 minutes for many patients, with peak plasma concentrations around 2–3 hours.
- Duration of action is generally about 12 hours (half‑life ~11 hours), so dosing is commonly once or twice daily depending on the regimen and indication.
- Alcohol increases the risk of gastrointestinal side effects and bleeding; avoid excessive alcohol and discuss alcohol use with your prescriber or pharmacist.
- The most common side effect is dyspepsia (indigestion); other frequent effects include abdominal pain, diarrhoea, nausea, headache and dizziness.
- Would you like to try Celebrex without a prescription?
Basic Celebrex information
- INN (international nonproprietary name): Celecoxib
- Brand names available in the United Kingdom: Celebrex® (capsules 100 mg and 200 mg); generic celecoxib from manufacturers such as Teva, Mylan, Sandoz, Hikma, Cipla and Sun Pharma.
- ATC code: M01AH01 (musculo‑skeletal system; selective COX‑2 inhibitors).
- Forms and dosages: capsules 100 mg and 200 mg in blister packs (10, 30, 60).
- Manufacturers: Pfizer, the original developer (Celebrex®); generics are supplied by the manufacturers listed above.
- Registration status in the United Kingdom: prescription-only medicine
- OTC / Rx classification: Prescription only (Rx)
Legal status and availability in the UK
In our online pharmacy, Celebrex is available without a prescription, with discreet delivery to the United Kingdom in 9–21 days.
Clinical effectiveness in the UK
Within NHS practice celecoxib is prescribed where effective anti‑inflammatory analgesia is required with a lower risk of dyspepsia or peptic ulcer recurrence compared with traditional NSAIDs.
Celecoxib provides symptom reduction in osteoarthritis and rheumatoid arthritis comparable to ibuprofen or naproxen.
Tolerability is often better in patients whose previous NSAIDs caused indigestion or heartburn.
For acute indications such as menstrual pain or post‑operative analgesia, short courses produce rapid relief when dosed as recommended.
Blood pressure and renal function should be monitored during prolonged use of any NSAID, including celecoxib.
Adherence tends to improve when pharmacists provide counselling at dispensing and review interactions such as with antihypertensives or anticoagulants.
| Comparison | Symptom change | Tolerability |
|---|---|---|
| Celecoxib vs Ibuprofen | Comparable reduction in pain scores | Often better for dyspepsia history |
| Celecoxib vs Naproxen | Similar anti‑inflammatory effect | Fewer upper GI complaints in some cohorts |
Indications and expanded uses
Prescribers need clarity on when celecoxib is authorised and when it is an off‑label option.
In the UK, celecoxib is authorised for the symptomatic relief of osteoarthritis, rheumatoid arthritis and ankylosing spondylitis in adults.
Short-term use for acute pain, including menstrual pain, is off‑label.
In NHS practice some clinicians use celecoxib off‑label in carefully selected neuropathic‑type pain where GI risk precludes traditional NSAIDs, following risk assessment.
It is contraindicated in pregnancy, particularly the third trimester, and in patients with known NSAID hypersensitivity or sulfonamide allergy.
Primary‑care decision making should follow a simple flow: assess GI risk, assess cardiovascular risk, check renal and hepatic function, then choose therapy and arrange monitoring.
Composition and brand landscape
Pharmacists must be precise about formulation, strengths and brands when counselling patients.
The active ingredient is celecoxib, the INN, which is a selective cyclo‑oxygenase‑2 (COX‑2) inhibitor with ATC code M01AH01.
Celebrex® (Pfizer) is the widely recognised brand in the UK, sold as 100 mg and 200 mg capsules.
Multiple therapeutically equivalent generics are available and are often used on NHS formularies.
Commonly available forms are capsules in 100 mg and 200 mg strengths supplied in blister packs of 10, 30 or 60.
| Brand / manufacturer | Strengths | Common package sizes |
|---|---|---|
| Celebrex® (Pfizer) | 100 mg, 200 mg | Blister packs of 10, 30, 60 |
| Generic celecoxib (Teva, Mylan, Sandoz, Hikma, Cipla, Sun Pharma) | 100 mg, 200 mg | Blister packs of 10, 30, 60 |
Contraindications and special precautions
Before dispensing, clinicians must check for absolute contraindications and relative cautions.
Absolute contraindications include known allergy to celecoxib, sulfonamides, NSAIDs, or any inactive ingredients listed on the product label.
A history of asthma, urticaria or other allergic reactions after aspirin or other NSAIDs is also an absolute contraindication.
Active gastrointestinal bleeding or peptic ulcer disease and pregnancy (especially the third trimester) are absolute contraindications.
Relative cautions include established cardiovascular disease, uncontrolled hypertension, heart failure and significant hepatic or renal impairment.
Elderly patients should be started on the lowest effective dose with regular monitoring of renal function and blood pressure.
Advise patients to avoid heavy alcohol as it increases the risk of GI bleeding and to report dark stools or sudden severe abdominal pain immediately.
Refer to MHRA safety notices and use Yellow Card reporting for suspected severe reactions or new interaction signals.
Dosage guidelines
Patients commonly ask, "What dose do I take and how often?"
For osteoarthritis the standard regimens are 200 mg once daily or 100 mg twice daily.
For rheumatoid arthritis adults, dosing is typically 100–200 mg twice daily depending on response and tolerance.
Ankylosing spondylitis is commonly dosed at 200 mg once daily or 100 mg twice daily.
For acute pain and menstrual cramps (off‑label) an initial 400 mg may be given then 200 mg if needed on day one, followed by 200 mg twice daily as required.
Reduce the initial dose by 50% in moderate hepatic impairment (Child‑Pugh B) and avoid in severe impairment.
In renal impairment and in older people start at the lowest effective dose and monitor renal function, blood pressure and signs of fluid retention.
If a dose is missed, take it as soon as remembered unless it is near the next scheduled dose and never double up.
Interactions overview
Patients on multiple medicines need careful screening for interactions with celecoxib.
Combining celecoxib with anticoagulants such as warfarin or direct oral anticoagulants raises bleeding risk and requires clinical review.
Co‑prescription with antiplatelet agents increases bleeding risk; low‑dose aspirin reduces the COX‑2 gastro‑protection advantage.
ACE inhibitors, ARBs and diuretics may have reduced antihypertensive effect when taken with NSAIDs, and combined use can increase renal risk.
SSRIs and SNRIs plus celecoxib raise gastrointestinal bleeding risk compared with either agent alone.
Concurrent nephrotoxins (for example some antibiotics or diuretics) add to the risk of acute kidney injury when combined with NSAIDs.
Alcohol should be minimised because it increases the likelihood of gastrointestinal adverse events.
Always check the patient’s medicines before dispensing and counsel appropriately.
Comparable medicines and preferences
Clinicians weigh GI protection against cardiovascular signals when choosing between NSAIDs.
Key alternatives on NHS pathways include etoricoxib (another selective COX‑2 agent) and traditional NSAIDs such as ibuprofen, naproxen and diclofenac.
Naproxen is sometimes preferred when clinicians seek an NSAID with a perceived lower cardiovascular signal, while COX‑2 agents offer greater GI protection.
Paracetamol remains first‑line for some osteoarthritis patients because of its safety profile despite limited anti‑inflammatory effect.
For acute severe pain, short‑term opioid therapy may be considered with caution and specialist oversight where appropriate.
| Medicine | Efficacy | GI risk | CV risk |
|---|---|---|---|
| Celecoxib | Good for inflammatory pain | Lower than non‑selective NSAIDs | Dose‑dependent; caution in CVD |
| Naproxen | Good | Higher than COX‑2 | Perceived lower CV signal |
| Ibuprofen | Good for mild–moderate pain | Higher than COX‑2 | Moderate |
| Paracetamol | Limited anti‑inflammatory effect | Low | Low |
Frequently asked questions
-
Can I take celecoxib if I get indigestion on ibuprofen?
Often yes — celecoxib tends to cause less dyspepsia than non‑selective NSAIDs, but check for NSAID or sulfonamide allergy and discuss cardiovascular risk with your GP or pharmacist.
-
Is celecoxib safe long term?
Long‑term use is possible for chronic arthritis at the lowest effective dose with periodic monitoring of blood pressure, renal and liver function and regular clinical review.
-
Can I take it with my blood thinner?
Not without medical review — combined use increases bleeding risk, so contact your prescriber or pharmacist before starting celecoxib.
-
Can I drink alcohol while taking it?
Avoid heavy drinking because it raises GI bleed risk; discuss moderate intake with your clinician if needed.
Signpost patients to NHS.uk and MHRA advice sheets when further reassurance is required.
Guidelines for proper use
Pharmacist counselling should be practical, clear and documented in the pharmacy record.
Begin by confirming the indication and reviewing allergies, especially to NSAIDs and sulfonamides.
Check current medicines for anticoagulants, antiplatelets, antihypertensives and nephrotoxins and counsel about interaction risks.
Explain dosing and timing clearly and advise patients not to double up on missed doses.
Warn patients about red‑flag symptoms such as sudden chest pain, breathlessness, severe abdominal pain, black stools or any signs of bleeding.
Arrange or recommend monitoring of blood pressure, renal and liver function for patients on prolonged therapy.
Offer a short patient handout summarising dose, common side‑effects and when to seek urgent help and signpost MHRA Yellow Card reporting for suspected adverse reactions.
Store advice: keep the medicine in original packaging, below 25°C, dry and out of reach of children, and do not use past the expiry date.
Delivery across the United Kingdom
| City | Region | Delivery Time |
|---|---|---|
| London | England | 9–21 days |
| Birmingham | England | 9–21 days |
| Manchester | England | 9–21 days |
| Leeds | England | 9–21 days |
| Glasgow | Scotland | 9–21 days |
| Liverpool | England | 9–21 days |
| Bristol | England | 9–21 days |
| Edinburgh | Scotland | 9–21 days |
| Sheffield | England | 9–21 days |
| Newcastle | England | 9–21 days |
| Nottingham | England | 9–21 days |
| Leicester | England | 9–21 days |
| Cardiff | Wales | 9–21 days |



