
Cyclogest
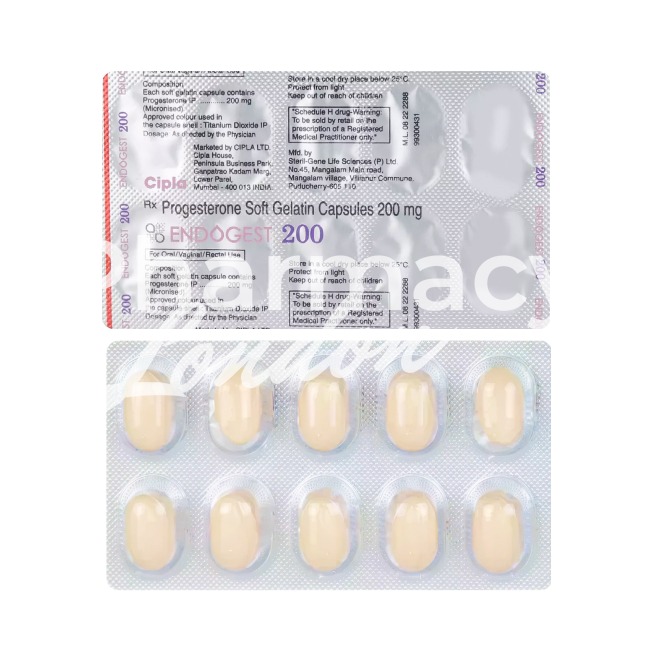
In brief
- In our pharmacy, you can buy Cyclogest without a prescription, with delivery in 9–21 days throughout the United Kingdom. Discreet and anonymous packaging.
- Cyclogest is a natural micronised progesterone preparation used for luteal phase support (for assisted conception), prevention of miscarriage in some settings, and for progesterone replacement; it acts on progesterone receptors to prepare and maintain the endometrium, reduce uterine contractility and support early pregnancy.
- The usual dose is 400 mg (one pessary) vaginally once daily at bedtime for luteal support; some indications or protocols may use 400 mg twice daily or 200 mg twice daily — follow the instructions given for your situation.
- The form of administration is a vaginal pessary/suppository (inserted high into the vagina); formulations may also exist as vaginal capsules or oral softgels in other brands.
- The effect typically begins within 1–2 hours after vaginal insertion as progesterone is absorbed locally and systemically over a few hours.
- The duration of action is approximately 12–24 hours per dose, which is why dosing is usually once or twice daily depending on the regimen.
- Avoid or limit alcohol while using Cyclogest, as alcohol can increase drowsiness and may worsen side effects such as dizziness or mood changes.
- The most common side effect is increased vaginal discharge or local irritation; other frequent effects include headache, breast tenderness, nausea, dizziness and mood changes.
- Would you like to try Cyclogest without a prescription?
Basic Cyclogest information
- INN (international nonproprietary name): Progesterone.
- Brand names available in the United Kingdom: Cyclogest (progesterone pessaries); Utrogestan (micronised progesterone capsules).
- ATC code: G03DA04.
- Forms & Dosages: Cyclogest pessaries 200 mg and 400 mg; micronised progesterone soft capsules 100 mg and 200 mg.
- Manufacturers in the United Kingdom: Besins Healthcare (Utrogestan) and other manufacturers.
- Registration status in the United Kingdom: Prescription only (Rx).
- OTC / Rx classification: Prescription only (Rx).
Legal status and availability in the UK
In our online pharmacy, Cyclogest is available without a prescription, with discreet delivery to the United Kingdom in 9–21 days.
Clinical effectiveness in the UK
What can patients expect when progesterone is prescribed in NHS practice?
Good control of bleeding and reliable endometrial protection are expected when prescribers follow product information and MHRA guidance.
Fertility services frequently prefer vaginal progesterone for luteal support after IVF because of direct uterine bioavailability.
Oral capsules such as Utrogestan are convenient but can occasionally cause sedation or GI upset.
Vaginal pessaries such as Cyclogest tend to reduce systemic side effects while producing local discharge or practical inconvenience for some users.
- Measured outcomes: bleeding control, endometrial protection, patient satisfaction, adverse events.
- Typical trade‑offs: oral convenience versus vaginal local tolerability.
| Route | Typical benefits | Typical downsides |
|---|---|---|
| Oral micronised (Utrogestan) | Convenient, standardised dosing | Possible sedation, GI upset |
| Vaginal pessary (Cyclogest) | Lower systemic effects, good uterine concentration | Local discharge, application inconvenience |
Indications and expanded uses
Why might a clinician choose one progesterone formulation over another?
Licensed indications in UK practice include endometrial protection during combined HRT, luteal support during assisted reproduction (vaginal progesterone such as Cyclogest) and treatment of secondary amenorrhoea.
Off‑label use occurs in reproductive medicine, for example vaginal administration of oral micronised capsules.
Clinicians should document rationale, discuss consent and monitoring for any off‑label regimen.
- Approved: endometrial protection with oestrogen; luteal support in assisted reproduction (vaginal progesterone); secondary amenorrhoea.
- Common off‑label: vaginal use of oral micronised capsules where local practice permits.
| Indication | Typical regimen |
|---|---|
| Secondary amenorrhoea | 400 mg orally nightly for 10 days (repeat as prescribed) |
| Endometrial protection (HRT) | 200 mg orally nightly for 12 days of a 28‑day cycle |
| Luteal support (fertility) | Vaginal progesterone 100–400 mg daily (protocol dependent) |
Composition and brand landscape
Which brands and formulations are encountered in UK practice?
The active ingredient across brands is progesterone (INN), listed under ATC G03DA04.
In the UK the portfolio commonly includes Utrogestan as micronised oral capsules and Cyclogest as a vaginal pessary.
Forms include micronised progesterone capsules 100 mg and 200 mg and Cyclogest pessaries 200 mg and 400 mg.
| Brand | Form | Common pack sizes | Excipient notes |
|---|---|---|---|
| Utrogestan | Oral micronised capsules | 30/90 | Check SPC for excipients |
| Cyclogest | Vaginal pessaries | 15/30 | Designed for vaginal use; excipient details in SPC |
Contraindications and special precautions
Who should not take progesterone or who requires extra caution?
Absolute contraindications include severe hepatic dysfunction, known or suspected breast cancer or other hormone‑dependent malignancy, undiagnosed vaginal bleeding, current or previous thrombosis, allergy to any excipient, and pregnancy in certain indications.
Relative contraindications include mild/moderate hepatic or renal impairment, migraine, asthma, psychiatric disorders and cardiovascular disease and require monitoring.
Practical UK pharmacy advice is to flag contraindications on electronic prescriptions and discuss them during counselling.
Advise patients that sedation or drowsiness may affect driving and to avoid alcohol if affected.
- Screening checklist: liver disease, breast cancer history, thrombotic history, unexplained bleeding, known excipient allergy.
- Pharmacy action: record issues in NHS records and consider MHRA alerts when dispensing.
Dosage guidelines
What are the standard doses and practical instructions?
Standard product information gives 400 mg orally at bedtime for 10 days for secondary amenorrhoea, and 200 mg orally at bedtime for 12 days of a 28‑day cycle for endometrial protection with oestrogen.
Vaginal preparations, commonly used in fertility, follow clinic protocols and typically range from 100–400 mg daily depending on the indication.
Special populations: not indicated in children; elderly require monitoring but usually no dose change; contraindicated in severe hepatic impairment and use with caution in renal impairment.
Missed dose advice: take as soon as remembered unless near the next scheduled dose; do not double up.
Overdose management is supportive; symptoms may include sedation, nausea and withdrawal bleeding.
| Indication | Usual dose |
|---|---|
| Secondary amenorrhoea | 400 mg orally nightly for 10 days |
| HRT endometrial protection | 200 mg orally nightly for 12 of 28 days |
| Luteal support (clinic protocol) | 100–400 mg vaginally daily (protocol dependent) |
Interactions overview
Which medicines and substances can affect progesterone?
Enzyme‑inducing drugs such as certain antiepileptics, rifampicin and some antivirals can lower progesterone plasma levels and reduce efficacy.
Oestrogens are commonly used together intentionally in HRT regimens and are not a negative interaction in that context.
CNS depressants and alcohol may add to sedation from progesterone and patients should be warned.
Food interactions are limited, though softgels with lipid excipients may have absorption variability with high‑fat meals.
- Check for enzyme inducers on repeat prescriptions.
- Advise patients on CNS depressant co‑use to take extra care when driving.
- Report suspected interaction signals to the MHRA Yellow Card scheme.
Comparable medicines and preferences
What are common alternatives to micronised progesterone in UK practice?
Synthetic progestins such as medroxyprogesterone acetate (Provera) and dydrogesterone (Duphaston) are widely used alternatives.
Differences include receptor profiles, thrombosis risk and systemic side‑effect patterns.
Micronised progesterone is often described as “natural” progesterone and is sometimes preferred for HRT endometrial protection or fertility support on the basis of tolerability.
| Medicine | Form | Key differences |
|---|---|---|
| Medroxyprogesterone (Provera) | Tablet/Injectable | Synthetic progestin; different thrombosis and metabolic profile |
| Dydrogesterone (Duphaston) | Oral tablet | Oral synthetic with distinct receptor action |
| Micronised progesterone | Oral/vaginal | Same natural hormone as endogenous progesterone; different excipient profiles |
Use a pros and cons checklist in consultations to support shared decision making between routes and products.
FAQ — common NHS patient questions
Will progesterone make me sleepy?
Some patients report dizziness, fatigue or drowsiness and should avoid driving or heavy machinery if affected.
Can I use oral capsules vaginally?
Vaginal use of some oral micronised capsules is reported in practice but is off‑label; clinicians should document the rationale and follow local protocol.
What if I miss a dose?
Take as soon as remembered unless it is close to the next scheduled dose; do not double up.
Are there allergy risks?
Check excipients carefully; always verify the SPC and inform the pharmacist of allergies.
Guidelines for proper use and counselling
What should a pharmacist tell a patient starting progesterone?
Counselling should include the indication, administration route, dosing schedule and expected bleeding patterns.
Discuss common side‑effects such as headache, breast tenderness, mood changes, nausea and possible sedation.
Advise storage below 25°C, protected from moisture and light, and to keep medication in the original packaging.
Document contraindications in NHS records and report suspected adverse reactions via the MHRA Yellow Card scheme.
- Counselling checklist: indication, dose, route, side‑effects, storage, when to seek help.
Delivery across the United Kingdom
| City | Region | Delivery time |
|---|---|---|
| London | Greater London | 9–21 days |
| Birmingham | West Midlands | 9–21 days |
| Manchester | Greater Manchester | 9–21 days |
| Leeds | West Yorkshire | 9–21 days |
| Glasgow | Scotland | 9–21 days |
| Edinburgh | Scotland | 9–21 days |
| Bristol | South West England | 9–21 days |
| Sheffield | South Yorkshire | 9–21 days |
| Newcastle Upon Tyne | North East England | 9–21 days |
| Norwich | East of England | 9–21 days |
| Plymouth | South West England | 9–21 days |
| Kingston Upon Hull | East Yorkshire | 9–21 days |
| Stirling | Scotland | 9–21 days |
| Llanelli | Wales | 9–21 days |



