
Doxepin
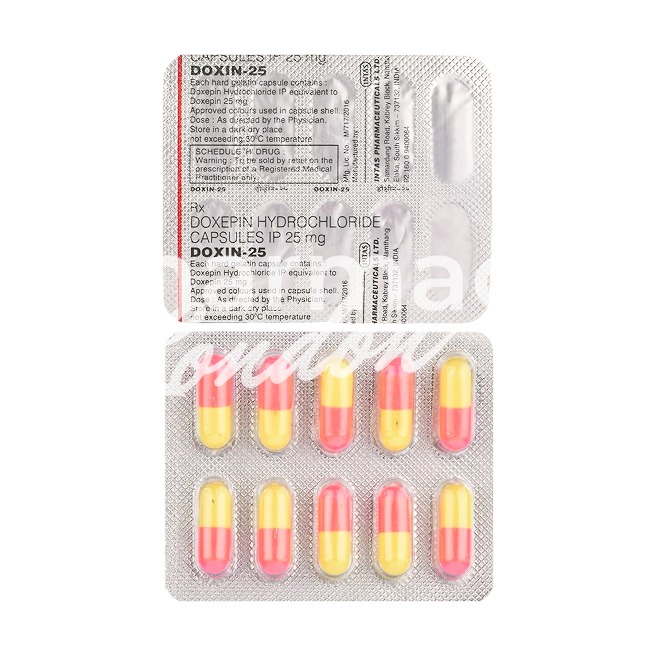
In brief
- In our pharmacy, you can buy doxepin without a prescription, with delivery in 9–21 days throughout the United Kingdom. Discreet and anonymous packaging.
- Doxepin is used for major depressive disorder, certain anxiety disorders, chronic pruritus and, at low doses, insomnia. It is a tricyclic antidepressant that non‑selectively inhibits norepinephrine and serotonin reuptake and has strong H1 antihistamine activity responsible for sedation and antipruritic effects.
- The usual systemic dose for depression is typically 25–150 mg daily (the defined daily dose is 100 mg); low‑dose preparations for insomnia are much smaller (commonly 3–6 mg at bedtime) and topical creams are dosed as a percentage formulation (e.g. 5% cream for pruritus).
- Available forms of administration include oral capsules/tablets, oral solution, and topical cream (e.g. 5% cream for dermatologic use).
- Sedative and antihistamine effects begin within 30–60 minutes; antidepressant benefits usually take 2–4 weeks of regular use to become apparent.
- Duration of action varies by dose and formulation but commonly ranges from about 6 to 24 hours; low‑dose formulations for insomnia are intended to act overnight.
- Do not consume alcohol while taking doxepin — alcohol increases central nervous system depression and the risk of excessive drowsiness and other adverse effects.
- The most common side effect is drowsiness (sedation); other frequent effects include dry mouth, constipation, blurred vision and urinary retention due to anticholinergic activity.
- Would you like to try doxepin without a prescription?
Basic doxepin information
- INN (international nonproprietary name): Doxepin (doxepin hydrochloride), a tricyclic antidepressant (TCA).
- Brand names available in the United Kingdom: Generic doxepin is available in the United Kingdom.
- ATC code: N06AA12 (systemic doxepin); D04AX01 (topical antipruritic).
- Forms and strengths: systemic forms include capsules, tablets and oral solution; topical form is a cream (commonly 5% for pruritus).
Legal status and availability in the UK
Doxepin is a prescription-only medicine (POM) in the UK.
In our pharmacy, doxepin is available without a prescription, with discreet delivery to the United Kingdom in 9‑21 days.
Clinical effectiveness in the UK
How is doxepin used in NHS practice?
Within NHS mental health services and primary care, doxepin is now generally a second‑ or third‑line TCA choice for major depressive disorder and selected anxiety disorders after SSRI/SNRI trials.
Specialist teams commonly use low‑dose regimens for sleep disturbance and report clinically meaningful improvements in sleep maintenance and patient‑reported sleep quality.
Responders often notice improved mood and better sleep, but adherence can be reduced by anticholinergic side‑effects such as dry mouth, constipation, blurred vision and daytime somnolence.
In chronic pruritus clinics, topical doxepin creams are a recognised option to reduce itch where antihistamines and topical steroids have failed.
- Outcome measures used: PHQ‑9 for depression, GAD‑7 for anxiety, and ISI (Insomnia Severity Index) for sleep assessment.
| Indication | Typical clinical endpoints |
|---|---|
| Major depressive disorder | Remission rates and PHQ‑9 score reduction. |
| Insomnia (low dose) | Improved sleep maintenance, reduced night‑time awakenings, ISI improvement. |
| Chronic pruritus (topical) | Reduction in itch scores and improved skin comfort. |
NHS clinics typically monitor treatment response with PHQ‑9 or GAD‑7 and perform baseline ECGs for patients with cardiac risk factors and fall‑risk reviews for people aged 65 and over.
Indications and expanded uses
What is licensed and what is specialist or off-label?
- Main licensed uses
- Major depressive disorder and anxiety disorders via systemic formulations.
- Dermatological use
- Chronic pruritus treated with topical cream formulations.
- Low-dose use
- Low‑dose preparations are used for insomnia in specialist protocols.
MHRA licences in the UK tend to reflect these core uses, but exact marketing authorisations and product SPCs vary by brand and formulation, so prescribers must check the product SPC and the BNF before prescribing.
Common off-label or specialist uses in UK practice include:
- Neuropathic pain management in selected patients within specialist clinics.
- Chronic urticaria refractory to standard therapy under dermatology review.
- Occasional secondary option for sleep disturbance in psychiatric clinics.
Off‑label prescribing should be reserved for specialist settings, with documented rationale, informed consent and monitoring plans because of cardiac and anticholinergic risks.
Composition and brand landscape
What forms does doxepin come in?
The active substance is doxepin hydrochloride, a tricyclic antidepressant (TCA) with ATC N06AA12 for systemic use and D04AX01 for topical antipruritics.
The UK market has generic doxepin capsules and tablets commonly in 10 mg, 25 mg and 50 mg strengths, and topical creams for pruritus.
Contraindications and special precautions
Who should avoid doxepin and what precautions are needed?
- Absolute/relative contraindications: recent MAOI use, known hypersensitivity to doxepin, acute recovery phase after myocardial infarction, uncontrolled narrow‑angle glaucoma, urinary retention and severe prostatic hypertrophy.
- High‑risk groups: older adults (higher anticholinergic and cognitive risks), pregnancy and breastfeeding (requires risk–benefit discussion), significant cardiac disease including arrhythmias and prolonged QT, bipolar disorder (risk of manic switch), and severe hepatic impairment.
Practical precautions include a baseline ECG for patients with cardiac risk factors and orthostatic blood pressure checks when initiating or titrating systemic therapy.
Review the anticholinergic burden score in frail or elderly patients, advise on driving and sedation, and avoid alcohol while taking doxepin.
Encourage MHRA Yellow Card reporting for suspected adverse drug reactions and counsel patients to report signs of anticholinergic toxicity and any worsening mood or suicidal thoughts.
ECG and orthostatic monitoring are triggered by known cardiac disease, concomitant QT‑prolonging drugs, or age over 65 with polypharmacy.
Dosage guidelines
What doses are typical and how are they titrated in UK practice?
Dosing must be individualised and follow BNF and SPC guidance with specialist advice for psychiatric indications.
Clinical practice ranges from single‑digit milligram low doses at night for insomnia to tens or low hundreds of milligrams daily for depressive disorder.
Start low and titrate slowly with review of response and side‑effects at 1–2 week intervals during initial treatment.
Older adults and patients with hepatic impairment should start at lower doses and have longer titration intervals.
Topical creams should be used as directed by dermatology specialists and patients must be monitored for contact dermatitis.
| Indication | Typical starting dose range | Monitoring checks |
|---|---|---|
| Major depressive disorder | Titrated towards tens to low hundreds of mg daily (BNF/SPC reference required) | PHQ‑9, ECG if cardiac risk, blood pressure monitoring |
| Insomnia (low dose) | Single‑digit mg at night (specialist protocols) | Sleep diary, daytime somnolence assessment |
| Topical pruritus | Apply cream as directed by specialist | Check for local skin reaction and systemic anticholinergic signs |
For exact numeric regimens and full contraindications consult the BNF and the product SPC before prescribing.
Interactions overview
Which medicines and substances interact with doxepin?
Major interactions include hazardous combinations with MAO inhibitors, and increased serotonin syndrome risk with SSRIs, SNRIs, tramadol or linezolid.
CYP interactions are important because doxepin is metabolised via CYP pathways including CYP2D6 and CYP2C19, so strong inhibitors such as fluoxetine, paroxetine or quinidine can raise plasma levels and increase toxicity risk.
Co‑use with antihistamines, antipsychotics, opioids, benzodiazepines and alcohol increases sedation and anticholinergic effects and raises fall risk, especially in older patients.
There are no major routine food interactions, but alcohol potentiates sedation and should be avoided.
Sedation, falls and anticholinergic adverse effects are common concerns; suspected reactions should be reported via the MHRA Yellow Card scheme.
- Managing a suspected interaction: stop the suspect medicine if severe, seek specialist advice, perform ECG if cardiac symptoms emerge, and monitor closely for anticholinergic or serotonergic signs.
Comparable medicines and preferences
What are the NHS alternatives and how do they compare?
| Drug/class | Main indications | Key advantages | Main risks |
|---|---|---|---|
| SSRIs (sertraline, citalopram, fluoxetine) | First‑line for many depressive and anxiety disorders | Better tolerability, lower anticholinergic burden, safer in overdose | Sexual dysfunction, GI upset, serotonergic interactions |
| Mirtazapine | Depression with insomnia or weight loss | Sedating, appetite stimulating | Weight gain, sedation, some metabolic effects |
| Amitriptyline | Neuropathic pain; low‑dose insomnia | Useful in neuropathic pain; sedating in low doses | High anticholinergic burden, cardiac risk |
NHS prescribing choice balances comorbidity, suicide and overdose risk, anticholinergic burden and patient preference, with older patients often guided to alternatives that have lower anticholinergic load.
Frequently asked questions
Will doxepin make me sleepy?
Sedation is a common side effect, particularly during initiation and at higher doses.
Avoid driving or operating machinery until you know how doxepin affects you and avoid alcohol while taking it.
Report excessive daytime sleepiness, falls, or confusion to your prescriber.
Is doxepin safe in older people?
Doxepin can be used in older adults but requires careful review of anticholinergic burden and falls risk.
Baseline ECG and ongoing monitoring are commonly recommended in frail patients.
Can I take doxepin with my other medicines?
Do not combine doxepin with MAO inhibitors and check for interactions with SSRIs, strong CYP inhibitors and other sedatives.
Bring a full medicine list to your GP or pharmacist and follow their interaction checklist.
How long until it works?
Low doses used for sleep can have effect within nights, while antidepressant benefits typically require several weeks with regular follow‑up and outcome measurement.
Guidelines for proper use
What should pharmacists and clinicians tell patients at dispensing?
Confirm the indication and prior treatment trials and explain the expected benefits and typical timeframes for effect.
Review all current medicines including OTC and herbal remedies and document consent for off‑label use when applicable.
Advise on driving restrictions, avoid alcohol and discuss practical measures for dry mouth and constipation.
Monitoring schedule to offer patients:
- Baseline ECG if cardiac risk is present.
- Blood pressure and orthostatic checks on initiation and after dose changes.
- Review at 1–2 weeks, then regularly, using PHQ‑9 or GAD‑7 as appropriate.
Patient support and safety:
Signpost patients to the NHS App and local IAPT services for psychological support and to dermatology clinics for pruritus follow‑up.
Encourage reporting of adverse effects via the MHRA Yellow Card scheme and advise safe disposal of unused tablets through pharmacy returns.
Delivery across the United Kingdom
| City | Region | Delivery Time |
|---|---|---|
| London | England | 9–21 days |
| Birmingham | England | 9–21 days |
| Manchester | England | 9–21 days |
| Glasgow | Scotland | 9–21 days |
| Leeds | England | 9–21 days |
| Edinburgh | Scotland | 9–21 days |
| Bristol | England | 9–21 days |
| Cardiff | Wales | 9–21 days |
| Belfast | Northern Ireland | 9–21 days |
| Sheffield | England | 9–21 days |
| Liverpool | England | 9–21 days |
| Newcastle | England | 9–21 days |
| Southampton | England | 9–21 days |



