
Duphaston
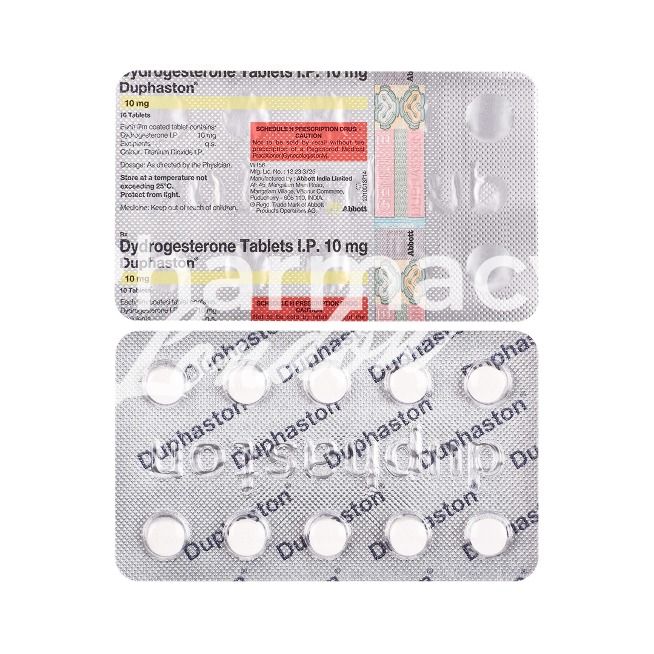
In brief
- Duphaston (dydrogesterone) is a prescription-only medicine, typically supplied as 10 mg tablets in blisters of 20; it has been withdrawn from the UK market since 2008.
- Duphaston is used as a progestogen for indications including secondary amenorrhoea, luteal phase insufficiency and infertility support, dysfunctional uterine bleeding, threatened or habitual abortion, endometriosis, dysmenorrhoea/PMS and as part of HRT; its mechanism is as a synthetic progesterone receptor agonist that supports the luteal phase and stabilises the endometrium, with minimal androgenic, oestrogenic or glucocorticoid activity.
- Usual adult doses vary by indication: commonly 10 mg once daily (e.g. luteal support, HRT) or 10 mg twice daily (e.g. secondary amenorrhoea, dysfunctional bleeding); endometriosis often 10–20 mg daily; threatened abortion protocols may start with higher initial doses (for example an initial 40 mg then 10 mg every 8 hours), and habitual abortion regimens frequently use 10 mg daily until about week 20 of pregnancy — follow a prescriber’s instructions for exact regimens.
- The form of administration is oral tablets only (10 mg tablets); no approved injectable, vaginal or cream formulations are marketed for Duphaston.
- Plasma levels are reached within a few hours after an oral dose (typically within 1–3 hours); clinical effects on bleeding patterns or pregnancy support may take several days to become apparent depending on the indication.
- Duration of action generally covers the dosing interval used (once or twice daily); clinical/progestogenic effects are maintained with regular daily dosing and dosing schedules are tailored to the condition being treated.
- Alcohol does not have a specific contraindicated interaction with dydrogesterone, but avoid excessive alcohol intake — alcohol may worsen side effects (e.g. dizziness, fatigue) and both alcohol and Duphaston should be used cautiously in patients with hepatic impairment.
- The most common side effects include breast pain or tenderness, headache, nausea, abdominal discomfort and menstrual irregularities (spotting or breakthrough bleeding); fatigue and rare mild oedema can also occur.
- Would you like to try Duphaston without a prescription?
Basic Duphaston information
- INN (international nonproprietary name): Dydrogesterone.
- Brand names available in the United Kingdom: Duphaston is no longer available in the UK (since 2008).
- ATC code: G03DB01.
- Forms & dosages: Tablet, 10 mg strength, blisters usually of 20 tablets.
- Manufacturer: Abbott (Laboratoires Abbott Products).
- Registration status in the United Kingdom: Duphaston is withdrawn from the UK market (no current UK licence).
- OTC / Rx classification: Prescription-only (Rx).
Legal status and availability in the UK
Duphaston has not been available on the UK market since 2008; dydrogesterone remains a prescription-only medicine.
In our online pharmacy, Duphaston is available without a prescription, with discreet delivery to the United Kingdom in 9–21 days.
Clinical effectiveness in the UK
Available evidence supports dydrogesterone for luteal support, dysfunctional uterine bleeding and recurrent miscarriage, but direct UK outcome data are limited.
Duphaston has not been marketed in the UK since 2008, so NHS data on dydrogesterone are sparse.
Tolerability is frequently described as favourable compared with some synthetic progestogens, and assisted reproduction studies report pregnancy rates comparable to vaginal progesterone.
For UK fertility clinics the pragmatic appeal of an oral dydrogesterone tablet is clear, but the absence of a UK licence limits routine NHS prescribing.
Patients in the UK are usually advised about alternatives such as micronised progesterone and norethisterone.
Indications and expanded uses
Dydrogesterone (ATC G03DB01) is used for a range of gynaecological and obstetric indications.
Indications listed in its product information include secondary amenorrhoea, dysfunctional uterine bleeding, luteal phase support, threatened and recurrent abortion, endometriosis, dysmenorrhoea and use within HRT regimens.
There is no current UK licence for Duphaston, so any use in the UK is unlicensed.
Typical adult dosing drawn from product information includes 10 mg twice daily for secondary amenorrhoea (cycle days 11–25) and 10 mg daily for luteal support, with higher initial dosing in some threatened-abortion protocols.
Off-label NHS or private practice regimens vary by clinical need, and prescribers must document rationale and obtain informed consent when using unlicensed or imported medicines.
- Secondary amenorrhoea: 10 mg twice daily, days 11–25; duration per specialist advice.
- Luteal support: 10 mg daily or 10 mg twice daily depending on protocol; typically for 3–6 cycles in infertility care.
- Threatened abortion: Initial higher dosing (for example 40 mg then 10 mg every 8 hours) with maintenance dosing as needed; document consent.
- Dysfunctional bleeding/endometriosis/PMS: Regimens commonly 10–20 mg daily or 10 mg twice daily on specified cycle days.
Composition and brand landscape
The active ingredient is dydrogesterone (INN), formulated only as a 10 mg oral tablet in marketed packs.
The main brand is Duphaston, typically supplied as blisters of 20 tablets with 10 mg strength per tablet.
Duphaston is manufactured by Abbott (Laboratoires Abbott Products).
No injectable, vaginal or topical dydrogesterone formulations are currently marketed; oral tablets are the sole form available.
In the UK there are no current marketed Duphaston packs (withdrawn in 2008).
Contraindications and special precautions
Absolute contraindications include known hypersensitivity to dydrogesterone, progestogen-dependent tumours, active or severe liver disease, and undiagnosed vaginal bleeding.
Relative contraindications that warrant monitoring include a history of depression, thromboembolic disorders (personal or strong family history), uncontrolled hypertension, renal impairment and diabetes mellitus.
The product information advises caution in hepatic impairment and states the drug is not recommended in severe liver disease.
In pregnancy, dydrogesterone is used in some protocols for threatened or habitual abortion, but prescribers should document benefit–risk discussions and obtain informed consent.
Practical daily-life cautions include warning patients about possible dizziness or fatigue; there are no formal driving restrictions but patients should take care until they know how they react.
Pharmacists in the UK should ensure documentation when an imported or unlicensed product is supplied, and counsel patients about red flags such as symptomatic liver disease or signs of venous thromboembolism.
- Absolute contraindications: Stop and refer if severe liver disease, progestogen-dependent tumour, allergy or unexplained vaginal bleeding is present.
- Relative risks: Monitor mood, blood pressure, glucose and thrombotic risk where indicated.
Dosage guidelines
Common regimens include 10 mg twice daily for secondary amenorrhoea (cycle days 11–25) and 10 mg daily for luteal insufficiency or luteal support (days 14–25 or continuous depending on protocol).
For dysfunctional uterine bleeding a short course of 10 mg twice daily for 5–7 days is typical, while threatened abortion protocols may use an initial loading approach followed by maintenance dosing.
Habitual-abortion treatment usually uses 10 mg daily continued through at least week 20 of pregnancy when a clinician judges it appropriate.
For endometriosis, dysmenorrhoea and PMS regimens commonly range 10–20 mg daily or 10 mg twice daily for specified cycle days.
Dose adjustments and precautions: avoid use in severe hepatic impairment and use with caution in the elderly; paediatric dosing is rare and specialist-led.
- Secondary amenorrhoea: 10 mg twice daily, days 11–25.
- Luteal support/infertility: 10 mg daily, days 14–25 or as clinic protocol; 3–6 cycles frequently used.
- Threatened abortion: Initial higher dosing then maintenance; clinician to document regimen.
Interactions overview
Dydrogesterone lacks significant androgenic or glucocorticoid activity and has relatively few well-documented pharmacokinetic interactions.
Enzyme inducers such as certain anticonvulsants and rifampicin may reduce progestogen levels and could potentially blunt clinical effectiveness.
No major food interactions are recorded, but alcohol and sedatives may worsen central side effects such as drowsiness or fatigue.
Suspected side effects, such as mood changes or thrombotic events, should be reported via the MHRA Yellow Card scheme.
In patients on polypharmacy—anticoagulants, antiepileptics or antidiabetics—clinical monitoring is sensible, with INR, glucose control and clinical response checked as appropriate.
Community pharmacists should record potential interactions in the PMR and advise patients about symptoms requiring urgent review, such as unilateral leg pain, sudden breathlessness or chest pain.
- Likely interacting classes: Enzyme inducers (monitor effectiveness), anticoagulants (monitor INR), anticonvulsants (dose adjustments may be required).
Comparable medicines and prescribing preferences
Clinically comparable progestogens used in the UK include micronised progesterone, norethisterone and medroxyprogesterone, each with distinct formulations and indications.
Micronised progesterone is commonly used for luteal support in fertility clinics and is available in oral and vaginal forms, with vaginal routes often preferred for direct endometrial effect.
Norethisterone is widely used for bleeding disorders and in HRT, while medroxyprogesterone remains an option for amenorrhoea and abnormal bleeding.
Pros of dydrogesterone include oral dosing convenience, a long clinical history and an absence of androgenic or glucocorticoid effects seen with some older progestins.
Cons include lack of a current UK licence and limited formulation options (oral only).
Frequently asked questions
Q: Can I get Duphaston on the NHS?
A: No — Duphaston has not been marketed in the UK since 2008 and NHS prescribing of dydrogesterone is therefore uncommon.
Q: Is dydrogesterone safe in pregnancy?
A: Its product information lists uses for threatened and habitual abortion with specific dosing, but clinicians must weigh benefits versus evidence and document informed consent.
Q: What are the common side effects?
A: The most reported effects are breast tenderness, headache, nausea, abdominal discomfort, menstrual irregularities and fatigue.
Q: What are suitable alternatives if Duphaston is unavailable?
A: Micronised progesterone, norethisterone or medroxyprogesterone may be used depending on indication; discuss route, safety and evidence with your clinician or pharmacist.
For urgent concerns, contact NHS 111, your GP or local pharmacist, and report suspected adverse reactions to the MHRA Yellow Card scheme.
Guidelines for proper use (pharmacist counselling + NHS patient portals)
Pharmacists should confirm the indication, check absolute and relative contraindications and review any interacting medicines before supply.
Counselling points to cover include the dosing schedule, missed-dose instructions (take as soon as remembered unless it is near the next dose) and the common side effects to expect.
Advise patients about red flags requiring urgent review: signs of venous thromboembolism (leg swelling, pain, sudden breathlessness), severe mood changes and symptoms of liver dysfunction.
For unlicensed or imported supplies, obtain and document written informed consent, explain the MHRA status and provide clear written information about the regimen.
Record counselling and follow-up plans in NHS patient portals or the electronic prescription message so fertility clinic protocols and primary-care records align.
Encourage patients to report suspected adverse reactions via the MHRA Yellow Card system and to contact their GP or pharmacist if they have questions about Duphaston.
- Counselling actions: Confirm indication, review cautions, explain dosing and storage (store below 30°C), document consent for imported products.
Delivery across the United Kingdom
| City | Region | Delivery Time |
|---|---|---|
| London | England | 9–21 days |
| Birmingham | England | 9–21 days |
| Manchester | England | 9–21 days |
| Glasgow | Scotland | 9–21 days |
| Leeds | England | 9–21 days |
| Liverpool | England | 9–21 days |
| Bristol | England | 9–21 days |
| Edinburgh | Scotland | 9–21 days |
| Sheffield | England | 9–21 days |
| Newcastle upon Tyne | England | 9–21 days |
| Leicester | England | 9–21 days |
| Coventry | England | 9–21 days |
| Belfast | Northern Ireland | 9–21 days |
| Brighton | England | 9–21 days |
| Plymouth | England | 9–21 days |



