
Femara
In brief
- Femara (letrozole) is a prescription-only medicine in the UK and should be obtained from a pharmacy or authorised supplier with a valid prescription; it is not legally intended for over-the-counter sale.
- Femara is used to treat hormone receptor‑positive breast cancer in postmenopausal women (early/adjuvant, extended adjuvant and advanced/metastatic disease); it is a non‑steroidal aromatase inhibitor that reduces oestrogen production by blocking the aromatase enzyme.
- The usual dose is 2.5 mg once daily for adults.
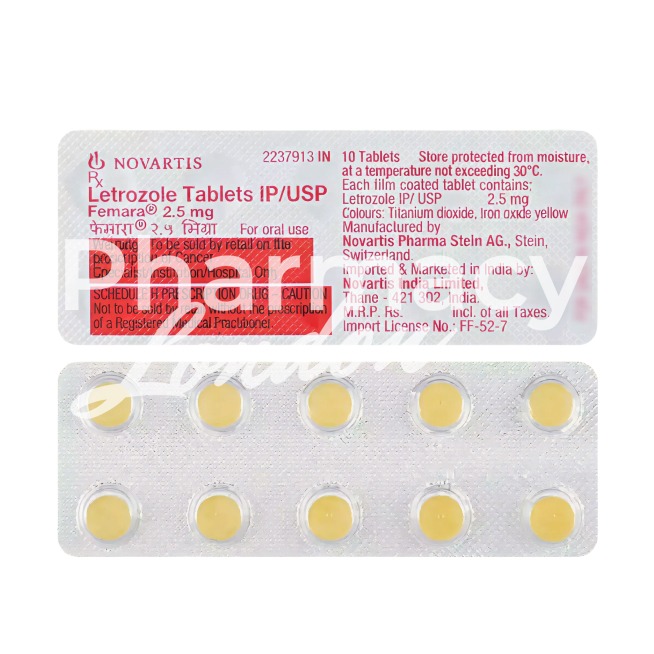
- Administration is oral: 2.5 mg film‑coated tablets taken once daily, with or without food.
- Letrozole is absorbed rapidly with plasma levels peaking in about 1 hour; aromatase inhibition begins within hours and biochemical effects are seen within days, though clinical benefits may take weeks to months.
- The elimination half‑life is approximately 2 days (around 40–60 hours); dosing is once daily and pharmacodynamic effects persist beyond 24 hours; adjuvant treatment is commonly given for 5 years (sometimes longer) and metastatic therapy continued until progression or unacceptable toxicity.
- Avoid excessive alcohol while taking Femara — alcohol can worsen liver function and bone health and may increase some risks associated with treatment; discuss safe drinking limits with your clinician.
- The most common side effect is hot flushes.
- Would you like to try Femara without a prescription?
Basic Femara information
- INN (international nonproprietary name): Letrozole
- Brand names available in the United Kingdom: Femara (2.5 mg tablets, 14 or 30 per pack)
- ATC code: L02BG04
- Forms & Dosages: oral film-coated tablets, 2.5 mg, in blister packs
- Manufacturers in the United Kingdom: Novartis Pharma AG (originator) and licensed generic producers including Sandoz
- Registration status in the United Kingdom: Prescription only
- OTC / Rx classification: Prescription only (Rx)
Legal status and availability in the UK
Femara (letrozole) is a prescription-only medicine (POM) in the UK.
In our online pharmacy, Femara is available without a prescription, with discreet delivery to the United Kingdom in 9–21 days.
Clinical effectiveness in the UK
Are patients in the NHS still prescribed Femara as a first-line adjuvant option?
Letrozole (Femara 2.5 mg tablets) is used in the UK for postmenopausal, hormone receptor–positive early and advanced breast cancer in line with its authorised indications.
Standard dosing is 2.5 mg once daily taken orally, with or without food, which simplifies adherence advice in primary and secondary care.
Treatment durations commonly cover five years in the adjuvant setting, with extensions considered to complete up to ten years when clinically indicated.
Common issues with aromatase inhibitors include joint pain, hot flushes and fatigue, which can affect continuation of therapy.
Comparisons across aromatase inhibitors focus on similar overall survival outcomes and differing side-effect profiles that guide individual choice.
Letrozole is noted for effective oestrogen suppression in postmenopausal patients and is interchangeable with generics.
Basic bone health monitoring and lipid checks are practical mitigation strategies to support long-term tolerability in NHS pathways.
When counselling patients, emphasise the once-daily regimen, the oral 2.5 mg formulation and when to seek review for troubling symptoms.
Indications and expanded uses (MHRA/NHS guidance and off‑label)
Do I qualify for Femara and are there any uses beyond the licence I should know about?
Letrozole is licensed for postmenopausal women with hormone receptor–positive breast cancer in adjuvant, extended adjuvant and first-line advanced/metastatic settings.
It is classified as prescription-only and is not authorised for premenopausal women, pregnancy or lactation.
Off‑label use occurs in specialist fertility clinics where letrozole is occasionally used for ovulation induction under strict medical supervision, but it is not licensed for infertility in the UK.
Absolute contraindications include pregnancy, breastfeeding and known hypersensitivity to letrozole or excipients.
Relative considerations include severe hepatic or renal impairment, and pre-existing osteoporosis, where specialist input is advised.
Prescribers should confirm postmenopausal status and consider a pregnancy test where clinically appropriate before initiating therapy.
Baseline checks useful at start of therapy are bone density assessment (DEXA), lipid profile and liver function tests when indicated.
A concise prescriber checklist improves safety: confirm menopause, check pregnancy status, baseline DEXA, baseline lipids and review concomitant medicines.
Composition and brand landscape (UK focus)
Which brands of letrozole will my pharmacy dispense and what should I expect in the pack?
The active ingredient is letrozole (INN), supplied primarily as 2.5 mg film-coated tablets for oral use.
Femara is the principal branded product in the UK and is supplied in blister packs.
Generics are widely available from manufacturers such as Sandoz and other licensed producers.
No injectable, topical or alternative formulations are authorised—only oral tablets are sold.
The ATC code L02BG04 places letrozole among aromatase inhibitors used in oncology.
Substitution considerations hinge on demonstrated bioequivalence and patient familiarity when switching brands or generics.
Electronic prescribing via EPS and hospital e-systems supports dispensing of branded Femara or approved generics according to local formulary rules.
Pharmacists should explain that the 2.5 mg oral tablet is the only authorised strength and advise on storage in original blister to protect from moisture.
Contraindications and special precautions
What are the absolute reasons not to take Femara and what needs close monitoring?
Absolute contraindications for letrozole are premenopausal status, pregnancy, breastfeeding and known hypersensitivity to the drug or its excipients.
Relative situations requiring caution include severe hepatic impairment and severe renal dysfunction, where clinical judgement is needed.
Pre-existing osteoporosis or significant osteopenia is a concern because aromatase inhibitors are associated with bone density loss over time.
Patients with a history of ischaemic heart disease should have cardiovascular risk factors reviewed before and during treatment.
Concurrent use of potent CYP450 inducers or inhibitors warrants specialist review for potential interaction effects.
Pharmacists should follow a short contraindication checklist: confirm menopausal status, ask about pregnancy/breastfeeding and check allergy history.
Baseline DEXA scanning for at-risk patients and periodic lipid checks are practical monitoring steps recommended in product information.
Advise patients about lifestyle measures for bone health including weight-bearing exercise and adequate calcium and vitamin D where appropriate.
Report any suspected adverse reactions to the MHRA Yellow Card scheme to contribute to ongoing pharmacovigilance.
Dosage guidelines (NHS‑aligned)
How is Femara dosed and what should patients do if they miss a tablet?
The standard adult dose of letrozole in NHS practice is 2.5 mg once daily taken orally with or without food.
This 2.5 mg film-coated tablet is the only authorised strength and is used across adjuvant, extended adjuvant and metastatic settings.
Adjuvant treatment is typically five years, with selected patients extending therapy to a total of ten years including prior tamoxifen exposure.
In metastatic disease letrozole is continued until disease progression or unacceptable toxicity occurs.
No routine dose adjustments are required for elderly patients or for mild to moderate hepatic or renal impairment.
Severe hepatic impairment and very low creatinine clearance (<10 ml/min) require specialist oversight and caution.
Paediatric use is not established and letrozole is not indicated in children.
If a dose is missed the patient should take it as soon as they remember unless it is near the time of the next dose; do not double up.
There is no specific antidote for overdose; treatment is supportive and symptomatic with monitoring.
Interactions overview (drugs, food, MHRA reports)
Could my other medicines change how Femara works or make side effects worse?
Letrozole has relatively few direct food interactions, but concurrent medicines can alter exposure via CYP450 pathways.
Potent CYP450 inducers or inhibitors should prompt specialist review because they may change letrozole plasma levels.
Additive adverse effect burdens are of practical concern, for example increased bone loss when corticosteroids are used concurrently.
Anticoagulant monitoring (such as INR checks with warfarin) is sensible if patients start or stop letrozole alongside these agents.
Certain antidepressants and lipid-lowering drugs are commonly co-prescribed; always check the BNF or local formulary for clinically relevant interactions.
Unregulated herbal remedies such as St John’s wort may act as CYP inducers and should be avoided without clinician approval.
Pharmacists should use a simple interaction checklist: review current medicines, flag potent CYP modulators, monitor INR and lipids as appropriate.
Report suspected interaction-related adverse events to the MHRA Yellow Card scheme to support real-world safety data.
Comparable medicines and prescribing preferences (NHS choices)
How does Femara compare with other aromatase inhibitors and tamoxifen in routine NHS practice?
Primary competitors to letrozole are anastrozole and exemestane, which are also aromatase inhibitors with similar indications in postmenopausal breast cancer.
Tamoxifen remains important for premenopausal patients and as sequential therapy where indicated.
Choice between letrozole, anastrozole and exemestane is often driven by side-effect profile, bone health considerations and local formulary preference.
Letrozole’s established efficacy and widespread availability make it a common selection in many NHS trusts.
Switching strategies for intolerable arthralgia commonly involve trialling an alternative aromatase inhibitor or reviewing adjunctive measures for symptom control with oncology input.
Pharmacists can use a short triage decision tree: confirm menopausal status, review current side effects, and refer to oncology for persistent intolerance.
All agents are prescription-only and should be dispensed with clear counselling on monitoring and when to seek specialist review.
Frequently asked questions
Can I get Femara without a prescription?
No—Femara and letrozole are prescription-only; UK pharmacies require a valid NHS or private prescription to supply the medicine.
Is letrozole safe in older adults?
Generally yes—no routine dose reductions are required for elderly patients, but monitor comorbidities such as bone health, lipids and liver function.
Can letrozole be used for fertility?
Letrozole is sometimes used off‑label for ovulation induction under specialist supervision, but it is not licensed for infertility in the UK.
What should I do if I miss a dose or experience side effects?
If a dose is missed, take it as soon as remembered unless it is close to the next dose; never double the dose.
Report side effects to your oncology team, GP or pharmacist, and consider Yellow Card reporting for suspected serious reactions.
Where can I find the correct dosing information?
The authorised dosing is 2.5 mg once daily; tablets should be stored below 30°C and kept in the original blister to protect from moisture.
Guidelines for proper use (pharmacist counselling and NHS support)
What should pharmacists cover when counselling a patient starting Femara?
Confirm the indication and postmenopausal status, review concomitant medicines for interactions and explain the dosing: 2.5 mg once daily with or without food.
Outline common side effects such as arthralgia, hot flushes and fatigue and set clear monitoring expectations for bone density, lipids and liver tests where appropriate.
Advise on storage: keep tablets below 30°C in the original blister and protect from moisture.
Provide written information and signpost to NHS patient portals, local oncology nurse specialists and community pharmacy follow‑ups.
Use a concise counselling checklist: indication, dosing, side-effect management, monitoring schedule and urgent referral triggers.
Monitoring intervals can be a practical plan: baseline DEXA where indicated, lipid check at baseline and at clinician discretion, and annual bone review for long-term therapy.
Trigger oncology referral for severe joint pain, new fractures or signs of hepatic dysfunction and document advice in EPS or the patient record.
Encourage patients and clinicians to report suspected adverse reactions to the MHRA Yellow Card scheme to support ongoing safety monitoring.
Delivery across the United Kingdom
| City | Region | Delivery Time |
|---|---|---|
| London | England | 9–21 days |
| Birmingham | England | 9–21 days |
| Manchester | England | 9–21 days |
| Glasgow | Scotland | 9–21 days |
| Liverpool | England | 9–21 days |
| Leeds | England | 9–21 days |
| Sheffield | England | 9–21 days |
| Bristol | England | 9–21 days |
| Newcastle Upon Tyne | England | 9–21 days |
| Edinburgh | Scotland | 9–21 days |
| Cardiff | Wales | 9–21 days |
| Belfast | Northern Ireland | 9–21 days |
| Plymouth | England | 9–21 days |



