
Florinef
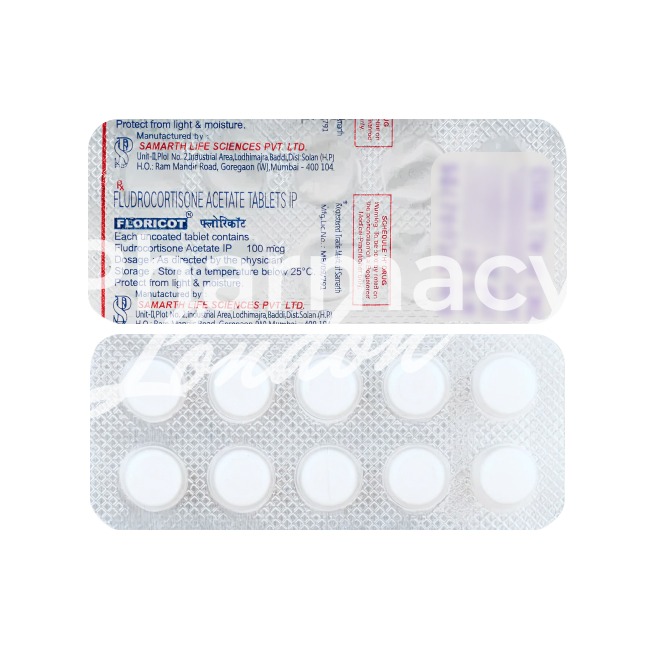
In brief
- In our pharmacy, you can buy Florinef without a prescription, with delivery in 9–21 days throughout the United Kingdom. Discreet and anonymous packaging.
- Florinef (fludrocortisone acetate) is a mineralocorticoid corticosteroid used mainly for Addison’s disease and salt‑losing congenital adrenal hyperplasia; it mimics aldosterone, promoting renal sodium retention, potassium excretion and water retention to maintain blood volume and blood pressure.
- The usual dose is generally 0.05–0.2 mg per day, most commonly 0.1 mg once daily (adjusted individually based on clinical response and electrolyte monitoring).
- Oral administration as a scored 0.1 mg tablet.
- The effect usually begins within a few hours, although meaningful clinical stabilisation of electrolytes and blood pressure may take several days.
- Duration of action is approximately 24 hours with once‑daily dosing; mineralocorticoid effects can persist into subsequent days depending on dose and individual response.
- Avoid or limit alcohol; alcohol may worsen gastrointestinal irritation and can aggravate fluid retention and blood pressure control while taking mineralocorticoids.
- The most common side effects are fluid retention and oedema with associated hypertension; other frequent issues include hypokalaemia, headache and weight gain.
- Would you like to try Florinef without a prescription?
Basic Florinef information
- INN (international nonproprietary name): fludrocortisone
- Active ingredient: Fludrocortisone 21‑acetate (fludrocortisone acetate)
- Drug class: mineralocorticoid corticosteroid
- CAS number: 514‑36‑3
- ATC code: H02AA02
- Forms and strengths: oral tablets containing 0.1 mg fludrocortisone acetate
- Registration status in the United Kingdom: prescription-only medicine (Rx)
- OTC / Rx classification: prescription-only medicine (Rx)
Legal status and availability in the UK
In our online pharmacy, Florinef is available with discreet delivery to the United Kingdom in 9–21 days.
Clinical effectiveness in the UK
How well does Florinef work in practice?
Within NHS endocrinology units, fludrocortisone contributes substantially to symptom control in primary adrenal insufficiency.
Combined with appropriate glucocorticoid replacement and patient education, it improves blood pressure and electrolyte stability.
In paediatric salt‑losing CAH, early specialist‑led fludrocortisone reduces salt supplementation needs and helps to stabilise growth trajectories when hypertension and excess growth are carefully monitored.
NHS monitoring pathways usually include baseline and periodic serum electrolytes, blood pressure and plasma renin measurements.
Monitoring frequency is stepped up during dose changes, pregnancy or any intercurrent illness.
Fludrocortisone acetate 0.1 mg tablets are the common formulation dispensed in NHS practice and are used to tailor low‑dose regimens.
Indications and expanded uses
What is Florinef licensed for, and when is it used off‑label?
In the United Kingdom, fludrocortisone is licensed principally for primary adrenal insufficiency (Addison’s disease) and salt‑losing congenital adrenal hyperplasia (adrenogenital syndrome).
Off‑label specialist use includes adjunctive therapy for selected forms of orthostatic hypotension that do not respond to non‑pharmacological measures.
Paediatric licensed use covers salt‑losing CAH, and dose adjustments in children are specialist‑led with close monitoring.
In the UK, fludrocortisone is a prescription-only medicine, so initiation and dose changes remain clinician responsibilities.
Clinicians using off‑label regimens should document MHRA guidance, local trust policy and informed consent in the patient record.
Fludrocortisone acetate is typically supplied as 0.1 mg scored tablets, which guides specialist dosing and titration.
Composition and brand landscape
Which products will your local pharmacy actually dispense?
The active ingredient is fludrocortisone 21‑acetate, commonly referred to clinically as fludrocortisone acetate.
Florinef is the best-known brand name; generic fludrocortisone acetate tablets are also available.
In the United Kingdom, generic scored 0.1 mg tablets are commonly dispensed and are favoured on NHS formularies unless a brand is specifically requested for clinical reasons.
The drug’s ATC classification is H02AA02, which supports placement in hospital and community formularies.
Packaging typically uses 0.1 mg scored tablets so pharmacists can advise on careful dose splitting when lower microdoses are required.
Pharmacies should check bioequivalence when substituting manufacturers.
Prescribers should reserve “no substitution” directions for clinically justified cases only.
Contraindications and special precautions
Who should be cautious before starting Florinef?
Absolute contraindications include known hypersensitivity to fludrocortisone or any excipients in the tablet.
Caution is required in patients with uncontrolled hypertension, heart failure or severe renal impairment because of the risk of fluid retention and sodium overload.
Elderly patients carry a higher risk of hypertensive events and heart failure exacerbation, so start low and monitor closely.
Pregnancy and breastfeeding require specialist review and careful documentation of risk and benefit.
Patients with diabetes or osteoporosis should be counselled, since corticosteroid activity may worsen glycaemic control or bone health.
Lifestyle advice includes avoiding excessive dietary salt, moderating alcohol intake and watching for reduced exercise tolerance if oedema develops.
Driving should be reviewed if dizziness, syncope or visual disturbance are present.
Oedema and hypertension are the main adverse reactions to watch for; suspected reactions can be reported via the Yellow Card scheme.
Dosage guidelines
How much Florinef should a patient expect to take?
Typical NHS adult starting doses are 0.05–0.1 mg (50–100 mcg) once daily with titration to clinical effect and plasma renin activity.
Some patients stabilise on 0.1 mg every other day, while others require daily dosing depending on symptoms and laboratory results.
Paediatric dosing in salt‑losing CAH is weight‑based and must be supervised by a paediatric endocrinologist with electrolyte and growth checks.
Elderly patients usually start at the lower end of the dosing range and increase cautiously because of cardiovascular risk.
Sick‑day rules apply: during intercurrent illness, surgery or dehydration clinicians should review doses and monitor more frequently, and coordinate any glucocorticoid adjustments.
Severe renal impairment and significant cardiac disease require specialist review before initiation.
Prescriptions should specify dose in mg and mcg where possible and include monitoring intervals for blood pressure, electrolytes and plasma renin.
Common monitoring schedule: baseline bloods and blood pressure, repeat checks at 1–2 weeks after initiation or dose change, then as clinically indicated.
Interactions overview
Which medicines and habits can change how Florinef works?
The main interaction concerns are additive effects on blood pressure and potassium balance.
Concurrent use of sympathomimetics and some NSAIDs can increase hypertensive risk when combined with fludrocortisone.
Potassium‑wasting diuretics may worsen hypokalaemia, while potassium‑sparing diuretics can mask the expected electrolyte changes of mineralocorticoid therapy.
No single‑meal food interactions are established, but excessive dietary sodium will blunt fludrocortisone’s intended effect.
Alcohol can worsen blood‑pressure control and fluid regulation, so counsel moderation.
Complex drug combinations can precipitate oedema or electrolyte disturbance.
For older adults on multiple drugs, pharmacist medication review and enhanced monitoring are recommended to reduce risk.
Comparable medicines and prescribing preferences
Are there true alternatives to fludrocortisone for mineralocorticoid replacement?
Fludrocortisone is the standard mineralocorticoid replacement and there are no widely used direct pharmacological alternatives with equivalent potency in routine NHS practice.
Management alternatives focus on non‑pharmacological measures such as salt supplementation and fluid management to help orthostatic symptoms.
In specialist cases of orthostatic hypotension, adjunctive agents such as midodrine may be considered but they do not replace mineralocorticoid replacement in adrenal insufficiency.
NHS trust prescribing preferences are influenced by availability, generic bioequivalence and patient tolerability.
Advantages include established evidence for symptomatic control, plasma renin normalisation and once‑daily dosing options.
Disadvantages include the potential to cause hypertension, oedema and hypokalaemia and the need for lifelong monitoring.
Frequently asked questions
- Q: Can I stop Florinef if I feel better?
- A: No — stopping without clinician advice risks salt loss and adrenal crisis in adrenal insufficiency.
- Q: What if I miss a dose?
- A: Take the missed dose as soon as you remember unless it is almost time for the next dose; never double up and contact NHS 111 or your endocrine team if unsure.
- Q: Will Florinef affect my blood tests or travel plans?
- A: Yes — it affects electrolytes and blood pressure; carry a steroid card, arrange monitoring before travel and plan sick‑day measures; avoid dehydration on long flights.
- Q: Can I get repeat prescriptions electronically?
- A: Yes, but ensure routine monitoring is maintained through NHS services; pharmacists may ask for recent review evidence before supplying repeats.
Definitions:
- Steroid card: a wallet card that lists steroid therapy and sick‑day guidance for emergency use.
- Sick‑day rules: practical steps for adjusting care and seeking help during acute illness, vomiting or diarrhoea.
Practical guidelines for proper use
What should pharmacists and patients cover at every supply?
Pharmacists should confirm the indication, typically Addison’s disease or CAH, before supply and discuss expected benefits and common side‑effects such as oedema, raised blood pressure and low potassium.
Clear advice on dose timing and what to do if vomiting or unable to take oral medicines must be given, together with sick‑day rules and steroid card reminders.
Pharmacies supplying by electronic prescription should include alerts for baseline and follow‑up blood tests and coordinate with primary care and specialist endocrine teams for shared care arrangements.
Point patients to NHS patient portals for result access, local endocrine nurse specialists and relevant patient charities for peer support.
Document counselling, supply substitutions and any clinical queries in the patient record to support continuity of care.
Suggested pharmacist checklist: confirm diagnosis, review blood pressure and recent electrolytes, discuss side‑effects, advise on sick‑day rules and ensure steroid card is carried.
Delivery across the United Kingdom
| City | Region | Delivery Time |
|---|---|---|
| London | England | 9–21 days |
| Birmingham | England | 9–21 days |
| Manchester | England | 9–21 days |
| Leeds | England | 9–21 days |
| Glasgow | Scotland | 9–21 days |
| Edinburgh | Scotland | 9–21 days |
| Bristol | England | 9–21 days |
| Liverpool | England | 9–21 days |
| Sheffield | England | 9–21 days |
| Newcastle Upon Tyne | England | 9–21 days |
| Nottingham | England | 9–21 days |
| Leicester | England | 9–21 days |
| Cardiff | Wales | 9–21 days |
| Swansea | Wales | 9–21 days |



