
Fluoxetine
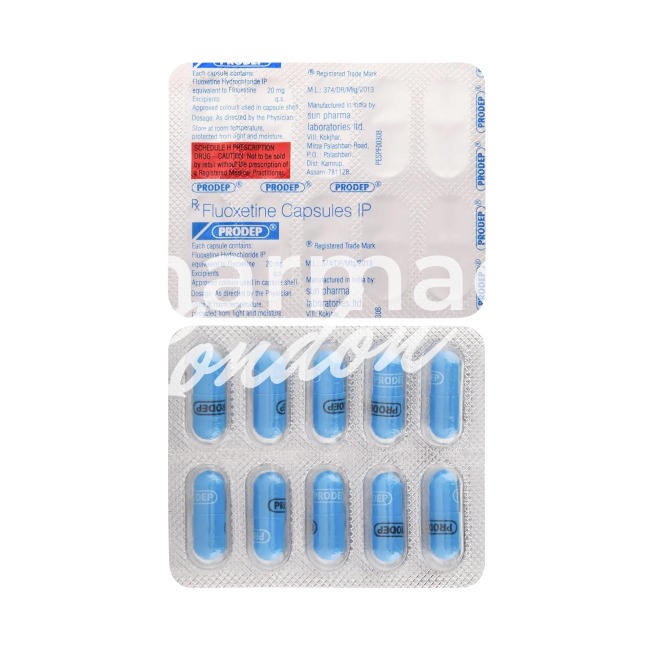
In brief
- Fluoxetine is a prescription-only medicine (POM) in the UK and should be obtained from a pharmacy with a valid prescription; consult a prescriber or pharmacist before use.
- Fluoxetine is an SSRI antidepressant used to treat major depressive disorder and other conditions such as obsessive–compulsive disorder and bulimia nervosa; it works by selectively inhibiting the serotonin reuptake transporter, increasing serotonin availability in the brain.
- The usual adult starting dose is 20 mg once daily for depression, with typical maintenance doses 20–40 mg daily and some patients requiring up to 60 mg daily; dosing for other indications and for children/adolescents differs and should follow a prescriber’s guidance.
- Administration is oral: capsules, tablets (including orodispersible tablets), and oral solution (commonly 20 mg/5 mL) are available.
- Some patients notice initial changes (e.g. in sleep or appetite) within 1–2 weeks, but meaningful antidepressant effects usually take several weeks to appear; full benefit often requires 4–6 weeks or longer.
- Fluoxetine has a long elimination profile: fluoxetine’s half-life is typically around 1–4 days after chronic dosing, and its active metabolite norfluoxetine has a half-life of about 7–15 days, so pharmacological effects can persist for days to weeks after stopping.
- Avoid or limit alcohol while taking fluoxetine; alcohol can increase drowsiness, worsen mood symptoms and amplify other side effects.
- The most common side effect is nausea (other frequent effects include headache, insomnia or somnolence, and sexual dysfunction).
- Would you like to try fluoxetine without a prescription?
Legal status and availability in the UK
In our online pharmacy, fluoxetine is available without a prescription, with discreet delivery to the United Kingdom in 9‑21 days.
Basic fluoxetine information
- INN (international nonproprietary name): fluoxetine
- Brand names available in the United Kingdom: Prozac; generic fluoxetine capsules and oral solution
- ATC code: N06AB03
- Forms and strengths: hard capsules 10 mg, 20 mg, 30 mg, 40 mg, 60 mg; oral solution 20 mg/5 mL; orodispersible tablets 20 mg
- Manufacturers in the United Kingdom: Not specified
- Registration status in the United Kingdom: Authorised; prescription-only
- OTC / Rx classification: Prescription only (POM)
Clinical effectiveness in the UK
Can fluoxetine reduce depressive symptoms for people in the NHS?
Fluoxetine produces clinically meaningful reductions in depressive symptoms for many patients, particularly those with moderate to severe major depressive disorder and comorbid obsessive‑compulsive features.
Response rates are comparable to those of other first‑line SSRIs, and some GPs prefer fluoxetine where its pharmacology fits the patient profile.
Improvement may be gradual at first, with sustained benefit when treatment is taken as prescribed.
Common side effects that can affect treatment include sexual dysfunction and sleep disturbance while on fluoxetine.
Oral formulations such as capsules and the oral solution 20 mg/5 mL support flexible dosing and help patients with swallowing difficulties.
Outcome measures commonly used
- PHQ‑9: Patient Health Questionnaire for depression severity.
- GAD‑7: Generalised Anxiety Disorder scale for comorbid anxiety assessment.
- IES or Y‑BOCS: For obsessive‑compulsive features in specialist settings.
Indications and expanded uses (MHRA and NHS practice)
What is fluoxetine licensed for in the UK?
In the UK, fluoxetine is licensed for major depressive episodes, obsessive‑compulsive disorder and bulimia nervosa (as an adjunct to psychotherapy).
Off‑label uses and how they are managed.
Off‑label uses in UK practice can include chronic pain syndromes or severe fatigue where a recognised comorbid mood disorder exists, but these are usually started in secondary care and documented carefully.
Prescribers follow MHRA and British National Formulary (BNF) guidance and document rationale for any non‑licensed use in GP records and shared‑care agreements when a specialist initiates treatment.
- Licensed uses: major depressive episodes, obsessive‑compulsive disorder and bulimia nervosa.
- Common off‑label uses: chronic pain with comorbid mood disorder; severe fatigue where mood disorder is implicated (specialist initiation).
Prescriber checklist before starting fluoxetine:
- Confirm licensed indication or document off‑label rationale.
- Check current medications for interactions and review previous antidepressant history.
- Discuss monitoring plan, pregnancy plans and informed consent for risks and benefits.
- Arrange follow‑up and shared‑care documentation if applicable.
Composition, brands and formulations (UK market)
What forms of fluoxetine are available in UK practice?
The INN is fluoxetine and the commonly used salt in product literature is fluoxetine hydrochloride.
Routes of administration and presentations.
Available oral presentations include hard capsules across multiple strengths and an oral solution at 20 mg/5 mL, as described in UK SmPCs.
| Brand / type | Common strengths | Notes |
|---|---|---|
| Prozac | 10 mg, 20 mg, 30 mg, 40 mg, 60 mg; oral solution 20 mg/5 mL | Recognised brand in the UK; SmPCs confirm capsule strengths and oral solution |
| Generic fluoxetine | 10 mg, 20 mg, 30 mg, 40 mg, 60 mg; oral solution 20 mg/5 mL | Widely dispensed; NHS routinely accepts generics unless brand specified |
- INN vs brand: INN refers to the generic nonproprietary name fluoxetine; brand names include Prozac in the UK.
- Oral solution: 20 mg/5 mL; clear, peppermint odour and contains sucrose as excipient.
Contraindications and special precautions
Who should avoid fluoxetine?
Absolute contraindications include concurrent use of monoamine oxidase inhibitors (MAOIs) and known hypersensitivity to fluoxetine or its excipients.
Pregnancy and breastfeeding considerations.
Special caution is required during pregnancy and breastfeeding and UK guidance advises a careful risk–benefit discussion and documentation.
High‑risk groups in UK practice.
Elderly patients have a higher risk of hyponatraemia and falls and require monitoring.
Adolescents and young adults should be monitored for emergent suicidal ideation, following MHRA guidance.
People with bipolar disorder require careful assessment.
There is a risk of manic switch when antidepressants are used without mood stabilisation.
| Age group | Key precaution |
|---|---|
| Adolescents / young adults | Increased monitoring for suicidality; specialist involvement where needed |
| Older adults | Monitor electrolytes for hyponatraemia; consider lower starting dose |
Practical points for patients.
Discuss driving and operating machinery if dizziness or sedation occurs and advise minimising alcohol due to additive central effects.
Due to the long half‑life, abrupt withdrawal is less common, but dose tapering is still recommended to minimise discontinuation symptoms.
Dosage guidelines (NHS‑aligned)
How is fluoxetine typically started and adjusted on the NHS?
Standard adult dosing usually starts at 20 mg once daily for depression, with titration based on response and tolerability.
Typical maximums used in practice.
Doses up to 40–60 mg daily are used for certain indications under clinician supervision and depending on clinical response.
Children and adolescents.
Fluoxetine is often the SSRI of choice for moderate to severe depression in children and adolescents, started under specialist supervision with age‑appropriate dosing and monitoring.
Older adults and organ impairment.
Older adults may start at lower doses because of hyponatraemia risk.
Renal impairment rarely requires dose change, but hepatic impairment needs caution and specialist advice.
Stepwise initiation and monitoring
- Start: 20 mg once daily for most adults.
- Review: clinical review at two weeks for tolerability and again at four and six weeks for response.
- Titrate: increase dose if insufficient response, under clinician guidance, up to commonly 40–60 mg where indicated.
- Maintenance: continue at least six months after remission on first episode; longer for recurrent depression.
| Patient group | Starting dose | Usual maintenance range |
|---|---|---|
| Adults | 20 mg once daily | 20–60 mg daily depending on indication |
| Children / adolescents | Specialist‑guided dosing (lower starting dose) | Adjusted by specialist; monitoring for suicidality |
| Older adults | Lower starting dose recommended | Adjusted with caution; monitor electrolytes |
Interactions overview (clinical and everyday)
What drugs should not be combined with fluoxetine?
Fluoxetine interacts with several medicines of clinical importance, including other serotonergic agents which increase the risk of serotonin syndrome.
MAOIs are contraindicated due to the risk of severe serotonergic toxicity.
Bleeding risk and CYP interactions.
Fluoxetine can increase bleeding risk when combined with antiplatelet agents or anticoagulants and is a potent CYP2D6 inhibitor which affects drugs metabolised via that pathway.
Food and alcohol.
There are limited direct food interactions, but alcohol should be avoided or minimised because of additive CNS and mood effects.
| Drug or class | Mechanism | Clinical action |
|---|---|---|
| MAOIs | Serotonergic potentiation | Contraindicated; observe washout periods |
| Other SSRIs / SNRIs / triptans | Increased serotonergic activity | Avoid or monitor for serotonin syndrome |
| Warfarin / antiplatelets | Increased bleeding risk | Monitor INR and bleeding signs; consider alternative therapy |
| Drugs metabolised by CYP2D6 (e.g. some antipsychotics) | Fluoxetine inhibits CYP2D6 | Check doses and monitor for increased effects or toxicity |
Interaction‑related adverse events are more likely in older adults with polypharmacy, so a careful medication review is needed before prescribing and dispensing.
In UK practice, GPs and pharmacists routinely use electronic decision‑support tools to flag interactions prior to dispensing.
Comparable medicines and prescribing preferences
What are the alternatives to fluoxetine on NHS formularies?
NHS formularies list several SSRIs including sertraline, citalopram and escitalopram and SNRIs such as venlafaxine and duloxetine as alternatives.
Choosing between options is individualised.
Selection depends on side‑effect profiles, comorbidity, interaction potential and prior response.
Where fluoxetine may be favoured.
Fluoxetine’s longer half‑life and the availability of an oral solution make it a good option where adherence is variable or in patients with swallowing difficulties.
Clinician checklist for matching drug to patient priorities
- Review previous antidepressant response and tolerability.
- Consider patient priorities such as sleep, sexual side‑effects and weight.
- Check for interacting medicines and metabolic considerations.
- Consider the monitoring burden for long‑term treatment.
| Drug | Onset | Typical side‑effects | Metabolic / interaction notes |
|---|---|---|---|
| Fluoxetine | Similar to other SSRIs (2–4 weeks initial effect) | Sexual dysfunction, sleep changes; lower abrupt withdrawal risk | Inhibits CYP2D6; long half‑life |
| Sertraline | Rapid onset for anxiety symptoms in some patients | GI symptoms common initially | Fewer CYP interactions than fluoxetine |
| Citalopram / Escitalopram | Comparable onset | Risk of QT prolongation at higher doses (citalopram) | Escitalopram often preferred for tolerability |
FAQ — common NHS patient questions
How long until fluoxetine starts to work?
Initial effects are often noticed within two to four weeks, with full response commonly taking six to 12 weeks.
Can I drink alcohol while taking fluoxetine?
It is best to minimise alcohol while establishing treatment due to additive sedation and potential mood effects.
What if I miss a dose?
Take the missed dose as soon as remembered unless it is near the time for the next dose, and do not double up doses.
How long will I need fluoxetine?
NHS guidance often recommends continuing for six months after remission for a first episode, with longer treatment for recurrent depression.
Where can I get reliable information?
Refer to MHRA safety updates and NHS patient portals for up‑to‑date advice and guidance on side‑effects and monitoring.
Practical guidelines for proper use (pharmacist and GP counselling)
What should pharmacists and GPs tell patients when dispensing fluoxetine?
Confirm the indication and review prior antidepressant history and current medications before supply.
Ask about pregnancy plans and provide a clear risk–benefit discussion if relevant.
Explain common side‑effects such as nausea, sleep changes and sexual dysfunction and give practical advice on management.
Emphasise adherence and the typical timeline for effect.
Warn about serious interaction risks such as MAOIs and anticoagulants and encourage use of NHS electronic decision‑support tools.
Use NHS patient portals and the MHRA Yellow Card scheme for reporting adverse events and encourage patients to report any concerning symptoms promptly.
Counselling checklist for dispensing fluoxetine
- Confirm dose form and strength (capsule or oral solution 20 mg/5 mL) and provide written instructions.
- Explain expected timeline: 2–4 weeks for early effects, 6–12 weeks for full response.
- Discuss common side‑effects and when to seek urgent review (suicidal thoughts, severe hyponatraemia signs, serotonin syndrome).
- Arrange appropriate follow‑up with GP or mental‑health services if inadequate response or intolerable side‑effects.
Definitions for patients and clinicians.
- Adherence: Taking the medicine exactly as prescribed on an ongoing basis.
- Remission: Resolution or near‑resolution of depressive symptoms as measured by validated scales such as PHQ‑9.
Example instructions for patients:
"Start one 20 mg capsule each morning, swallow with water, and continue daily even if you feel better unless advised otherwise by your prescriber."
"If you experience worrying symptoms such as new thoughts of harming yourself, seek urgent advice from your GP or NHS services."
Delivery across the United Kingdom
| City | Region | Delivery Time |
|---|---|---|
| London | England | 9–21 days |
| Birmingham | England | 9–21 days |
| Manchester | England | 9–21 days |
| Glasgow | Scotland | 9–21 days |
| Edinburgh | Scotland | 9–21 days |
| Belfast | Northern Ireland | 9–21 days |
| Cardiff | Wales | 9–21 days |
| Leeds | England | 9–21 days |
| Sheffield | England | 9–21 days |
| Newcastle Upon Tyne | England | 9–21 days |
| Nottingham | England | 9–21 days |
| Plymouth | England | 9–21 days |
| Aberdeen | Scotland | 9–21 days |
| Liverpool | England | 9–21 days |



