
Glucovance
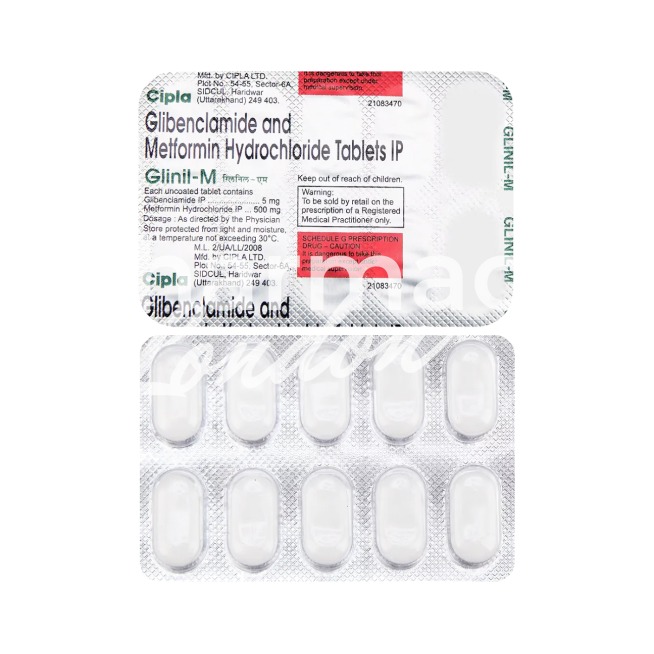
In brief
- In our pharmacy, you can buy Glucovance without a prescription, with delivery in 9–21 days throughout the United Kingdom. Discreet and anonymous packaging.
- Glucovance is used to treat type 2 diabetes as an adjunct to diet and exercise; it combines glibenclamide (a sulfonylurea that stimulates pancreatic insulin secretion) and metformin (a biguanide that reduces hepatic glucose production and improves insulin sensitivity).
- The usual dose varies by formulation; common strengths are 500 mg metformin/2.5–5 mg glibenclamide or 1000 mg/5 mg. Typical regimens start with one tablet once daily with a meal and may be increased to one tablet twice daily, with total daily metformin usually up to 2000 mg and glibenclamide 2.5–20 mg depending on response and tolerability.
- The form of administration is film‑coated oral tablets taken with food to reduce gastrointestinal side effects and lower risk of hypoglycaemia.
- The effect on blood glucose usually begins within 1–2 hours (glibenclamide onset), though metformin’s full glucose‑lowering benefits may take several days to weeks.
- The duration of action is typically about 12–24 hours depending on dose and individual response; steady glycaemic control develops with continued use.
- Do not consume alcohol or limit intake, as alcohol increases the risk of lactic acidosis with metformin and can worsen hypoglycaemia risk from glibenclamide.
- The most common side effect is hypoglycaemia (low blood sugar); gastrointestinal upset (nausea, diarrhoea) is also frequently reported due to metformin.
- Would you like to try Glucovance without a prescription?
Basic Glucovance information
- INN (international nonproprietary name): glibenclamide/metformin
- Brand names available in the United Kingdom: Not specified
- ATC code: A10BD02
- Forms and strengths: film‑coated oral tablets with fixed combinations, e.g. 500 mg/2.5 mg, 500 mg/5 mg and 1000 mg/5 mg (metformin/glibenclamide).
- Manufacturers in the United Kingdom: Not specified
- Registration status in the United Kingdom: Not specified
- OTC / Rx classification: Not specified
Legal status and availability in the UK
In our online pharmacy, Glucovance is available without a prescription, with discreet delivery to the United Kingdom in 9–21 days.
Clinical effectiveness in the UK
Patients want clear outcomes: will one tablet help me reach targets more easily?
NHS practice judges effectiveness by glycaemic control (HbA1c), hypoglycaemia incidence and adherence.
Fixed‑dose combinations like Glucovance produce clinically meaningful HbA1c reductions when added to diet and exercise for adults with type 2 diabetes uncontrolled on monotherapy.
A single tablet improves convenience, but mild hypoglycaemia and occasional gastrointestinal upset are more common than with metformin alone.
Primary‑care monitoring typically occurs every three to six months after initiation and focuses on HbA1c, eGFR and weight.
- HbA1c targets: Local targets vary, commonly aiming for individualised control per NHS guidance.
- eGFR thresholds: Renal function guides metformin dosing and continuation.
| Outcome | NHS metric |
|---|---|
| Glycaemic control | HbA1c reduction when added to lifestyle |
| Safety | Documented increased mild hypoglycaemia vs metformin alone |
| Adherence | Single‑tablet format often improves adherence |
Indications and expanded uses
People ask whether Glucovance can be prescribed beyond the licence.
Use follows the licence: adults with type 2 diabetes as an adjunct to diet and exercise when monotherapy with metformin or a sulfonylurea is insufficient, or when patients are already stable on a free combination.
Some private clinics may consider off‑label insulin‑sparing strategies in selected patients, but standard NHS guidance favours licensed indications and local formulary policy adherence.
Before prescribing, clinicians should check the product information and local formularies and record the rationale in the clinical notes.
- Licensed indications: Adjunct to diet and exercise for adults with type 2 diabetes when monotherapy is insufficient.
- Common off‑label scenarios: Considered rarely in private practice for insulin‑sparing approaches with careful monitoring.
Composition and brand landscape
Patients often want to know what is in the tablet and whether generics are available.
Glucovance is a fixed‑dose combination of glibenclamide — a sulfonylurea — and metformin hydrochloride — a biguanide.
The INN is glibenclamide/metformin.
| INN | Class | Common strengths |
|---|---|---|
| Glibenclamide/metformin | Sulfonylurea + biguanide | 500 mg/2.5 mg, 500 mg/5 mg, 1000 mg/5 mg |
- INN: International Nonproprietary Name.
- ATC: Anatomical Therapeutic Chemical classification (A10BD02).
Contraindications and special precautions
Patients worry about who should not take this medicine and when to be cautious.
Contraindications and precautions centre on renal impairment due to metformin accumulation and the hypoglycaemia risk from the sulfonylurea component.
Conditions associated with lactic acidosis risk and advanced hepatic disease are relevant when considering metformin use.
High‑risk groups include older people with frailty, patients with advanced renal or hepatic disease, and pregnancy or breastfeeding where sulfonylureas are generally avoided.
Practical lifestyle cautions in UK guidance include avoiding excessive alcohol, ensuring carbohydrate intake when driving or working at height, and following DVLA guidance if hypoglycaemia risk affects driving entitlement.
- Contraindications: Significant renal impairment, known hypersensitivity to components, acute or chronic metabolic acidosis.
- High‑risk groups: Older frail adults, advanced hepatic disease, pregnancy/breastfeeding.
Hypoglycaemia is a key safety concern for sulfonylurea‑containing combinations.
Dosage guidelines
Patients regularly ask what dose to start and how to change it safely.
Typical dosing follows the product licence and local formularies: start with the lowest effective fixed dose and titrate according to glycaemic response and tolerability.
Clinicians must pay attention to renal function when adjusting metformin‑containing regimens.
In UK practice, metformin monotherapy is commonly initiated first, with combinations such as Glucovance introduced if targets remain unmet.
Dose adjustments are advised for elderly patients, those with eGFR decline, and when interacting medicines are present.
When switching from free combination therapy to a fixed‑dose product, ensure equivalent total daily doses are matched.
- Start low, titrate by response and tolerability.
- Check eGFR before and after initiation; adjust if renal function declines.
| Switch scenario | Conversion note |
|---|---|
| Free metformin + glibenclamide → Glucovance | Match total daily metformin and glibenclamide doses when selecting fixed‑dose strength. |
Interactions overview
People often ask which medicines or foods affect their tablets.
Key drug interactions include agents that potentiate hypoglycaemia, such as other insulin secretagogues and certain antibiotics, and drugs that affect metformin clearance like cationic agents and contrast media.
Drugs that alter sulfonylurea metabolism — notably CYP inhibitors or inducers — can change glibenclamide exposure and hypoglycaemia risk.
Alcohol increases the risk of lactic acidosis with metformin and may worsen hypoglycaemia with sulfonylureas.
Caffeine‑containing drinks can mask some hypoglycaemia symptoms in certain people and should be considered when counselling drivers.
Hypoglycaemia and gastrointestinal intolerance are the most common adverse effects of this combination.
| Drug class | Interaction risk |
|---|---|
| Insulin secretagogues / insulin | Increased hypoglycaemia |
| Fluoroquinolone antibiotics | Can potentiate hypoglycaemia |
| Contrast media / cationic drugs | May affect metformin clearance; consider withholding metformin around some procedures |
| CYP inhibitors/inducers | Alter sulfonylurea metabolism and hypoglycaemia risk |
Food and drink: avoid excessive alcohol and be cautious with fasting or very low‑carbohydrate diets.
Comparable medicines and prescribing preferences
Clinicians weigh risk and comorbidity when choosing alternatives.
NHS alternatives to glibenclamide/metformin combinations include metformin plus other sulfonylureas, DPP‑4 inhibitors, SGLT2 inhibitors and GLP‑1 receptor agonists depending on individual comorbidity and weight targets.
Prescribing preference increasingly reflects cardiovascular and renal outcome evidence, which can favour SGLT2 or GLP‑1 agents in appropriate patients, while sulfonylurea/metformin combinations remain an option for many without those specific indications.
Key pros and cons are rapid HbA1c lowering versus higher hypoglycaemia risk and potential weight gain.
| Option | Advantages | Disadvantages |
|---|---|---|
| Glibenclamide/metformin | Effective HbA1c lowering | Higher hypoglycaemia risk; modest weight gain |
| SGLT2 inhibitor | Cardiorenal benefits for some patients | Different side‑effect profile |
| GLP‑1 receptor agonist | Weight loss potential; cardiorenal benefits | Injectable for many options |
- Clinician checklist: consider comorbidity, hypoglycaemia risk and weight goals when choosing therapy.
FAQ
- Can I drive while taking Glucovance?
Yes if you have no hypoglycaemia episodes, but inform the DVLA where appropriate and carry hypos treatment.
- What monitoring is needed?
Regular HbA1c and renal (eGFR) checks are required — typically about three months after any change, then as per local policy.
- Can I drink alcohol?
Avoid excessive alcohol due to metformin‑related lactic acidosis risk and increased hypo risk with sulfonylureas.
- Is one tablet better than two?
Fixed‑dose convenience can improve adherence but reduces dose flexibility compared with separate agents.
Guidelines for proper use
Pharmacists should follow a structured counselling approach to keep patients safe and informed.
Confirm indication and allergies, explain the dual mechanism (sulfonylurea plus biguanide), and advise on dosing and timing.
Explain signs of hypoglycaemia and how to treat it promptly with fast‑acting carbohydrate and when to seek help.
Stress the importance of renal monitoring and when to withhold metformin, for example around some contrast imaging procedures.
Document advice on the NHS patient record, promote NHS App access and local diabetes education programmes for ongoing support.
- Set up EPS nominations and consider repeat dispensing for stable chronic users.
- Provide written hypoglycaemia action plan and clear instructions on when to contact the GP.
Delivery across the United Kingdom
| City | Region | Delivery Time |
|---|---|---|
| London | Greater London | 9–21 days |
| Birmingham | West Midlands | 9–21 days |
| Manchester | Greater Manchester | 9–21 days |
| Glasgow | Scotland | 9–21 days |
| Leeds | West Yorkshire | 9–21 days |
| Liverpool | Merseyside | 9–21 days |
| Edinburgh | Scotland | 9–21 days |
| Bristol | South West England | 9–21 days |
| Sheffield | South Yorkshire | 9–21 days |
| Newcastle Upon Tyne | North East England | 9–21 days |
| Belfast | Northern Ireland | 9–21 days |
| Cardiff | Wales | 9–21 days |
| Leicester | Leicestershire | 9–21 days |
| Coventry | West Midlands | 9–21 days |



