
Hydroxychloroquine
In brief
- Hydroxychloroquine is a prescription-only medicine (POM) in the UK; legitimate supply requires a clinician’s assessment and monitoring.
- Hydroxychloroquine is used for the treatment and prevention of malaria, and for long-term management of autoimmune conditions such as rheumatoid arthritis and systemic lupus erythematosus. It is an antimalarial aminoquinoline that is thought to work by interfering with parasite growth and by modulating immune and inflammatory activity.
- The usual dose depends on the condition: for malaria treatment, 800 mg initially, then 400 mg at 6, 24 and 48 hours; for malaria prevention, 400 mg once weekly; for rheumatoid arthritis or lupus, commonly 200–400 mg daily. Doses should be adjusted to clinical response, body weight, and kidney or liver function.
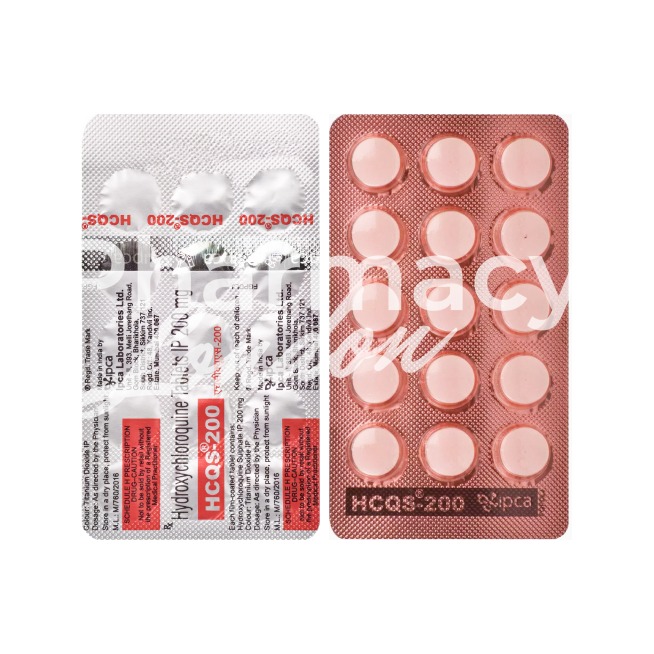
- Hydroxychloroquine is taken by mouth as tablets, typically 200 mg strength.
- It usually starts to work within hours for malaria, while improvement in rheumatoid arthritis or lupus may take several days to several weeks.
- Its duration of action is long, allowing once-daily or weekly dosing depending on the indication; for chronic autoimmune conditions, benefits may last as long as treatment is continued.
- Alcohol should be avoided or limited, as it may increase the risk of stomach upset and can add strain when taking medicines that require long-term monitoring.
- The most common side effects are nausea, vomiting, diarrhoea, abdominal pain, loss of appetite, skin rash, and itching. Visual disturbance can also occur and needs prompt medical review.
- Would you like to try hydroxychloroquine without a prescription?
Legal status and availability in the UK
In our online pharmacy, hydroxychloroquine is available without a prescription, with discreet delivery to the United Kingdom in 9–21 days.
Basic hydroxychloroquine information
- INN (international nonproprietary name): Hydroxychloroquine
- Brand names available in the United Kingdom: Plaquenil; Quinoric
- ATC code: P01BA02
- Forms and strengths: tablet 200 mg; no creams or injectables commercially available
- Manufacturers in the United Kingdom: Sanofi; Sun Pharmaceuticals; Teva Pharmaceuticals; Viatris (Mylan); Zydus Lifesciences; Dr. Reddy's Laboratories; Lupin; Apotex; Cadila
- Registration status in the United Kingdom: Prescription only
- OTC / Rx classification: Prescription-only (Rx)
Is hydroxychloroquine still worth talking about in the UK?
The short answer is yes, but mainly for the right patients and the right reasons.
Clinical evidence continues to support hydroxychloroquine sulfate in selected autoimmune disease pathways, especially lupus treatment and rheumatoid arthritis, where symptom control and steroid-sparing benefits can matter day to day.
MHRA safety messaging remains clear that this is a prescription-only medicine and not a routine option for viral illness.
Long-term use is appropriate only when there is a proper diagnosis, dose review, and monitoring plan.
The major severe risks remain retinopathy and cardiomyopathy.
In practice, the balance is straightforward.
For a patient with stable lupus or rheumatoid arthritis, the benefit can be fewer flares, less joint pain, and reduced reliance on steroids.
For someone without a valid indication, the risks outweigh the upside.
| Area | Potential benefit | Main risk |
|---|---|---|
| Lupus treatment | May reduce flares and improve symptoms | Retinal toxicity with long-term use |
| Rheumatoid arthritis | Can ease pain and help steroid-sparing treatment | Cardiac and visual adverse effects |
| Malaria prevention | Useful in specific travel protocols | Drug interactions and dose-related toxicity |
How hydroxychloroquine is used in NHS care
- Lupus
- Used to help reduce lupus flares and support longer-term control.
- Rheumatoid arthritis
- Prescribed as part of an NHS prescription when symptoms or disease pattern make it suitable.
- Malaria prophylaxis
- Sometimes used for travel-related prevention in specific circumstances and under protocol.
In NHS care, hydroxychloroquine tablets are usually started by rheumatology, dermatology, or a GP working from a specialist plan.
Travel clinic pathways are different because malaria prevention is tied to destination, resistance patterns, and timing before travel.
It is not a first-line choice for most infections, and that matters because discussions about it are often confused by social media claims.
The benefits are often practical rather than dramatic: fewer flares, reduced joint pain, or a better chance of cutting down steroids over time.
The catch is that benefit is not instant.
Some people wait weeks before noticing change, so repeat prescription planning through the NHS Electronic Prescription Service can help keep treatment steady.
| Who typically prescribes it | Usual reason |
|---|---|
| GP | Repeat maintenance under established specialist advice |
| Rheumatologist | Lupus or rheumatoid arthritis control |
| Dermatologist | Selected autoimmune skin disease pathways |
| Travel clinic clinician | Malaria prevention advice and dosing |
Approved indications and off-label prescribing in the United Kingdom
What is officially routine, and what needs extra care?
Hydroxychloroquine is a prescription-only medicine in the UK, and UK prescribers generally keep to recognised autoimmune and antimalarial uses.
Malaria treatment and prophylaxis follow protocol-based dosing.
Long-term autoimmune treatment is routine in the right clinical setting, but off-label hydroxychloroquine use needs clearer counselling and documentation in both NHS and private clinics.
That is because the medicine has a narrow safety margin for some patients and the monitoring burden is real.
Historical or social-media claims have not survived higher-quality research, especially where people promoted it as a general solution for viral illness.
| Use | Status | Monitoring need |
|---|---|---|
| Lupus | Routine clinical use | Eye checks and dose review |
| Rheumatoid arthritis | Routine clinical use | Long-term safety monitoring |
| Malaria prophylaxis | Protocol-based use | Travel and interaction review |
| Unusual off-label uses | Specialist-only | Stronger documentation and counselling |
People often ask why the rules are so strict.
The answer is simple: the medicine can help, but only when the indication is sound, the dose fits the patient, and monitoring is properly arranged.
Composition, strengths and brand landscape
- INN
- Hydroxychloroquine.
- ATC code
- P01BA02.
- Dose form
- Tablet.
In the UK, hydroxychloroquine 200 mg tablets are the usual format.
The active substance is hydroxychloroquine sulfate; brands include Plaquenil (Sanofi) and Quinoric.
Generic substitution is common when clinically appropriate.
| Brand | Manufacturer | Packaging |
|---|---|---|
| Plaquenil | Sanofi | Film-coated 200 mg tablets |
| Quinoric | Bristol Laboratories | Tablets |
Generic hydroxychloroquine is also made by manufacturers such as Teva, Viatris, Zydus Lifesciences, Dr. Reddy's Laboratories and Lupin.
Contraindications and who needs extra caution
Who should be careful before starting hydroxychloroquine?
Absolute contraindications include known hypersensitivity to hydroxychloroquine or other 4-aminoquinoline compounds, pre-existing retinopathy, and severe liver or renal impairment where the product information treats this as a hard stop.
Children under 6 years should not receive the tablet form because of choking risk.
People with psoriasis, porphyria, cardiac conduction disorders, G6PD deficiency, or other QT prolongation risks need close assessment rather than casual prescribing.
Older patients, especially those over 65, are more likely to experience adverse effects and may need lower starting doses or tighter review.
Tell the pharmacist about eye disease, heart problems, kidney or liver disease, and every medicine being taken before dispensing.
- Eye disease: raises concern for retinal toxicity and irreversible vision loss.
- Cardiac history: matters because conduction problems can worsen QT prolongation risk.
- Kidney or liver impairment: may require dose reduction and closer monitoring.
- Pregnancy and breastfeeding: need individual advice rather than assumptions.
| Risk factor | Why it matters |
|---|---|
| Retinopathy | Vision loss can be irreversible |
| Renal impairment | Drug accumulation and toxicity risk rises |
| Hepatic impairment | Side effects may become more likely |
| QT prolongation | Rhythm problems can become more serious |
Driving is usually only an issue if blurred vision or dizziness occurs.
Alcohol advice should be cautious, because nausea and liver concerns can make side effects harder to manage.
Dosage guidance, missed doses and overdose
How much hydroxychloroquine is taken depends on the condition being treated.
For rheumatoid arthritis and lupus, typical adult dosing is 200–400 mg daily, taken once or divided.
For malaria prophylaxis, the dose is 400 mg weekly, usually started 1 to 2 weeks before travel.
For malaria treatment, the schedule is 800 mg initially, then 400 mg at 6, 24, and 48 hours.
Children need weight-based dosing, and dose adjustments may be needed in renal or hepatic impairment, in the elderly, and during severe illness.
| Condition | Typical regimen | Duration | Monitoring |
|---|---|---|---|
| Malaria treatment | 800 mg, then 400 mg at 6, 24, 48 hours | Days | Clinical response and adverse effects |
| Malaria prophylaxis | 400 mg weekly | Travel-based | Travel review and interaction check |
| RA / SLE | 200–400 mg daily | Long-term | Eye checks and tolerance |
If a dose is missed, take it as soon as remembered unless the next dose is nearly due.
Do not double up.
Overdose is a medical emergency and can cause headache, drowsiness, visual disturbances, cardiac arrhythmias, convulsions, and hypokalaemia.
Anyone with suspected overdose needs urgent hospital care and poison control management.
Interactions with other medicines, food and drink
Which combinations cause trouble in real life?
The biggest issue is concurrent QT-prolonging drugs.
That includes some antibiotics, antiarrhythmics, and antipsychotics, plus other medicines that can affect heart rhythm.
Medicines that lower blood sugar can also be a concern because severe hypoglycaemia, although rare, is a serious effect.
Taking hydroxychloroquine with food often helps reduce stomach upset, which matters for people trying to fit repeat dosing around work and family routines.
| Interaction type | Examples | What to do |
|---|---|---|
| QT prolongation | Some antibiotics, antiarrhythmics, antipsychotics | Ask for a pharmacist or prescriber review |
| Blood sugar lowering | Diabetes medicines | Watch for signs of hypoglycaemia |
| Food | Meals can improve tolerability | Often best taken with food |
Tea and coffee do not create a major direct interaction, but caffeine may worsen jitteriness or sleep disturbance in some people.
Alcohol is not a formal major interaction, yet it can aggravate nausea and liver concerns.
If a suspected side effect appears, the MHRA Yellow Card system is there for reporting.
When in doubt, ask your pharmacist before combining hydroxychloroquine with any new treatment.
Side effects, monitoring and eye safety
Can hydroxychloroquine be tolerated well?
Often yes, but side effects still need respect.
The most common complaints are nausea, vomiting, diarrhoea, abdominal pain, anorexia, skin rash, and itch.
Less common effects include headache, dizziness, insomnia, mood swings, pigment changes in skin or hair, and visual disturbances such as blurring or scotomas.
The serious risks are rarer, but they matter because retinopathy can become irreversible, and cardiomyopathy or seizures can be dangerous.
Long-term users need routine ophthalmological monitoring, and early eye checks are especially important in the NHS pathway for chronic therapy.
| Side effect | How common | Action |
|---|---|---|
| Nausea or abdominal upset | Common | Take with food and speak to a pharmacist if persistent |
| Rash or itch | Common | Seek advice if troublesome or widespread |
| Blurred vision or field loss | Serious warning sign | Stop and seek urgent medical review |
| Retinopathy | Rare but serious | Needs specialist ophthalmology monitoring |
New blurred vision should never be ignored.
Visual field changes need prompt assessment because catching toxicity early gives the best chance of preventing further damage.
Comparable medicines and treatment preferences
Why choose hydroxychloroquine over something stronger?
Because in milder autoimmune disease it is often better tolerated than alternatives, even if it is not always enough on its own.
For some patients, clinicians move to methotrexate, azathioprine, mycophenolate mofetil, or biologic DMARDs if disease control needs a bigger step.
For malaria, artemisinin-based combination therapies are important comparators, and chloroquine remains the closest older antimalarial cousin.
| Medicine | Main use | Relative point |
|---|---|---|
| Hydroxychloroquine | Lupus, rheumatoid arthritis, malaria prevention | Often well tolerated, but not always enough alone |
| Chloroquine | Antimalarial | Similar class, different use pattern |
| Methotrexate | RA / SLE | Stronger disease control, more intensive monitoring |
| Azathioprine / Mycophenolate mofetil | Autoimmune disease | Used when extra immunosuppression is needed |
The choice comes down to balance: symptom control, tolerability, monitoring, and the exact diagnosis.
Frequently asked questions and proper use advice from UK pharmacists
How long does hydroxychloroquine take to work?
It is usually not instant, and many people need several weeks before noticing the full effect.
Can it be taken with food?
Yes, and taking it with food often helps reduce stomach upset.
What should I do if my vision changes?
Seek medical help promptly, because blurred vision or visual field changes can signal retinal toxicity.
Is it safe to stop suddenly?
Do not stop without medical advice, especially if it is being used for lupus or rheumatoid arthritis.
For day-to-day use, the pharmacist checklist is simple.
- Take it at the same time each day.
- Attend eye checks if you are on long-term treatment.
- Keep tablets in the original packaging.
- Store at 15–30°C, away from moisture and direct light.
- Seek urgent help for overdose symptoms or new vision problems.
NHS advice pathways are useful when symptoms change, but sudden eye symptoms or suspected overdose should never wait.
Delivery across the United Kingdom
| City | Region | Delivery time |
|---|---|---|
| London | England | 9–21 days |
| Birmingham | England | 9–21 days |
| Manchester | England | 9–21 days |
| Leeds | England | 9–21 days |
| Liverpool | England | 9–21 days |
| Sheffield | England | 9–21 days |
| Bristol | England | 9–21 days |
| Newcastle upon Tyne | England | 9–21 days |
| Glasgow | Scotland | 9–21 days |
| Edinburgh | Scotland | 9–21 days |
| Cardiff | Wales | 9–21 days |
| Belfast | Northern Ireland | 9–21 days |
| Inverness | Scotland | 9–21 days |
| Swansea | Wales | 9–21 days |
For most orders, using a registered online pharmacy and checking the product details before purchase is the safest approach.



