
Medroxyprogesterone
In brief
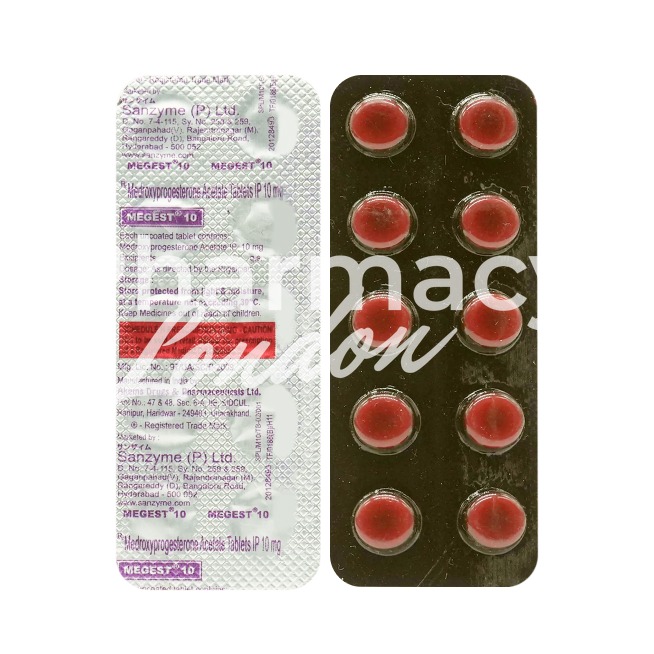
- In our pharmacy, you can buy medroxyprogesterone without a prescription, with delivery throughout the United Kingdom. It is usually supplied discreetly in blister packs, vials, or pre-filled syringes.
- Medroxyprogesterone is used for contraception, endometriosis, abnormal uterine bleeding, secondary amenorrhoea, and some hormone-sensitive cancers. It is a progestogen that works by suppressing ovulation, thinning the endometrium, and altering cervical mucus to help prevent pregnancy and control hormone-related conditions.
- The usual dose depends on the condition: for contraception, 150 mg by intramuscular injection every 3 months or 104 mg by subcutaneous injection every 3 months; for some gynaecological uses, 5–10 mg by mouth daily for 5–10 days; for certain cancers, doses are individually adjusted by specialists.
- The form of administration is a tablet, intramuscular injection, or subcutaneous injection, depending on the product and indication.
- It usually starts working within hours after an injection, although full contraceptive protection may require up to 7 days if the injection is not given at the start of the menstrual period. Oral treatment may begin to act within a few days as hormone levels build and bleeding patterns change.
- The duration of action is about 12–13 weeks for injectable contraception, while oral courses are usually taken for 5–10 days per cycle. For cancer treatment, the effect may continue as long as therapy is maintained.
- Avoid alcohol or use it only with caution, as it may worsen dizziness, headache, or mood changes, and can also make side effects feel stronger.
- The most common side effects are menstrual changes or amenorrhoea, weight gain, headache, abdominal bloating or pain, dizziness, mood changes, acne, hair loss, and decreased libido.
- Would you like to try medroxyprogesterone without a prescription?
Legal status and availability in the UK
Medroxyprogesterone is a prescription-only medicine (POM) in the UK.
In our online pharmacy, medroxyprogesterone is available without a prescription, with discreet delivery to the United Kingdom in 9–21 days.
Clinical effectiveness in NHS practice
Does medroxyprogesterone actually work well in everyday NHS care?
For many patients, the answer is yes, especially when the main goal is reliable contraception with less day-to-day effort.
In routine UK practice, the depot injection is valued because it reduces menstrual bleeding for many users and can lead to amenorrhoea, which some patients actively want.
The quarterly schedule is often the biggest reason for choosing it, particularly for people who prefer not to remember a daily tablet.
Drop-out usually happens for practical reasons rather than lack of effect.
- Irregular bleeding or spotting.
- Weight gain concerns.
- Mood changes.
- Desire to return to fertility sooner.
The standard regimen is 150 mg IM every 3 months or 104 mg SC every 3 months.
In NHS pathways, follow-up matters if bleeding persists, because ongoing bleeding is a common reason for review rather than a sign that the medicine has stopped working.
Pharmacist counselling helps set expectations, while GP surgery or sexual health clinic monitoring checks that the method still suits the patient.
Convenience, lighter periods, and reduced anxiety about missed pills are often mentioned as positives.
Indications and expanded uses in the United Kingdom
What is medroxyprogesterone actually used for, and when does specialist care come in?
The licensed uses are straightforward, but specialist-led and off-label practice can appear in gynaecology and oncology.
- Contraception
- Used as an injectable progestogen for long-acting pregnancy prevention.
- Endometriosis
- Used as progestin therapy when symptom suppression is needed.
- Secondary amenorrhoea
- Used in short oral courses to induce a withdrawal bleed where appropriate.
- Dysfunctional uterine bleeding
- Used for cycle regulation and bleeding control in selected patients.
- Certain cancers
- Used in endocrine therapy where a progestogen is part of specialist treatment.
Real dosing examples from accepted practice include oral courses of 5–10 mg daily for 5–10 days, while oncology dosing is individualised by specialists.
In the NHS, anything outside the core licensed indications should be specialist-led, whether that is in hospital gynaecology, sexual health, or private prescribing.
Composition, brands and United Kingdom product landscape
What exactly is in the pack when a patient collects medroxyprogesterone?
The medicine is a synthetic progestogen available in both injectable and tablet forms, and the brand name often tells you the route.
Depo-Provera is the best-known injection, while Provera is the tablet brand most people recognise.
Single-use vials, pre-filled syringes, and blister packs are all used.
| Form | Strength | Common pack type |
|---|---|---|
| Oral tablet | 2.5 mg, 5 mg, 10 mg | Blister strips or bottles |
| IM suspension | 150 mg/mL | Pre-filled syringe or vial |
| Subcutaneous injection | 104 mg/0.65 mL | Pre-filled syringe |
Pfizer is the brand owner for Depo-Provera, Sayana Press (subcutaneous 104 mg) and Provera.
Contraindications and special precautions
Who should not use medroxyprogesterone, or needs closer review first?
Because this is prescription-only in the UK, a clinician should always check for contraindications before supply.
- Known or suspected pregnancy.
- Active thromboembolic disease.
- Unexplained vaginal bleeding.
- Known or suspected breast or genital cancer.
- Severe liver dysfunction or disease.
- Hypersensitivity to medroxyprogesterone or excipients.
Conditions that usually need monitoring include depression, diabetes, hypertension, osteoporosis or high bone-loss risk, migraine, and hyperlipidaemia.
Long-term DMPA use is the main setting where bone health becomes a practical issue, especially if there are other risk factors.
In daily life, patients should be careful if dizziness affects driving, keep alcohol modest if it worsens side effects, and seek advice quickly if mood becomes lower or more unstable.
Medication counselling in the UK normally covers these points clearly, because safety is about fit, not just product choice.
Dosage guidelines and treatment schedules
How is the dose chosen for different uses?
The route matters just as much as the dose, because the injection and the tablets are used for different aims.
| Indication | Dose and route | Typical schedule |
|---|---|---|
| Contraception | 150 mg IM | Every 12–13 weeks |
| Contraception | 104 mg SC | Every 12–13 weeks |
| Endometriosis or uterine bleeding | 5–10 mg oral daily | For 5–10 days, usually cyclically |
| Certain cancers | Specialist dosing | Individualised therapy |
| Secondary amenorrhoea | 5–10 mg oral daily | For 5–10 days, repeated as needed |
For contraception, the practical interval is usually 12 to 13 weeks, and timely attendance matters.
Gynaecological courses are generally short, cyclical, and tailored to the reason for treatment.
Cancer regimens are not standardised in the same way and must be individualised by the oncology team.
Children should only receive it under specialist care.
There is limited dose-specific data in older patients, and hepatic impairment needs caution because the drug is metabolised in the liver.
Interactions and practical use with food, drink, and other medicines
Do food and drink matter with medroxyprogesterone?
There are no routine food restrictions, but alcohol can make dizziness or mood symptoms feel worse for some patients.
Tea and coffee are not major interaction issues, although caffeine may aggravate anxiety in sensitive people.
- Enzyme-inducing medicines.
- Some antiepileptics.
- Rifampicin.
- Medicines that affect mood or clot risk.
These medicines should be checked with a pharmacist or prescriber before starting treatment.
If a side effect seems unusual or severe, reporting it through the MHRA Yellow Card scheme helps improve medicine safety for everyone.
Comparable medicines and why patients switch
What if medroxyprogesterone does not feel like the right fit?
The main alternatives in UK practice include norethisterone, levonorgestrel, desogestrel, dienogest, and combined hormonal methods.
- Medroxyprogesterone: convenient quarterly injection, tablets also available, but bleeding changes and weight gain can lead to switching.
- Norethisterone: oral option, often used for cycle control or period delay, but not as convenient as a depot injection.
- Levonorgestrel: available orally and as an intrauterine system, with different bleeding patterns and reversal timing.
- Desogestrel: oral-only in routine use, useful for some patients who prefer daily self-management.
- Dienogest: often considered for endometriosis, especially when symptom control is the priority.
Patients switch because of mood, weight, delayed fertility return, or simply because they want a different bleeding profile.
Others stay with Depo-Provera because quarterly dosing is easier than remembering tablets.
Frequently asked questions for NHS patients
How long does the injection last?
The standard contraceptive effect lasts about 12 to 13 weeks.
What happens if I miss my injection?
If more than 14 weeks have passed, backup contraception and a pregnancy assessment are needed.
Will it stop my periods?
Periods often become lighter or stop altogether, but irregular bleeding can happen first.
How long does fertility take to return after stopping?
Return of fertility can be delayed after the last injection, so planning ahead matters if pregnancy is wanted soon.
Proper use, counselling and follow-up in the United Kingdom
What should a pharmacist or clinician check before the first dose?
The usual UK process is simple but careful: confirm why the medicine is being used, screen for pregnancy, check contraindications, explain bleeding changes, and arrange follow-up if needed.
After that, documenting the injection date is essential, because the next appointment depends on it.
NHS patient portals and repeat-prescription systems help many patients stay on schedule.
Storage also matters for safe use.
- Store at 15–25°C.
- Protect from light and freezing.
- Do not use if the suspension is clumped or discoloured.
- If an injection is late, use backup contraception and assess for pregnancy if more than 14 weeks have passed.
- If tablets are missed, take them as soon as remembered unless the next dose is due soon, and do not double up.
Patients should seek urgent help for heavy bleeding, severe mood change, signs of allergy, or any concern about pregnancy after a missed dose.
Good counselling makes medroxyprogesterone easier to use safely, especially when patients are juggling work or travel.
Delivery across the United Kingdom
| City | Region | Delivery time |
|---|---|---|
| London | England | 9–21 days |
| Birmingham | England | 9–21 days |
| Manchester | England | 9–21 days |
| Glasgow | Scotland | 9–21 days |
| Edinburgh | Scotland | 9–21 days |
| Liverpool | England | 9–21 days |
| Leeds | England | 9–21 days |
| Bristol | England | 9–21 days |
| Sheffield | England | 9–21 days |
| Newcastle upon Tyne | England | 9–21 days |
| Cardiff | Wales | 9–21 days |
| Belfast | Northern Ireland | 9–21 days |
| Aberdeen | Scotland | 9–21 days |
| Portsmouth | England | 9–21 days |
| Norwich | England | 9–21 days |



