
Misoprostol
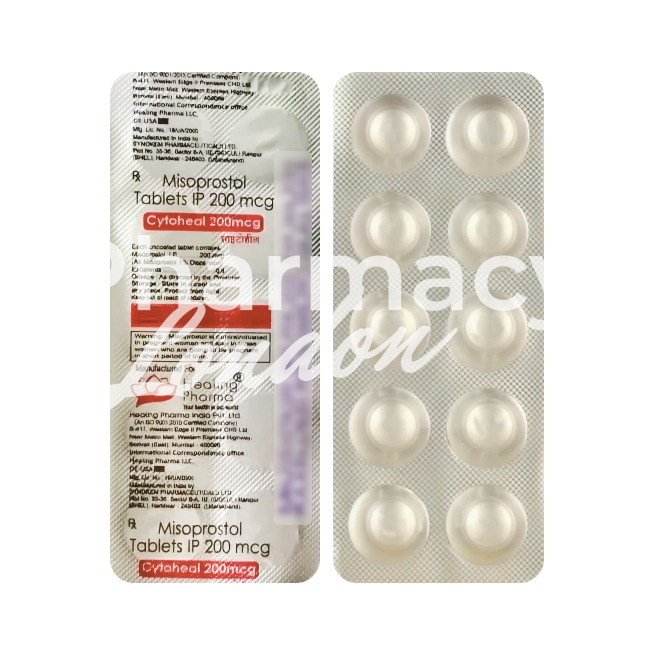
In brief
- Misoprostol is a prescription-only medicine (POM) in the UK and is dispensed with a prescription; consult a clinician before use.
- Misoprostol is a synthetic prostaglandin E1 analogue used to protect the gastric mucosa from NSAID injury, and as a uterotonic for medical abortion, miscarriage management, labour induction and prevention/treatment of postpartum haemorrhage; it works by reducing gastric acid secretion and increasing mucosal defence, and by stimulating uterine contractions and cervical ripening.
- Usual dosages vary by indication: gastric ulcer prevention 200 mcg 2–4 times daily; medical abortion 800 mcg (4×200 mcg) buccal/vaginal/sublingual after mifepristone 200 mg; miscarriage management 800 mcg vaginally (may repeat after 3–12 h); labour induction commonly 25 mcg vaginally every 4–6 h (off‑label); PPH 600–800 mcg orally as a single dose.
- Administration is by tablet, with routes including oral, buccal, sublingual and vaginal (and sometimes rectal), depending on the indication and protocol.
- Onset of effect depends on the route: generally 15–60 minutes (sublingual/buccal and vaginal routes are faster for uterine effects; oral onset for gastric protection or PPH is commonly within 20–60 minutes).
- Duration of action is variable; plasma half‑life is short but uterine effects commonly persist for several hours (typically around 3–6 hours), while gastroprotective benefit requires regular dosing as prescribed.
- Avoid alcohol while taking misoprostol — alcohol can exacerbate gastrointestinal side effects (nausea, vomiting, diarrhoea) and increase bleeding risk in obstetric contexts.
- The most common side effect is diarrhoea; other frequent effects include abdominal pain/cramps, nausea, flatulence, headache and uterine cramps or increased vaginal bleeding when used for pregnancy‑related indications.
- Would you like to try misoprostol without a prescription?
Basic misoprostol information
- INN (international nonproprietary name): Misoprostol
- Brand names available in the United Kingdom: Cytotec and generic misoprostol tablets
- ATC code: A02BB01 (gastric protection); G02AD06 (gynaecological use)
- Forms and dosages: tablets 200 mcg (standard) and 100 mcg (less common); combination tablets with diclofenac also exist
- Manufacturers: Pfizer (Cytotec) and various generic manufacturers
- Registration status in the United Kingdom: prescription only
- OTC / Rx classification: prescription‑only (Rx); misoprostol is not available over the counter
Legal status and availability in the UK
In our online pharmacy, misoprostol is available without a prescription, with discreet delivery to the United Kingdom in 9–21 days.
Clinical effectiveness in the UK
What are the real‑world outcomes with misoprostol?
When misoprostol is used within guideline protocols it contributes to high clinical effectiveness for both PPH management and medical abortion pathways.
PPH protocols that include misoprostol have been associated with lower transfusion rates where injectable oxytocics are delayed or inaccessible.
Medical abortion using mifepristone followed by 800 mcg misoprostol achieves high complete abortion rates with structured follow‑up.
Predictable side effects include diarrhoea and cramps, and home‑based management works well when clear counselling and 24/7 helplines are available.
Serious adverse events are more likely in high‑risk obstetric cases or when induction is attempted off‑label without specialist oversight.
- Standard regimens in use: abortion 800 mcg after mifepristone; PPH 600–800 mcg single dose.
Indications and expanded uses
Which uses are MHRA‑approved and which are off‑label in UK practice?
Misoprostol’s original licensed indication is gastric ulcer prophylaxis when NSAIDs are required.
In UK clinical practice misoprostol is used for gastric protection, for medical abortion (very commonly in combination with mifepristone under clinical governance), miscarriage management, PPH management and, under local trust protocols, for labour induction.
Off‑label uses often include labour induction using low vaginal doses (commonly 25 mcg) and miscarriage management pathways, both of which usually require obstetric review because induction can increase the risk of uterine rupture in people with prior uterine surgery.
All uses are prescription‑only and should follow local governance and informed consent procedures.
- MHRA‑approved: gastric ulcer prevention (NSAID users).
- Off‑label (require specialist oversight): labour induction (25 mcg vaginally), some miscarriage protocols; always consult obstetric guidelines for high‑risk patients.
Composition and brand landscape
What is in the tablet and which brands are available?
The active ingredient is misoprostol (INN), usually presented as 200 mcg tablets and less commonly as 100 mcg tablets.
The best‑known brand is Cytotec (Pfizer), and generic misoprostol tablets are also available.
Many NHS trusts and sexual health clinics use generic 200 mcg tablets.
Always check MHRA listings and local trust formularies for current authorised brands and stock status.
Contraindications and special precautions
Who should not take misoprostol and which patients need extra caution?
Absolute contraindications include known hypersensitivity to prostaglandins or misoprostol and pregnancy when the drug is prescribed for gastric protection.
When misoprostol is used intentionally for abortion, miscarriage or PPH the pregnancy‑related contraindication is contextually different, but suspected ectopic pregnancy remains an absolute contraindication for medical abortion protocols.
Relative contraindications requiring multidisciplinary assessment include inflammatory bowel disease, severe cardiovascular disease, poorly controlled asthma, prior uterine surgery (especially multiple caesarean sections) and severe hepatic or renal impairment.
Lifestyle cautions include the potential for diarrhoea and dizziness that can affect driving and work performance, and alcohol should be avoided if dehydration from bleeding or gastrointestinal upset is likely.
- Absolute contraindications: hypersensitivity to prostaglandins; pregnancy when used for gastric protection; suspected ectopic pregnancy for abortion/miscarriage protocols.
- Relative contraindications: IBD, severe CVD, prior uterine surgery, asthma, severe hepatic/renal impairment.
| Activity | Advice |
|---|---|
| Driving | Avoid if dizzy, faint or severely unwell from cramps/diarrhoea |
| Heavy lifting / work | Avoid while experiencing heavy bleeding or significant cramping |
Dosage guidelines
What are standard NHS regimens and special population considerations?
For gastric ulcer prophylaxis the typical dose is 200 mcg two to four times daily with food and at bedtime while the patient remains on NSAIDs.
For medical abortion the commonly used regimen is mifepristone 200 mg followed 24–48 hours later by 800 mcg misoprostol (four 200 mcg tablets) administered buccally, vaginally or sublingually.
Miscarriage management often uses 800 mcg vaginally with the option to repeat after 3–12 hours if needed.
Post‑partum haemorrhage single oral doses of 600–800 mcg are used when injectable uterotonics are unavailable or delayed.
Labour induction protocols in many trusts use low vaginal doses of 25 mcg every 4–6 hours but this is off‑label and guided by local obstetric protocols.
| Indication | Route | Dose / timing |
|---|---|---|
| Gastric ulcer prevention | Oral | 200 mcg 2–4x/day with food |
| Medical abortion (with mifepristone) | Buccal/Vaginal/Sublingual | Mifepristone 200 mg then 800 mcg misoprostol after 24–48 h |
| PPH | Oral | 600–800 mcg single dose |
| Labour induction (off‑label) | Vaginal | 25 mcg every 4–6 h (local protocol) |
Special populations such as the elderly or those with severe renal/hepatic impairment require caution but no standard dose adjustments for mild/moderate renal impairment are listed.
Prescription‑only status and local protocol adherence are essential; route and timing should be verified with the treating clinician or obstetric unit.
Interactions overview
Are there important drug, food or clinical interactions to watch for?
Major food interactions are not recorded, although alcohol can worsen dehydration if diarrhoea or heavy bleeding occurs after treatment.
Vomiting after misoprostol can impair absorption of concomitant oral medicines, and clinicians should consider this in acute settings.
Caution is advised when combining misoprostol with other uterotonics such as oxytocin or carboprost because additive uterine activity can intensify contractions and related effects.
- High‑risk combinations: misoprostol plus other uterotonics (additive effect); vomiting may impede absorption of oral drugs.
Monitor patients for increased gastrointestinal upset when misoprostol is used alongside other GI‑irritant medicines and report interaction type events via Yellow Card where appropriate.
Comparable medicines and prescribing preferences
What are the common alternatives and how do clinicians choose between them?
For induction and PPH, oxytocin is frequently first‑line in many NHS settings and dinoprostone is an alternative prostaglandin used for induction.
Injectable carboprost is another uterotonic option for PPH where appropriate and available.
For gastric protection proton pump inhibitors are commonly preferred over prostaglandins for many patients.
For medical abortion mifepristone is an integral partner drug, and misoprostol alone is less effective but used when mifepristone is unavailable.
| Drug | Typical use | Pros | Cons |
|---|---|---|---|
| Misoprostol | PPH, medical abortion, induction (off‑label) | Oral/vaginal routes, WHO essential med | GI side effects; off‑label induction risks |
| Oxytocin | First‑line uterotonic for PPH and labour | Well‑established IV/IM use | Requires parenteral administration |
| Dinoprostone | Labour induction, cervical ripening | Licensed induction agent | Local availability |
Clinician checklist when choosing misoprostol:
- Confirm indication and gestational parameters (where relevant).
- Screen for prior uterine surgery and ectopic pregnancy risk.
- Ensure reliable follow‑up and access to emergency care.
- Discuss patient preference and likely side effects.
FAQ
-
Is misoprostol legal and available on the NHS?
Yes; misoprostol is prescription‑only and used in hospitals and clinics under MHRA‑aligned protocols and local trust governance.
-
What should I expect after taking misoprostol for abortion?
Expect heavy cramping and bleeding as the common response, with most patients having a complete abortion with follow‑up; seek urgent care for fever over 38°C, bleeding soaking more than two pads per hour, fainting or other worrying signs.
-
Can I drive after taking misoprostol?
Avoid driving if you feel dizzy, faint, or are severely unwell from cramps or diarrhoea.
-
Where can I report side effects?
Report suspected adverse reactions via the MHRA Yellow Card scheme or through your NHS clinic follow‑up pathway.
Guidelines for proper use
What should pharmacies and clinicians cover when counselling patients who will take misoprostol?
Pharmacist counselling should explain the indication, route and exact timing of doses, expected side effects such as diarrhoea and cramping, and red‑flag symptoms that require urgent assessment.
Advise storage below 25°C in a dry place and to keep tablets in the original pack to protect from moisture.
Pharmacists should signpost patients to the NHS App, local sexual health services or 24/7 maternity helplines for follow‑up and to NHS 111 out‑of‑hours concerns.
Use Electronic Prescription Service (EPS) to facilitate clinic‑to‑pharmacy transfers and ensure ID verification and provision of a patient leaflet at dispensing.
- Confirm indication and check contraindications (hypersensitivity, ectopic pregnancy where relevant).
- Explain the dosing schedule and what each symptom may indicate.
- Provide written information and emergency contact numbers (NHS 111, local maternity unit).
- Document informed consent for off‑label uses and adhere to trust protocols for induction or high‑risk cases.
Red‑flag symptoms (seek urgent care):
- Fever >38°C after treatment.
- Very heavy bleeding (soaking >2 pads per hour for more than 2 hours).
- Severe continuous abdominal pain not relieved by analgesia.
- Fainting, dizziness, or signs of severe allergic reaction.
Delivery across the United Kingdom
| City | Region | Delivery time |
|---|---|---|
| London | England | 9–21 days |
| Birmingham | England | 9–21 days |
| Manchester | England | 9–21 days |
| Glasgow | Scotland | 9–21 days |
| Liverpool | England | 9–21 days |
| Leeds | England | 9–21 days |
| Sheffield | England | 9–21 days |
| Bristol | England | 9–21 days |
| Newcastle | England | 9–21 days |
| Nottingham | England | 9–21 days |
| Leicester | England | 9–21 days |
| Cardiff | Wales | 9–21 days |
| Belfast | Northern Ireland | 9–21 days |
| Swansea | Wales | 9–21 days |



