
Neurontin
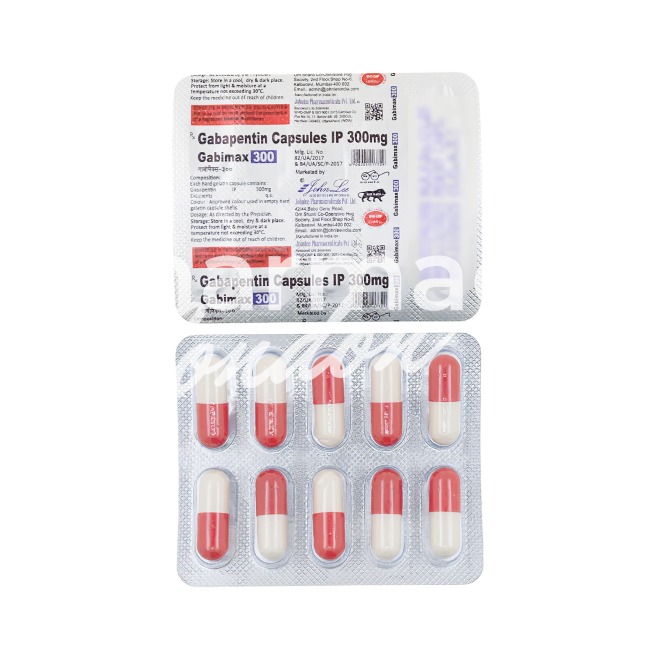
In brief
- Neurontin (gabapentin) is a prescription-only medicine (POM) in the UK.
- Neurontin is used for partial seizures and various types of neuropathic pain (including postherpetic neuralgia and diabetic neuropathy); it acts by binding the α2δ subunit of voltage‑gated calcium channels in the central nervous system, reducing excitatory neurotransmitter release.
- Typical adult dosages: epilepsy often starts at 300 mg on day 1 then 300 mg twice daily then 300 mg three times daily, with maintenance commonly 900–1,800 mg/day (up to 3,600 mg/day in some neuropathic pain regimens after titration); for neuropathic pain usual target ranges 1,800–3,600 mg/day in divided doses; children (≥6 years) start at 10–15 mg/kg/day (divided), usually 25–35 mg/kg/day for maintenance; reduce doses substantially in renal impairment.
- Given orally as capsules, tablets or oral solution, usually in divided doses (three times daily).
- Onset: sedation and dizziness can occur within 1–3 hours of a dose; anticonvulsant effects may begin within hours to days as doses are escalated, while meaningful relief of neuropathic pain often takes several days to a few weeks of titration.
- Duration of action: gabapentin has a half‑life around 5–8 hours and is typically dosed three times daily.
- Alcohol warning: avoid or limit alcohol while taking Neurontin—alcohol increases drowsiness, dizziness and the risk of respiratory depression and can worsen cognitive and motor impairment, especially in the elderly or when combined with opioids or other CNS depressants.
- The most common side effect is dizziness (drowsiness/somnolence are also very common), with other frequent effects including fatigue, peripheral oedema, ataxia, weight gain and gastrointestinal symptoms.
- Would you like to try Neurontin without a prescription?
Basic Neurontin information
- INN (international nonproprietary name): Gabapentin
- Brand names available in the United Kingdom: Neurontin (originator); generics by Teva, Sandoz, Mylan/Viatris and others
- ATC code: N03AX12
- Forms and dosages: capsules 100 mg, 300 mg, 400 mg; tablets 600 mg, 800 mg; oral solution 250 mg/5 mL
- Manufacturers: Pfizer (originator) and numerous generic manufacturers
- Registration status in the United Kingdom: Authorised for partial seizures and neuropathic pain; prescription‑only
- OTC / Rx classification: Prescription‑only (Rx)
Legal status and availability in the UK
Our online pharmacy accepts valid prescriptions and offers discreet delivery within the United Kingdom in 9‑21 days.
Clinical effectiveness in the UK
In NHS practice gabapentin is primarily used for focal epilepsy and neuropathic pain such as postherpetic neuralgia and diabetic neuropathy.
Adherence is commonly influenced by side effects such as dizziness and somnolence and by the need for slow upward titration.
For seizure control gabapentin performs well as adjunctive therapy; typical maintenance dosing in adults is 900–1800 mg/day in divided doses.
In neuropathic pain, maintenance dosing commonly ranges 1800–3600 mg/day where tolerated.
| Outcome metric | Typical change | Adverse event rate |
|---|---|---|
| Pain score (neuropathic) | Modest to moderate reduction vs baseline | Dizziness/somnolence common |
| Seizure frequency (adjunctive) | Reduced seizure frequency in partial seizures | Withdrawal risk if stopped abruptly |
| Quality of life / function | Improvements weighted by functional gains | Older patients: increased fall risk |
Indications and expanded uses
The MHRA authorises gabapentin for partial seizures and for peripheral neuropathic pain such as postherpetic neuralgia.
Off‑label uses seen in NHS and private practice include anxiety disorders, fibromyalgia and some chronic non‑neuropathic pain presentations where the evidence is mixed.
Clinicians should document the rationale and discuss uncertain efficacy and safety when prescribing off‑label.
- Licensed vs off‑label
- Licensed: Partial seizures; neuropathic pain (e.g. PHN, diabetic neuropathy).
- Off‑label (document and counsel): Anxiety, fibromyalgia, chronic non‑neuropathic pain.
- Prescriber checklist
- Record indication and why standard options were unsuitable.
- Obtain informed consent and document counselling.
- Plan monitoring for benefit, side effects and misuse.
Composition and brand landscape
Patients will see different pack shapes and names; clear counselling helps avoid confusion.
Gabapentin is the International Nonproprietary Name (INN) and the originator brand is Neurontin (Pfizer).
Generic gabapentin is made by Teva, Sandoz, Mylan/Viatris and others.
| Brand | Form | Common dosages |
|---|---|---|
| Neurontin (Pfizer) | Capsules, Tablets, Solution | 100 mg, 300 mg, 400 mg caps; 600 mg, 800 mg tabs; 250 mg/5 mL solution |
| Generic manufacturers (Teva, Sandoz, Mylan/Viatris) | Capsules, Tablets, Solution | 100 mg, 300 mg, 400 mg; 600 mg, 800 mg; 250 mg/5 mL |
- Generic substitution checklist: Explain appearance differences, confirm dosing frequency and reassure on bioequivalence.
- Patient counselling tip: Show the current pack and review the patient information leaflet at collection.
Contraindications and special precautions
Common questions: who should not take gabapentin and what baseline checks are needed?
Absolute contraindication is known hypersensitivity to gabapentin or any excipient.
Key precautions include renal impairment, where gabapentin is renally excreted and requires dose reduction.
Patients with respiratory compromise, elderly frailty and those taking opioids or other CNS depressants face higher risk of sedation and respiratory depression.
History of mood disorder should prompt close monitoring because of possible suicidal ideation signals.
Pregnancy and breastfeeding require a careful risk–benefit discussion and use only if benefits outweigh risks.
- Contraindications: Known hypersensitivity to gabapentin or excipients.
- Precautions: Renal impairment (check creatinine), existing respiratory disease, elderly (fall risk), psychiatric history.
- Practical advice: Avoid heavy machinery and driving until tolerability is known; avoid excessive alcohol.
Renal dosing is essential to prevent accumulation; record baseline renal function and adjust as per prescribing information.
Dosage guidelines
Patients and carers frequently ask how quickly to titrate and what to expect when changing doses.
For adult epilepsy many NHS protocols start 300 mg on day one, then 300 mg twice daily on day two, then 300 mg three times daily thereafter with titration toward 900–1800 mg/day in divided doses.
For neuropathic pain initiation often starts at 300 mg daily with increases of about 300 mg every 24 hours to reach typical maintenance between 1800–3600 mg/day in divided doses, depending on tolerability.
Children aged six years and older use weight‑based regimens for epilepsy, starting at 10–15 mg/kg/day in three divided doses, with an effective dose usually of 25–35 mg/kg/day.
| Group | Starting dose | Maintenance |
|---|---|---|
| Adult (epilepsy) | 300 mg day 1; 300 mg twice day 2; then thrice daily | 900–1800 mg/day in divided doses |
| Adult (neuropathic pain) | 300 mg, increase by 300 mg/day as tolerated | 1800–3600 mg/day in divided doses |
| Children ≥6 years | 10–15 mg/kg/day in three doses | Usually 25–35 mg/kg/day |
Do not stop gabapentin abruptly, especially in epilepsy, as this may increase seizure risk; taper gradually under clinical supervision.
| Renal function (CrCl) | Adjustment |
|---|---|
| Normal | Standard dosing |
| Reduced | Proportionate dose reduction and extended dosing interval as per SmPC |
Interactions overview
A common worry is whether gabapentin combines safely with other medicines and alcohol.
Gabapentin has minimal hepatic CYP‑mediated interactions but important pharmacodynamic interactions exist.
Concomitant opioids, benzodiazepines, antipsychotics and alcohol increase sedation and respiratory depression risk, especially with polypharmacy.
Antacids containing aluminium or magnesium may reduce gabapentin absorption if taken at the same time.
| Co‑medication | Risk |
|---|---|
| Opioids | Increased sedation and respiratory depression |
| Benzodiazepines / Antipsychotics | Additive CNS depression |
| Antacids (Al/Mg) | Reduced bioavailability if co‑administered |
Clinicians should review all central nervous system depressants before prescribing and advise patients to report suspected interactions via the MHRA Yellow Card scheme.
Comparable medicines and prescribing preferences
Clinicians weigh efficacy and side‑effect profile when selecting between gabapentin and alternatives.
Pregabalin (Lyrica) is structurally related and is often chosen for tolerability or specific licence advantages, but it shares the misuse risk.
Antidepressants such as duloxetine or amitriptyline are first‑line for some neuropathic pains, while other antiepileptics like carbamazepine or lamotrigine are preferred for specific seizure types.
- Pros of gabapentin: Established indications, multiple formulations.
- Cons of gabapentin: Sedation, dose‑dependent adverse effects, requirement for renal dose adjustments, potential for misuse in some patients.
| Patient profile | Preferable option |
|---|---|
| Older patient with fall risk | Consider alternatives or lower doses; prioritise functional goals |
| Neuropathic pain needing rapid control | Pregabalin or duloxetine may be considered depending on comorbidities |
| Renal impairment | Gabapentin requires careful renal adjustment; consider alternatives if monitoring is difficult |
Frequently asked questions
Can I drive while taking gabapentin?
Do not drive until you know how gabapentin affects you; drowsiness and dizziness are common and if you are impaired you must not drive and you may need to inform the DVLA.
Is gabapentin addictive?
Gabapentin is not a classic opioid but dependence and misuse have been reported; monitor for dose escalation, craving and withdrawal, and avoid abrupt cessation.
Can I take gabapentin with opioids or alcohol?
Concomitant use increases the risk of severe sedation and respiratory depression and should be avoided or closely supervised by a clinician.
What if I miss a dose?
Take as soon as you remember unless it is nearly time for the next dose; do not double the dose.
If you suspect a serious reaction report it via the MHRA Yellow Card scheme and seek urgent advice for respiratory or severe allergic events.
Guidelines for proper use
Good counselling reduces harm and improves outcomes.
Pharmacists should explain the indication, expected timeline for benefit, titration steps and common side effects such as dizziness and somnolence.
Use teach‑back to confirm patient understanding and advise on alcohol avoidance and risks when combining with CNS depressants.
Prescribers should record baseline renal function, review repeat prescriptions regularly and document informed consent for any off‑label use.
- Pharmacist counselling checklist: Indication, dosing schedule, expected side effects, when to seek help, safe disposal.
- Monitoring schedule: Baseline renal review, review at 2–6 weeks for efficacy/tolerability, periodic review thereafter.
For disposal advise returning unused medicines to a pharmacy; do not flush tablets down the toilet.
Delivery across the United Kingdom
| City | Region | Delivery Time |
|---|---|---|
| London | Greater London | 9–21 days |
| Birmingham | West Midlands | 9–21 days |
| Manchester | Greater Manchester | 9–21 days |
| Glasgow | Scotland | 9–21 days |
| Liverpool | Merseyside | 9–21 days |
| Leeds | West Yorkshire | 9–21 days |
| Newcastle | Tyne and Wear | 9–21 days |
| Sheffield | South Yorkshire | 9–21 days |
| Bristol | South West England | 9–21 days |
| Edinburgh | Scotland | 9–21 days |
| Cardiff | Wales | 9–21 days |
| Belfast | Northern Ireland | 9–21 days |
| Norwich | East of England | 9–21 days |
| Plymouth | South West England | 9–21 days |



