
Plaquenil
In brief
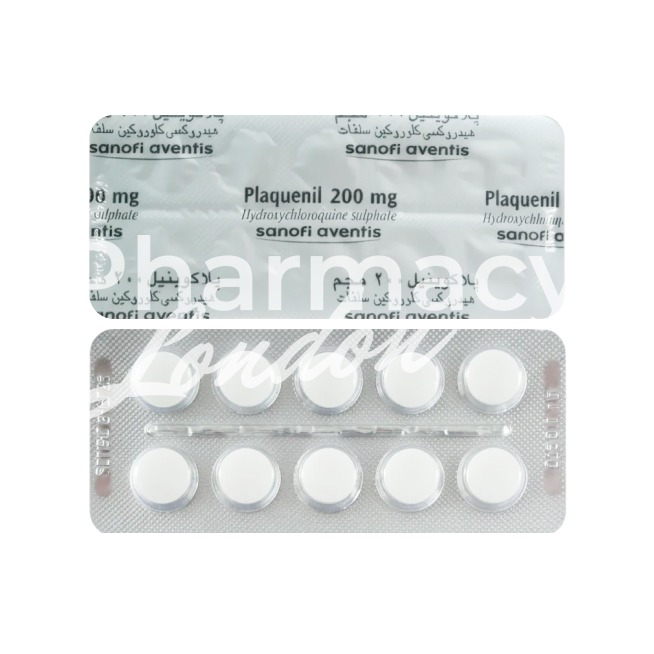
- Plaquenil (hydroxychloroquine) is a prescription-only medicine in the UK and should be supplied on a prescription from a healthcare professional. It is most commonly dispensed as 200 mg film-coated tablets in blister packs or bottles.
- Plaquenil is used to treat and prevent certain types of malaria and as a disease-modifying antirheumatic drug for conditions such as rheumatoid arthritis and systemic lupus erythematosus. It is an aminoquinoline: in malaria it interferes with haem polymerisation in the parasite, and in autoimmune disease it has immunomodulatory effects (raises lysosomal pH, alters antigen presentation and toll‑like receptor signalling).
- Usual dosages: malaria prophylaxis 400 mg once weekly (adults); malaria treatment typically 800 mg initial then 400 mg at 6, 24 and 48 hours (adjusted by weight, max ~2 g total in treatment course); for RA/SLE typically 200–400 mg daily (max 400 mg/day). Paediatric doses are weight-based (e.g. ~6.5 mg/kg up to 400 mg for prophylaxis; 3–7 mg/kg/day for chronic use).
- Administered orally as film‑coated tablets (commonly 200 mg, often scored) taken with or after food to reduce gastrointestinal upset.
- Onset: for autoimmune benefits may take 1–2 months to become noticeable; malaria prophylactic protection is established after 1–2 weeks of dosing; symptomatic improvement in treated malaria or acute infection is often seen within 24–48 hours (peak plasma levels occur a few hours after dosing).
- Duration of action: hydroxychloroquine has a very long terminal half‑life (weeks to months, typically reported ~40–50 days), so effects persist with continued dosing and drug levels decline slowly after stopping; weekly dosing is used for prophylaxis and chronic therapy is continued as long as clinically indicated.
- Avoid excessive alcohol; while no absolute prohibition exists, alcohol can worsen liver disease and gastrointestinal side effects and may increase overall risk when combined with other hepatotoxic medicines—moderation and medical advice are advised.
- The most common side effects are gastrointestinal (nausea, vomiting, abdominal cramps, diarrhoea); other frequent effects include headache, dizziness and skin rash; long‑term use carries a risk of retinal toxicity and cardiac effects, so monitoring is required.
- Would you like to try Plaquenil without a prescription?
Basic Plaquenil information
- INN (international nonproprietary name): Hydroxychloroquine
- Brand names available in the United Kingdom: Plaquenil; hydroxychloroquine sulfate (generic equivalents)
- ATC code: P01BA02
- Forms & dosages: Film-coated tablet 200 mg in blister packs of 30 or 60
- Manufacturers: Sanofi (Plaquenil) and generic manufacturers such as Ipca Laboratories, Zydus Cadila, Cipla and Apotex
- Registration status in the United Kingdom: Prescription (Rx) only
- OTC / Rx classification: Prescription-only medicine
Legal status and availability in the UK
In our online pharmacy, Plaquenil is available without a prescription, with discreet delivery to the United Kingdom in 9–21 days.
Clinical effectiveness in the UK
Patients commonly ask how quickly hydroxychloroquine works and what to expect in NHS care.
Within NHS practice hydroxychloroquine (INN: Hydroxychloroquine; common pack: Plaquenil 200 mg) demonstrates consistent disease‑modifying effects in mild to moderate SLE and as an adjunct DMARD in rheumatoid arthritis.
Benefits include fewer flares and a steroid‑sparing effect after six to twelve months of treatment.
Clinical effectiveness correlates strongly with adherence and appropriate dosing, typically 200–400 mg daily and weight‑based regimens in children.
Patients often report early gastrointestinal upset that usually settles with dose timing and later concerns about vision, which are managed through screening and specialist review.
Indications and expanded uses (MHRA‑approved and off‑label)
Patients often wonder what hydroxychloroquine is authorised to treat in the UK.
UK licensed indications include long‑term use for rheumatoid arthritis, systemic lupus erythematosus and discoid lupus, and dermatological conditions caused or aggravated by sunlight; it is also used for malaria in some settings.
Within NHS practice hydroxychloroquine is commonly used for cutaneous lupus and other dermatological autoimmune presentations as an established therapy.
Off‑label use persists in specialist clinics for certain inflammatory dermatoses or as an adjunct in paediatric rheumatology if standard agents are unsuitable, and such use should follow specialist review.
The COVID‑19 episode prompted MHRA and NHS guidance advising against routine use outside clinical trials because of lack of efficacy and safety concerns.
- Approved indications: rheumatoid arthritis, systemic and discoid lupus, and light-sensitive skin conditions.
- Off‑label situations: selected dermatological autoimmune conditions and some paediatric rheumatology cases after specialist assessment.
- Decision points: specialist referral for initiation, pregnancy considerations and monitoring commitments before long‑term use.
Composition and brand landscape (active ingredient, UK brands and generics)
People frequently ask whether generic hydroxychloroquine is as reliable as branded products.
The active ingredient is hydroxychloroquine sulfate, commonly dispensed as 200 mg film‑coated tablets in the UK market.
Plaquenil (Sanofi) is the most recognised brand, and generic hydroxychloroquine sulfate tablets are also widely available.
Common packaging formats are blister packs of 30 or 60 tablets and pharmacy‑dispensed bottles, and pharmacists should confirm tablet strength and scoring before issuing any divided dose.
| Brand | Typical pack sizes | Supplier / manufacturer |
|---|---|---|
| Plaquenil | 30, 60 tablets of 200 mg | Sanofi |
| Hydroxychloroquine Sulfate (generic) | 30, 60 tablets | Multiple generic manufacturers (Winthrop, Cipla, Ipca) |
| Hydroxychloroquine Winthrop | 30, 60 tablets | Winthrop / generic suppliers |
Contraindications and special precautions (high‑risk groups)
Patients must know when hydroxychloroquine is not suitable.
Absolute contraindications include known hypersensitivity to hydroxychloroquine or other 4‑aminoquinolines and pre‑existing retinopathy.
Full‑strength adult tablets are not appropriate for young children under six years because of overdose risk.
Relative contraindications requiring specialist review include cardiac conduction disorders or ventricular arrhythmia history, severe hepatic or renal impairment, G6PD deficiency, uncontrolled psoriasis and porphyria.
Pregnancy and breastfeeding require individualised risk–benefit discussions, and many specialists continue hydroxychloroquine in pregnancy for SLE because of maternal risk reduction.
Practical lifestyle advice is straightforward: driving is usually unaffected but patients must report any visual changes immediately and avoid driving if vision is impaired.
| Contraindication / risk | Monitoring / action |
|---|---|
| Known hypersensitivity | Do not prescribe |
| Pre‑existing retinopathy | Contraindicated; ophthalmology review |
| Cardiac conduction disorders | Specialist cardiology review and baseline ECG |
| Pregnancy | Risk–benefit discussion with specialist; many continue for SLE |
Dosage guidelines (NHS‑recommended regimens and adjustments)
One of the common concerns is how much plaquenil to take and how dosing reduces risk.
Standard adult dosing in rheumatology is 200–400 mg daily, given as a single dose or divided dosing depending on tolerance and clinician preference.
Many UK clinicians use 200 mg daily for maintenance and 200 mg twice daily for initial titration, mindful of cumulative dose and ideal body weight limits to reduce retinal risk.
Malaria prophylaxis dosing is 400 mg weekly, starting one to two weeks before travel and continued for four weeks after return.
Treatment regimens for malaria use weight‑adjusted loading doses such as an initial 800 mg followed by 400 mg at specified intervals per travel health guidance.
Paediatric dosing is weight‑based at approximately 3–7 mg/kg/day with a maximum of 400 mg and requires ophthalmology oversight.
Dose adjustments are recommended in renal or hepatic impairment and in the elderly, and clinicians should avoid exceeding 5 mg/kg actual body weight to reduce retinopathy risk.
| Indication | Adult dose | Paediatric dose |
|---|---|---|
| Rheumatology (RA/SLE) | 200–400 mg daily | 3–7 mg/kg/day, max 400 mg |
| Malaria prophylaxis | 400 mg weekly | 6.5 mg/kg, up to 400 mg |
| Malaria treatment | Initial 800 mg then 400 mg at 6, 24, 48 hrs | Weight‑adjusted; max cumulative 2 g |
Interactions overview (food and drugs)
Patients and prescribers ask about the safety of taking other medicines with plaquenil.
Hydroxychloroquine interacts with QT‑prolonging agents such as macrolide antibiotics including azithromycin and certain antiarrhythmics, increasing arrhythmia risk.
Concomitant use with hypoglycaemic agents may potentiate hypoglycaemia and requires monitoring of glucose control.
There are interactions with some antiepileptics and with other 4‑aminoquinolines, which should be avoided.
Food and drink interactions are minimal, but taking the tablet with food reduces transient gastrointestinal upset and supports adherence.
Cardiac events have been reported when hydroxychloroquine is co‑prescribed with QT‑prolonging agents, so an ECG prior to initiation is advised in patients with cardiac risk.
| High‑risk drug pair | Clinical action |
|---|---|
| Hydroxychloroquine + Azithromycin | Avoid where possible; if necessary perform ECG monitoring |
| Hydroxychloroquine + Antiarrhythmics | Specialist review and ECG monitoring |
| Hydroxychloroquine + Hypoglycaemics | Monitor blood glucose and counsel patient on hypoglycaemia signs |
Comparable medicines and prescribing preferences (NHS alternatives)
Clinicians deciding between DMARDs weigh efficacy, monitoring burden and reproductive safety.
Hydroxychloroquine is often combined with or used instead of other DMARDs such as methotrexate, sulfasalazine or leflunomide depending on disease severity and comorbidities.
For malaria, chloroquine remains an alternative in regions with sensitive strains, while artemisinin derivatives are used where resistance is present.
Comparative pros and cons note that hydroxychloroquine is generally well tolerated and is considered safe in many pregnancy SLE cases, with a low monitoring burden outside ophthalmic checks.
Methotrexate can be more effective in some RA phenotypes but requires more intensive toxicity monitoring and is teratogenic.
| Medicine | Pros | Cons |
|---|---|---|
| Hydroxychloroquine | Well tolerated, safe in many pregnancies, low monitoring aside from eye checks | Slower onset than some DMARDs; retinal monitoring required |
| Methotrexate | Higher efficacy for many RA presentations | Teratogenic; requires blood monitoring and folic acid supplementation |
| Chloroquine | Alternative for malaria in sensitive regions | Higher toxicity profile and resistance limits use |
When choosing therapy, clinicians assess disease severity, pregnancy plans, comorbidities including cardiac and liver disease, monitoring capacity and patient preference.
Frequently asked questions
Q1: Will hydroxychloroquine affect my driving?
A1: Not directly, but report any new visual disturbance immediately and do not drive if vision is impaired.
Q2: How soon will I feel better?
A2: Symptomatic improvement for SLE or RA often begins within one to two months, with full benefit taking longer.
Q3: Is it safe in pregnancy?
A3: Many rheumatologists continue hydroxychloroquine in pregnancy for SLE after a specialist risk–benefit discussion.
Q4: What monitoring is needed?
A4: Baseline ophthalmology assessment and annual screening for long‑term users; consider ECG if cardiac risk is present.
Guidelines for proper use (UK pharmacist counselling and NHS support)
Pharmacists should lead with patient concerns when counselling about plaquenil.
Start by confirming the indication, dose, weight and expected time to benefit, usually one to two months for autoimmune indications.
Discuss common side effects such as nausea and skin reactions and explain red‑flag symptoms including vision changes and palpitations.
Document all current prescription and over‑the‑counter medicines to screen for interactions, particularly QT‑prolonging drugs.
Provide written leaflets, set up repeat dispensing or NHS Electronic Prescription Service where appropriate and signpost to rheumatology nurse helplines and ophthalmology services for baseline and annual screening.
Encourage Yellow Card reporting for any suspected adverse reactions and advise storage at room temperature away from moisture and light.
- Pharmacist checklist: confirm indication; verify dose and tablet strength; screen interactions; advise on monitoring; set up repeat dispensing.
- Local NHS support: rheumatology clinics, ophthalmology services, NHS 111 and local GP for urgent matters.
Delivery across the United Kingdom
| City | Region | Delivery Time |
|---|---|---|
| London | England | 9–21 days |
| Birmingham | England | 9–21 days |
| Manchester | England | 9–21 days |
| Glasgow | Scotland | 9–21 days |
| Leeds | England | 9–21 days |
| Liverpool | England | 9–21 days |
| Bristol | England | 9–21 days |
| Edinburgh | Scotland | 9–21 days |
| Sheffield | England | 9–21 days |
| Newcastle | England | 9–21 days |
| Cardiff | Wales | 9–21 days |
| Belfast | Northern Ireland | 9–21 days |
| Leicester | England | 9–21 days |
| Coventry | England | 9–21 days |



