
Ranexa
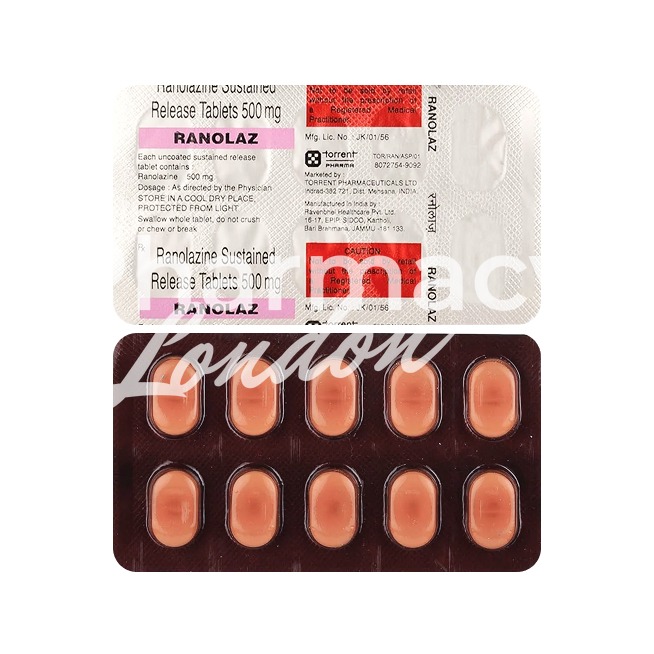
In brief
- In our pharmacy, you can buy Ranexa without a prescription, with delivery in 9–21 days throughout the United Kingdom. Discreet and anonymous packaging.
- Ranolazine (Ranexa) is used for the treatment of chronic stable angina; it works primarily by inhibiting the late inward sodium current (late INa), reducing intracellular calcium overload, lowering diastolic tension and myocardial oxygen consumption without significantly affecting heart rate or blood pressure.
- The usual starting dose is 375 mg prolonged‑release twice daily; after 2–4 weeks it is increased to 500 mg twice daily and, based on response and tolerability, up to a maximum of 750 mg twice daily.
- The form of administration is oral extended‑release tablets.
- The effect of the medication typically begins within 1–2 hours after dosing (peak concentrations are reached a few hours after an ER dose), with some clinical benefit developing over days.
- The duration of action is approximately 12 hours with twice‑daily dosing (extended‑release formulation provides sustained effect over this interval).
- Avoid excessive alcohol while taking Ranexa; alcohol may increase dizziness and other side effects and could potentiate cardiac effects such as QT prolongation — exercise caution and consult a clinician.
- The most common side effects are constipation, nausea, headache and dizziness (constipation is frequently reported).
- Would you like to try Ranexa without a prescription?
Basic Ranexa information
- INN (international nonproprietary name): Ranolazine.
- Brand names available in the United Kingdom: Ranexa; generic ranolazine (e.g. Accord).
- ATC code: C01EB18 (Antianginal drugs, other antianginal agents).
- Forms and strengths: Prolonged‑release oral tablets in 375 mg, 500 mg and 750 mg strengths.
- Manufacturers in the United Kingdom: Menarini and Accord (generics).
- Registration status in the United Kingdom: Prescription‑only; approved for chronic stable angina and recommended for specialist supervision.
- OTC / Rx classification: Rx (prescription only) in the United Kingdom.
Legal status and availability in the UK
In our online pharmacy, Ranexa is available without a prescription, with discreet delivery to the United Kingdom in 9–21 days.
Clinical effectiveness in the UK
Is ranolazine effective for patients who still have angina despite standard therapy?
In NHS practice, ranolazine is typically initiated by cardiologists or specialist clinics for persistent angina despite first‑line agents.
Many patients experience reduced angina frequency and better exercise tolerance after adding ranolazine to therapy.
Ranolazine’s neutral effect on heart rate and blood pressure means it is often chosen where hypotension or bradycardia limit alternatives.
UK safety monitoring emphasises baseline and follow‑up ECGs to watch the QT interval, together with renal and liver function checks and a medication review for CYP3A interactions.
Practical NHS considerations include liaison with the patient’s GP for repeat prescribing, adding e‑prescription summaries to patient records, and pharmacist counselling to support adherence.
Indications and expanded uses
What is ranolazine officially approved for, and where is it being tried off‑label?
Licensed indication: ranolazine (INN ranolazine; brand Ranexa) is approved for chronic stable angina when symptoms persist despite other therapies and is used as an add‑on rather than first‑line in the NHS.
Off‑label or investigational uses seen in UK cardiology practice include suppression of atrial fibrillation and adjunctive therapy after revascularisation, but these remain investigational and vary between trusts.
Paediatric use is not approved and safety/efficacy have not been established.
In private clinics, clinicians sometimes trial ranolazine for refractory symptomatic angina under cardiology supervision with shared decision‑making and clear documentation.
- Approved indication: Chronic stable angina as an add‑on therapy.
- Off‑label uses: Atrial fibrillation suppression; adjunct post‑revascularisation (investigational).
- Not recommended: Paediatric use; routine first‑line monotherapy.
Composition and brand landscape
Who makes ranolazine and what strengths are available in the UK market?
INN: ranolazine is supplied in extended‑release oral tablets.
In the United Kingdom the principal brand is Ranexa, with generics marketed by Accord and other suppliers also present.
Available strengths in the UK are 375 mg, 500 mg and 750 mg prolonged‑release tablets.
ATC classification is C01EB18 (other antianginal agents).
| Strength | Brand | Manufacturer |
|---|---|---|
| 375 mg ER | Ranexa | Menarini / generics (Accord) |
| 500 mg ER | Ranexa | Menarini / generics (Accord) |
| 750 mg ER | Ranexa | Menarini / generics (Accord) |
Contraindications and special precautions
Who must not take ranolazine, and what should pharmacists check before supply?
Absolute contraindications include known hypersensitivity to ranolazine, moderate or severe hepatic impairment, severe renal impairment, concomitant use with strong CYP3A inhibitors (for example ketoconazole and clarithromycin) and documented QT‑prolongation syndromes.
Relative precautions include mild hepatic impairment, mild to moderate renal impairment, elderly patients who may be more sensitive, and a history of arrhythmias.
Practical UK advice: obtain baseline ECG and LFTs/renal function before initiation, review concurrent prescribed and over‑the‑counter CYP3A modulators, and counsel patients to report syncope or new palpitations immediately.
Driving and alcohol: advise caution because dizziness or syncope can occur; suggest limiting alcohol until tolerance is clear.
- Contraindications: Moderate or severe hepatic impairment; severe renal impairment; strong CYP3A inhibitors; known QT prolongation; allergy to ranolazine.
- Monitoring checklist for pharmacists: Baseline ECG, LFTs, eGFR/creatinine, medication reconciliation for CYP3A/CYP2D6 modulators, counsel on adverse signs.
Dosage guidelines
How is ranolazine dosed and what adjustments are needed for organ impairment?
Standard adult dosing for chronic stable angina is ranolazine 375 mg prolonged‑release twice daily initially, increased after 2–4 weeks to 500 mg twice daily and, depending on response and tolerability, to a maximum of 750 mg twice daily.
Ranolazine is not approved for children.
Dose adjustments: contraindicated in moderate or severe hepatic impairment and in severe renal impairment; use with caution in mild hepatic impairment and in mild to moderate renal impairment.
In NHS practice prescriptions are typically started by a cardiologist with clear communication to the GP for repeat prescribing, and pharmacists should stress twice‑daily timing and not to split or crush the extended‑release tablets.
| Patient group | Starting dose | Titration / max |
|---|---|---|
| Adults | 375 mg twice daily | Increase to 500 mg twice daily after 2–4 weeks, then up to 750 mg twice daily if needed |
| Moderate or severe hepatic impairment | Contraindicated | Do not use |
| Elderly | Start low; monitor | Adjust based on tolerability and ECG |
Interactions overview
Can ranolazine be taken safely with other medicines?
Ranolazine is metabolised primarily via CYP3A and to a lesser extent CYP2D6, making strong CYP3A inhibitors contraindicated and inducers likely to reduce efficacy.
Concomitant use with certain macrolide antibiotics, azole antifungals and some antiretrovirals requires caution or avoidance because they alter ranolazine plasma concentrations.
Co‑prescription with QT‑prolonging drugs increases the risk of torsade de pointes and should prompt careful ECG review and specialist advice.
There are no major food interactions requiring avoidance of specific foods, though alcohol may worsen dizziness and should be limited.
- Contraindicated drugs: Strong CYP3A inhibitors such as ketoconazole and clarithromycin.
- Use with caution: Moderate/weak CYP3A inhibitors or inducers, and co‑medications that prolong QT interval.
Comparable medicines and preferences
When should clinicians consider ranolazine instead of other antianginals?
Ranolazine is usually considered as an add‑on when beta‑blockers, calcium‑channel blockers or nitrates are insufficient or poorly tolerated.
Common NHS alternatives include isosorbide mononitrate/dinitrate, amlodipine, diltiazem, verapamil and beta‑blockers such as bisoprolol or metoprolol.
Advantages of ranolazine include limited effect on heart rate and blood pressure, which helps when hypotension or bradycardia are concerns.
Disadvantages are the QT risk, potential CYP interactions, twice‑daily ER dosing and the need for specialist initiation and ECG monitoring.
| Agent | Pros | Cons |
|---|---|---|
| Ranolazine | No major HR/BP effect; useful when hypotension is an issue | QT risk; CYP3A interactions; ER twice‑daily dosing |
| Amlodipine | Once‑daily dosing; effective vasodilation | Can cause peripheral oedema; lowers BP |
| Isosorbide Mononitrate | Effective symptomatic relief | Tolerance development; may lower BP |
| Beta‑Blockers | Reduce heart rate and myocardial oxygen demand | May cause bradycardia and hypotension; not suitable for all |
FAQ
Will ranolazine make my pulse slow?
Typically no — ranolazine does not significantly lower heart rate or blood pressure, which is why it is chosen when those effects are unwanted.
How soon will I feel better?
Symptom reduction can occur within weeks and clinicians usually reassess during dose titration.
Can I take it with my other meds?
Always check with your prescriber or pharmacist — strong CYP3A inhibitors are contraindicated and some QT‑prolonging drugs require caution.
What if I miss a dose?
Take the next dose at the usual time and do not double up.
- ER tablet
- Extended‑release formulation designed for twice‑daily dosing.
- QT prolongation
- Lengthening of the heart’s electrical repolarisation visible on an ECG; can increase arrhythmia risk.
Guidelines for proper use
How should pharmacists counsel patients who are starting ranolazine?
Confirm the indication and the initiating prescriber, usually a cardiologist or specialist clinic.
Check baseline ECG, liver function tests and renal function before supply and ensure medication reconciliation for CYP3A and CYP2D6 interacting drugs.
Advise twice‑daily ER administration and warn patients not to crush or split the tablets.
Counsel on common adverse effects such as dizziness, constipation and headache and advise urgent review for syncope or new palpitations.
Document counselling in the NHS record or EPS and signpost patients to NHS patient portals and cardiology contacts for follow‑up.
| Monitoring | Timing |
|---|---|
| Baseline ECG, LFTs, Renal Function | Before starting |
| ECG and clinical review | 1–3 months after initiation and as clinically indicated |
| Ongoing review | Every clinic visit or with changes in other meds |
Storage: Store ranolazine at 20–25°C in a dry place, protected from moisture and heat, and keep out of reach of children.
Delivery across the United Kingdom
| City | Region | Delivery time |
|---|---|---|
| London | England | 9–21 days |
| Birmingham | England | 9–21 days |
| Glasgow | Scotland | 9–21 days |
| Manchester | England | 9–21 days |
| Leeds | England | 9–21 days |
| Edinburgh | Scotland | 9–21 days |
| Cardiff | Wales | 9–21 days |
| Belfast | Northern Ireland | 9–21 days |
| Newcastle | England | 9–21 days |
| Southampton | England | 9–21 days |
| Plymouth | England | 9–21 days |
| Norwich | England | 9–21 days |



