
Revia
In brief
- In our pharmacy you can buy Revia without a prescription, with delivery in 9–21 days throughout the United Kingdom. Discreet and anonymous packaging.
- Revia (naltrexone hydrochloride) is used to prevent relapse in opioid dependence and to reduce craving in alcohol dependence; it works as an opioid receptor antagonist (competitive mu‑opioid receptor blocker) and is used as part of medication‑assisted treatment (MAT).
- The usual dose is 50 mg orally once daily for adults.
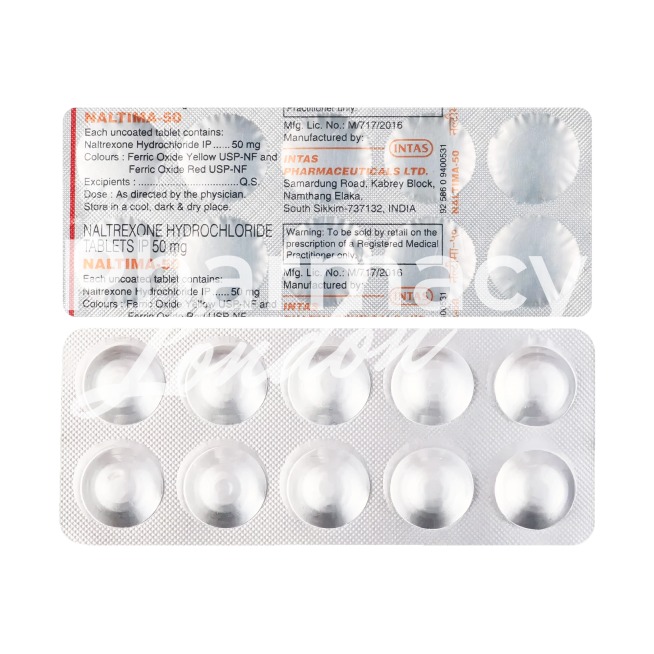
- Form of administration: oral film‑coated, scored 50 mg tablets (blisters or bottles).
- Onset time: oral naltrexone begins to take effect within 30–60 minutes (peak concentrations ~1–2 hours).
- Duration of action: a single 50 mg oral dose has effects for about 24 hours.
- Alcohol warning: although used to treat alcohol dependence, avoid heavy drinking and be aware of liver risk — naltrexone is not recommended in acute hepatitis or severe hepatic impairment and regular liver function monitoring is advised.
- The most common side effect is nausea; other frequent side effects include headache, insomnia, joint or muscle pain, anxiety, fatigue and loss of appetite.
- Would you like to try Revia without a prescription?
Basic Revia information
- INN (international nonproprietary name): Naltrexone hydrochloride
- Brand names available in the United Kingdom: generic naltrexone 50 mg tablets (Revia is the original brand name)
- ATC code: N07BB04
- Forms and strengths: oral tablet 50 mg (film-coated, scored; blisters or bottles)
- Manufacturers in the United Kingdom: generic manufacturers such as Teva, Sandoz and Accord Healthcare
- Registration status in the United Kingdom: prescription only
- OTC / Rx classification: Prescription only (Rx)
Legal status and availability in the UK
Oral generic naltrexone 50 mg tablets are prescription-only in the UK and are available on NHS prescription.
In our online pharmacy, Revia is available without a prescription, with discreet delivery to the United Kingdom in 9‑21 days.
Clinical effectiveness in the UK
Do patients actually do better on naltrexone in NHS practice?
Naltrexone is used primarily for alcohol dependence and for relapse prevention after detoxification from opioids in UK services.
In adherent patients, naltrexone can reduce craving and heavy drinking days, especially when medication is combined with community counselling and mutual‑help referrals.
Oral naltrexone’s real‑world effectiveness for opioid use disorder is limited by adherence problems.
Safety monitoring with baseline and periodic liver function tests is standard practice and improves patient selection and outcomes.
Indications and expanded uses
Is naltrexone only for alcohol and opioid problems?
MHRA‑ and NICE‑aligned practice recognises naltrexone hydrochloride primarily for alcohol dependence and for relapse prevention in opioid dependence after confirmed detoxification.
Off‑label uses seen in specialist NHS or private clinics include adjunctive treatment for some behavioural addictions and experimental low‑dose protocols for binge‑eating disorder, but these remain investigational and require specialist oversight.
Protocols consistently require documented opioid abstinence, typically 7–10 days, before initiation to avoid precipitated withdrawal.
Oral 50 mg tablets taken once daily are the standard form of treatment.
Use in pregnancy is decided case‑by‑case with attention to risks from opioid withdrawal and limited safety data; lactation guidance varies and specialist advice is needed.
- MHRA/NICE‑recognised uses: Alcohol dependence; relapse prevention after opioid detoxification.
- Off‑label/investigational: Behavioural addictions in specialist settings; low‑dose protocols for binge‑eating disorder under supervision.
Composition and brand landscape
Which brands and formulations will the pharmacist actually see?
The active ingredient is naltrexone hydrochloride (INN) and the ATC code is N07BB04 for drugs used in alcohol dependence.
In the UK, naltrexone is mainly supplied as generic oral 50 mg tablets made by manufacturers such as Teva, Sandoz and Accord Healthcare.
Revia was the original branded tablet.
The tablets are film‑coated and scored, supplied in blister packs or bottles.
| Brand | Form | Manufacturer | Availability |
|---|---|---|---|
| Revia | 50 mg tablets | Originally Mallinckrodt | Original brand |
| Generic naltrexone | 50 mg tablets | Teva, Sandoz, Accord Healthcare | Available on prescription |
Contraindications and special precautions
What could make naltrexone unsafe for someone?
Absolute contraindications are recent or current opioid use due to the risk of precipitated withdrawal, acute hepatitis or severe hepatic impairment, and known hypersensitivity to naltrexone or excipients.
Relative contraindications that require close monitoring include moderate hepatic or renal impairment and a history of severe depression or suicidal ideation, given reports of mood‑related adverse effects.
Practical precautions in UK practice include baseline liver function tests and periodic monitoring thereafter, urine or other opioid screening to verify abstinence before initiation, and clear counselling about the blockade of opioid analgesia.
Patients should be warned about dose‑related dizziness or fatigue and advised on driving and safety implications.
Pharmacists must explain emergency plans for acute pain management because naltrexone blocks opioid analgesia and document routes for non‑opioid strategies or specialist supervised opioid analgesia if required.
- Contraindications: recent opioid use; acute hepatitis; severe hepatic impairment; known hypersensitivity.
- Pre‑initiation screening: Baseline LFTs; opioid testing; mood assessment; informed consent documented.
Dosage guidelines
How should naltrexone be dosed and what if a dose is missed?
The standard adult oral dose is 50 mg once daily for alcohol dependence and relapse prevention.
NHS protocols commonly recommend an individualised duration, often a minimum of 3–6 months for alcohol dependence and ongoing specialist review for some opioid‑dependent patients.
Initiation rules require confirmation of opioid abstinence, usually 7–10 days after last opioid use, to avoid precipitated withdrawal.
Children under 18 are not recommended to use naltrexone owing to lack of established safety and efficacy data.
Elderly patients require careful monitoring of renal and hepatic function and clinical judgement about dosing, although routine dose reductions are not specified.
For hepatic impairment avoid use in acute hepatitis or liver failure and consider lower dosing plus more frequent LFTs in moderate disease.
| Population | Typical dose | Notes |
|---|---|---|
| Adults (alcohol) | 50 mg PO daily | Minimum 3–6 months |
| Adults (opioid relapse prevention) | 50 mg PO daily | Initiate only after 7–10 days opioid‑free |
| Children and adolescents | Not recommended | Safety not established |
Interactions overview
Will this drug clash with other medicines I take?
The principal pharmacological interaction is with opioids, where antagonism can cause precipitated withdrawal and will block opioid analgesia.
There are no major food interactions of clinical significance, but patients should avoid heavy alcohol consumption during early treatment because of added liver risk.
Concomitant use with other hepatotoxic medications increases liver risk and clinicians should review statins, high‑dose paracetamol, and other hepatically metabolised agents when prescribing.
Elevated liver enzymes and mood changes have been reported; a full medication review including OTC products and herbal remedies is essential before starting naltrexone.
Pharmacists should coordinate with GPs and hospital teams to document non‑opioid analgesia pathways for emergencies and ensure there are no gaps in care that might expose the patient to unblocked opioids.
- High‑risk interactions: Opioids (precipitated withdrawal/blocking analgesia); hepatotoxic drugs (increased liver risk).
- Practical steps: Check full medication list; advise on paracetamol limits; report suspected interaction reactions via Yellow Card.
Comparable medicines and prescribing preferences
How does naltrexone stack up against other options?
For alcohol dependence, common NHS alternatives are acamprosate and disulfiram, with choice depending on comorbidity, drinking pattern and likely adherence.
Acamprosate is suited to maintenance after detox and has minimal hepatic burden, while disulfiram provides aversive therapy that needs supervised adherence and may suit a motivated, supervised patient.
For opioid dependence, agonist maintenance with methadone or buprenorphine is first‑line for many patients because it reduces cravings and overdose risk under supervision.
Naltrexone’s advantages are that it blocks opioid effects, reduces alcohol cravings in many patients, and has no abuse potential.
Its drawbacks are hepatotoxicity risk, blockade of opioid analgesia and adherence challenges with daily oral dosing; these factors guide whether antagonist or agonist therapy is preferred.
| Drug | Indication | Advantage | Drawback |
|---|---|---|---|
| Naltrexone | Alcohol, opioid relapse prevention | Blocks opioids, reduces craving | Hepatic risk; blocks analgesia; adherence |
| Methadone / Buprenorphine | Opioid dependence | Reduces withdrawal and overdose risk | Requires supervised dispensing; agonist effects |
| Acamprosate | Alcohol dependence | Low hepatic burden | Requires abstinence at start |
Frequently asked questions
Q1: Can I start naltrexone straight after my last opioid use?
A: No. Initiate only after 7–10 days opioid‑free for most opiates, and longer after long‑acting opioids, to avoid precipitated withdrawal; verify with testing and clinical history.
Q2: Will naltrexone affect emergency pain relief?
A: Yes. Naltrexone blocks opioid analgesia; inform GPs and emergency services, carry a card advising non‑opioid pain strategies and plan for specialist managed high‑dose opioid analgesia if needed.
Q3: What monitoring is needed?
A: Baseline liver function tests and periodic repeats, mood screening and adherence checks; report adverse effects via the MHRA Yellow Card system.
Q4: Can I drink alcohol while on naltrexone?
A: The medicine reduces craving and heavy drinking but does not make drinking safe; counsel on reduced tolerance and ongoing liver risks and combine medication with psychosocial support.
- Emergency analgesia steps: Notify GP; carry a treatment card; in emergencies, inform ambulance/ED staff that opioid antagonism may require specialist pain management.
Guidelines for proper use
What should pharmacists do at the point of dispensing?
Use a standardised checklist to confirm indication and informed consent, verify opioid abstinence with documented tests and perform baseline LFTs before initiation.
Discuss common side effects such as nausea, headache, insomnia and mood changes, and explain when to seek help or stop the medicine.
Advise on missed‑dose rules: take a missed tablet as soon as remembered unless it is close to the next dose, and do not double up.
Storage guidance for tablets is 20–25°C and protect from moisture and excess heat.
Emphasise referral to IAPT, local alcohol services or community recovery groups and give the patient a written information card about emergency analgesia steps.
| Activity | When | Who |
|---|---|---|
| Baseline LFTs | Before initiation | Prescriber / GP |
| Opioid screening | Before initiation | Prescriber / Clinic |
| Periodic LFTs and mood checks | As per local protocol | GP / Pharmacist |
Delivery across the United Kingdom
| City | Region | Delivery time |
|---|---|---|
| London | Greater London | 9–21 days |
| Birmingham | West Midlands | 9–21 days |
| Manchester | Greater Manchester | 9–21 days |
| Glasgow | Scotland | 9–21 days |
| Leeds | West Yorkshire | 9–21 days |
| Bristol | South West England | 9–21 days |
| Edinburgh | Scotland | 9–21 days |
| Liverpool | Merseyside | 9–21 days |
| Sheffield | South Yorkshire | 9–21 days |
| Newcastle Upon Tyne | North East England | 9–21 days |
| Cardiff | Wales | 9–21 days |
| Belfast | Northern Ireland | 9–21 days |
| Coventry | West Midlands | 9–21 days |
| Plymouth | Devon | 9–21 days |



