
Rifaximin
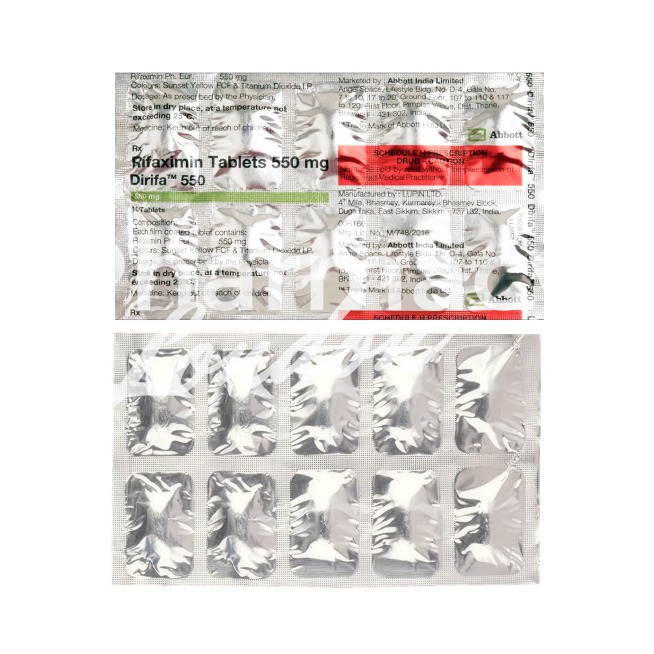
In brief
- In our pharmacy, you can buy rifaximin without a prescription, with delivery in 9–21 days throughout the United Kingdom. Discreet and anonymous packaging.
- Rifaximin is used for traveller’s diarrhoea (caused by non‑invasive E. coli), reduction of risk of recurrence of overt hepatic encephalopathy (HE) and treatment of irritable bowel syndrome with diarrhoea (IBS‑D). It is a non‑absorbable, gut‑selective rifamycin‑derivative antibiotic that acts locally in the gastrointestinal tract to reduce pathogenic bacteria and bacterial overgrowth.
- Usual doses vary by indication: traveller’s diarrhoea — 200 mg three times daily for 3 days; IBS‑D — 550 mg three times daily for 14 days; HE (prevention of recurrence) — typically 550 mg twice daily (long‑term as prescribed).
- Administration is oral: film‑coated tablets (commonly 200 mg and 550 mg).
- Onset of symptomatic improvement for diarrhoea is often within 24–48 hours; for IBS‑D relief may take a few days and prevention of HE recurrence is observed over days to weeks.
- Antibacterial activity in the gut generally persists for 12–24 hours after a dose; clinical benefit is maintained for the duration of the prescribed course (e.g. 3 days for traveller’s diarrhoea, 14 days for IBS‑D, ongoing while taken for HE prevention).
- Avoid excessive alcohol, especially if you have liver disease, as alcohol can worsen hepatic encephalopathy and gastrointestinal symptoms; discuss alcohol use with your clinician.
- The most common side effects are gastrointestinal — for example nausea, abdominal pain and flatulence; headache may also occur.
- Would you like to try rifaximin without a prescription?
Legal status and availability in the UK
In our online pharmacy, rifaximin is available without a prescription, with discreet delivery to the United Kingdom in 9–21 days.
Basic rifaximin information
- INN (international nonproprietary name): rifaximin
- Brand names available in the United Kingdom: Rifaximin 550 mg film-coated tablets (generic)
- ATC code: A07AA11
- Forms and strengths: 200 mg and 550 mg film-coated tablets
- Manufacturers in the United Kingdom: not specified
- Registration status in the United Kingdom: not specified
- OTC / Rx classification: not specified
Clinical effectiveness in the UK
Used alongside lactulose as secondary prophylaxis, rifaximin reduces the recurrence of overt hepatic encephalopathy and HE‑related hospital admissions.
Short courses of rifaximin are used for traveller’s diarrhoea where non‑invasive E. coli is suspected and provide rapid symptomatic relief.
For IBS‑D, UK gastroenterology practice is variable; rifaximin may be tried off‑label in refractory cases after dietary and non‑antibiotic measures have failed.
The overall safety profile is favourable, while clinicians remain alert to antibiotic‑associated diarrhoea and rare allergic reactions.
Indications and expanded uses (MHRA approval and off‑label practice)
Which conditions is rifaximin actually licensed for, and where is it used off‑label?
Core labelled indications include traveller’s diarrhoea due to non‑invasive E. coli, reduction in risk of recurrence of overt hepatic encephalopathy.
In the UK the MHRA licensing historically reflects traveller’s diarrhoea and hepatic encephalopathy as primary indications.
Off‑label use in NHS settings is generally conservative.
Gastroenterology teams may consider rifaximin for refractory IBS‑D after diet, psychological therapies and other pharmaceuticals have been trialled.
UK prescribers emphasise shared decision‑making, documented rationale and review plans when prescribing off‑label.
- Traveller’s diarrhoea
- Typical patient group: adolescents and adults ≥12 years.
- Usual labelled dose: 200 mg three times daily for three days.
- Hepatic encephalopathy
- Typical patient group: adults with prior overt HE episodes.
- Usual labelled dose: 550 mg twice daily for reduction of recurrence.
Composition and brand landscape (active ingredient, UK brands, packaging)
What is rifaximin and how is it supplied in the UK?
Rifaximin is the active substance, an oral non‑absorbable rifamycin derivative acting locally in the gut.
- Rifaximin 550 mg film‑coated tablets — generic presentation available in the UK.
| Dose strength | Common packaging |
|---|---|
| 200 mg | Small blister packs (e.g., short 3‑day courses) |
| 550 mg | Larger blister packs or bottles for maintenance regimens |
Contraindications and special precautions (high‑risk groups)
Who should not take rifaximin, and when should clinicians be cautious?
Absolute contraindication is hypersensitivity to rifamycins, including the rifampicin family.
Pregnancy and breastfeeding require a careful discussion as systemic exposure is minimal but evidence is limited.
Elderly patients should be monitored more closely because of a higher baseline risk of antibiotic‑associated complications such as C. difficile infection.
In hepatic encephalopathy, rifaximin is indicated to reduce recurrence, but clinicians should balance dosing with clinical monitoring and concomitant lactulose therapy.
There are no general driving or alcohol prohibitions in product literature, but patients must be advised not to drive if they feel dizzy or excessively drowsy.
- Checklist: Confirm no history of rifamycin allergy before prescribing.
- Checklist: Discuss pregnancy plans and breastfeeding; record the discussion in the clinical record.
- Checklist: Monitor for worsening diarrhoea, blood in stools or signs of C. difficile.
Rare hypersensitivity reactions and C. difficile infections have been reported, but such events remain uncommon.
Dosage guidelines (NHS‑aligned regimens and special populations)
What doses do UK clinicians use in practice, and how are special populations handled?
Traveller’s diarrhoea: 200 mg three times daily for three days is the common short‑course regimen for non‑invasive E. coli in patients aged 12 and over.
Hepatic encephalopathy: 550 mg twice daily is widely used for reduction of recurrence and may be prescribed as maintenance alongside lactulose.
IBS‑D: a 14‑day course of 550 mg three times daily is the regimen used in trials; in the UK this use is largely off‑label.
| Indication | Typical dose | Duration | UK licensing status |
|---|---|---|---|
| Traveller’s diarrhoea | 200 mg TID | 3 days | Generally recognised |
| Hepatic encephalopathy | 550 mg BID | Long‑term maintenance when indicated | Recognised |
| IBS‑D | 550 mg TID | 14 days | Limited UK licensing; used off‑label in some cases |
Renal dosing adjustments are rarely required due to minimal systemic absorption.
Paediatric use is generally limited to adolescents aged 12 years and older for traveller’s diarrhoea.
Always follow local formulary guidance and record the planned review date in the NHS record.
Interactions overview (food, drink, drug interactions and Yellow Card reports)
Will rifaximin interact with other medicines or food?
Because rifaximin is minimally absorbed, systemic drug interactions are uncommon.
Relevant interactions include concurrent rifamycin antibiotics which may increase allergy risk and theoretical induction effects with systemic rifamycins.
There are no major food restrictions, though patients may take tablets with food if this improves tolerability.
Antacids are not routinely contraindicated but follow local guidance if combining with other GI agents.
- Interaction checklist: Avoid combining with other rifamycins unless clinically justified and documented.
- Interaction checklist: Monitor for microbiome disruptions and possible selection of resistant gut organisms.
Suspected side effects can be reported through the MHRA Yellow Card scheme.
Comparable medicines and prescribing preferences (NHS alternatives)
What are the typical alternatives clinicians consider instead of rifaximin?
For traveller’s diarrhoea, alternatives include azithromycin for suspected invasive pathogens and, less commonly, ciprofloxacin where appropriate.
For hepatic encephalopathy, lactulose remains the first‑line therapy for acute and maintenance needs, with rifaximin acting as an adjunct to reduce recurrence.
For IBS‑D, clinicians favour non‑antibiotic approaches such as the low FODMAP diet, loperamide for symptom control, bile acid sequestrants when bile‑acid diarrhoea is suspected, and neuromodulators.
- Pros for rifaximin: gut selectivity and minimal systemic effects; useful adjunct in HE and effective short courses for traveller’s diarrhoea.
- Cons for rifaximin: limited formal IBS‑D licensing in the UK and stewardship concerns about gut resistance.
NHS prescribers follow stepwise, evidence‑based approaches and document the rationale when choosing rifaximin as part of therapy.
Frequently asked questions
Q1: Can I get rifaximin on the NHS?
A1: If clinically indicated, your GP or hospital team can prescribe rifaximin.
Q2: Is rifaximin safe in pregnancy?
A2: Evidence is limited because systemic absorption is minimal; discuss risks and alternatives with your clinician before taking it in pregnancy or while breastfeeding.
Q3: Will rifaximin affect my driving or drinking alcohol?
A3: There are no specific restrictions, but do not drive if you feel dizzy or excessively drowsy, and discuss alcohol with your prescriber.
Q4: Can I buy rifaximin over the counter?
A4: No – rifaximin is a prescription‑only medicine in the UK.
Guidelines for proper use (pharmacist counselling style and NHS advice)
What should pharmacists and prescribers tell patients when rifaximin is supplied?
Confirm the indication and document it clearly in the NHS clinical record.
Explain the dose, duration and purpose of therapy, for example 200 mg TID for three days for traveller’s diarrhoea, or 550 mg BID for HE maintenance where indicated.
Advise patients to complete the prescribed course unless otherwise instructed and to report worsening diarrhoea, blood in stools or signs of severe abdominal pain.
Warn about the risk of antibiotic‑associated diarrhoea and the need to seek prompt advice if symptoms suggest C. difficile infection.
Storage: keep tablets in their original packaging at room temperature and out of reach of children.
Safety netting: report suspected adverse reactions using the Yellow Card scheme and schedule review dates for repeat prescriptions in the NHS record or patient portal.
- Step 1: Verify indication and check allergy history before dispensing.
- Step 2: Give clear verbal and electronic instructions about dose and duration.
- Step 3: Provide safety netting advice about when to contact NHS 111 or the GP.
- Step 4: Record the supply, counsel about storage and arrange a follow‑up or review date.
Delivery across the United Kingdom
| City | Region | Delivery time |
|---|---|---|
| London | England | 9‑14 days |
| Birmingham | England | 9‑14 days |
| Manchester | England | 9‑14 days |
| Glasgow | Scotland | 9‑14 days |
| Edinburgh | Scotland | 9‑14 days |
| Bristol | England | 9‑14 days |
| Leeds | England | 9‑14 days |
| Cardiff | Wales | 9‑14 days |
| Belfast | Northern Ireland | 9‑14 days |
| Newcastle | England | 14‑21 days |
| Southampton | England | 14‑21 days |
| Plymouth | England | 14‑21 days |
| Swansea | Wales | 14‑21 days |



