
Salazopyrin
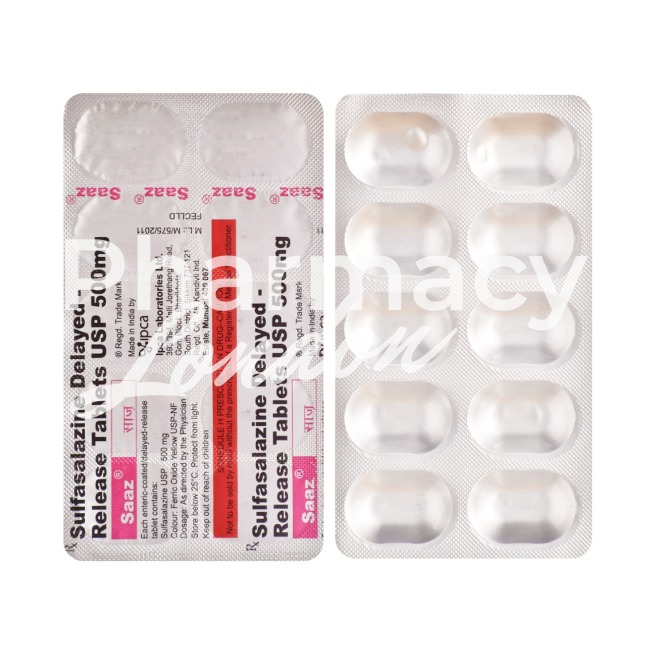
In brief
- In our pharmacy, you can buy Salazopyrin without a prescription, with delivery in 9–21 days throughout the United Kingdom. Discreet and anonymous packaging.
- Salazopyrin (sulfasalazine) is used for ulcerative colitis, rheumatoid arthritis and juvenile idiopathic arthritis; it is converted in the colon to 5‑aminosalicylic acid (anti‑inflammatory) and sulfapyridine (antibacterial and immunomodulatory), which together reduce intestinal inflammation and modulate immune activity.
- Usual dosages: for ulcerative colitis adults 1–2 g/day initially, maintenance commonly 2 g/day (severe up to 4 g/day); for rheumatoid arthritis start ~0.5 g/day and titrate to ~2 g/day (max ~3 g/day); children ≥6 years 30–50 mg/kg/day (up to ~2 g/day).
- Form of administration: oral tablets (immediate‑release 500 mg and delayed‑release/enteric‑coated 500 mg); taken with food and a full glass of water.
- Onset time: symptomatic benefit for ulcerative colitis may begin in 3–6 weeks; for rheumatoid arthritis onset is slower, often 6–12 weeks or more.
- Duration of action: effects are maintained with regular daily dosing for ongoing therapy; the active metabolite (sulfapyridine) has a plasma half‑life typically in the range of about 7–17 hours, so dosing is usually split across the day.
- Alcohol warning: avoid excessive alcohol; alcohol may increase gastrointestinal side effects and the risk of liver toxicity — exercise caution, especially with existing liver disease.
- The most common side effect is gastrointestinal upset (nausea, vomiting, abdominal pain and diarrhoea); other frequent effects include headache, rash, reversible orange/yellow discolouration of urine or skin and mild haematological changes.
- Would you like to try Salazopyrin without a prescription?
Basic Salazopyrin information
- INN (international nonproprietary name): Sulfasalazine
- Brand names available in the United Kingdom: Salazopyrin; Salazopyrin EN-Tabs; generic sulfasalazine
- ATC code: A07EC01
- Forms and dosages: immediate‑release tablets 500 mg; delayed‑release EN‑Tabs 500 mg; standard dosing for ulcerative colitis, rheumatoid arthritis and juvenile RA as per product literature
- Manufacturers: Pfizer and various generic manufacturers
- Registration status in the United Kingdom: licensed for ulcerative colitis, rheumatoid arthritis and juvenile idiopathic arthritis; prescription only
- OTC / Rx classification: prescription only (Rx)
Legal status and availability in the UK
Sulfasalazine is a prescription-only medicine (POM) in the UK and is available on NHS prescription.
In our online pharmacy, Salazopyrin is available without a prescription, with discreet delivery to the United Kingdom in 9‑21 days.
Clinical effectiveness in the UK
Patients want to know whether Salazopyrin will reduce flares or joint pain in routine NHS settings.
In NHS practice sulfasalazine (brand: Salazopyrin) remains in routine use for mild to moderate ulcerative colitis for induction and maintenance of remission, and as a disease‑modifying antirheumatic drug in rheumatoid arthritis and juvenile idiopathic arthritis.
Maintenance dosing of around 2 g/day for ulcerative colitis and for rheumatoid arthritis reduces relapse frequency and improves symptoms when treatment is tolerated.
Dosing escalation to maximum licensed levels — up to 4 g/day in severe ulcerative colitis or up to 3 g/day in rheumatoid arthritis — is less common and typically guided by secondary care specialists.
Early gastrointestinal adverse effects and urine discolouration are common tolerability issues that affect adherence.
In rheumatology practice, combination DMARD regimens that include sulfasalazine alongside methotrexate and/or hydroxychloroquine can give better disease control than monotherapy for some patients, supporting its role in stepwise treatment strategies.
Indications and expanded uses
Which conditions is Salazopyrin licensed to treat, and when is it used off‑label?
UK licensing lists ulcerative colitis, rheumatoid arthritis and juvenile idiopathic/rheumatoid arthritis as the standard indications for sulfasalazine.
Specialist teams in the UK may use sulfasalazine off‑label in selected cases, for example in certain spondyloarthritis presentations or inflammatory dermatological conditions when alternative agents are unsuitable and after clear risk/benefit discussion.
Paediatric use is generally from age six years and up, with weight‑based dosing and specialist initiation usual for juvenile rheumatology patients.
Use is prescription only and is commonly started in secondary care with shared‑care transfer to primary care once response and monitoring stability are established.
Absolute contraindications that limit expanded use include known sulfonamide or salicylate allergy, porphyria, intestinal or urinary obstruction and infants under two years.
Checklist for shared‑care transfer:
- Confirmed indication and response documented.
- Baseline blood tests and first monitoring results recorded.
- Clear responsibility for ongoing monitoring and dose adjustments agreed between specialist and GP.
Composition and brand landscape
People commonly ask whether branded or generic Salazopyrin is better tolerated.
The active ingredient is sulfasalazine (INN), most commonly supplied in 500 mg tablets in immediate‑release and delayed‑release enteric‑coated EN‑tabs formats.
In the UK it is available as Salazopyrin and Salazopyrin EN‑Tabs (Pfizer) and as generic sulfasalazine from several manufacturers.
Packaging commonly ranges from 28 to 100 tablet packs, and EN‑tabs delayed‑release formulations are marketed to improve gastrointestinal tolerability in some patients.
For NHS prescribing, generics are routinely used unless a specific brand is clinically indicated for tolerability reasons.
Brand, formulation and typical pack sizes
| Brand | Formulation | Typical pack size |
|---|---|---|
| Salazopyrin | Immediate‑release tablets 500 mg | 28–100 tablets |
| Salazopyrin EN‑Tabs | Delayed‑release/enteric‑coated 500 mg | 28–100 tablets |
Contraindications and special precautions
What warnings should pharmacists and patients never miss?
Absolute contraindications include known allergy to sulfonamides or salicylates, intestinal or urinary obstruction, porphyria and infants under two years.
High‑risk groups needing enhanced caution include the elderly, people with renal or hepatic impairment, those with G6PD deficiency, blood dyscrasias, severe allergic disease or asthma, and pregnant or breastfeeding women unless specialist advice is obtained.
Pharmacists should counsel patients on common benign effects such as reversible yellow‑orange urine or skin discolouration and on reversible oligospermia in men.
Lifestyle advice includes limiting alcohol while liver enzymes are being monitored and exercising caution with driving until dizziness or visual disturbance status is known.
Monitoring frequency:
- Baseline FBC, LFTs and renal function before starting.
- Early checks at 2 weeks, 4 weeks and 8–12 weeks.
- Thereafter, monitoring usually every three months while on stable therapy.
Dosage guidelines (NHS‑aligned)
How should Salazopyrin be dosed across indications in line with NHS practice?
Ulcerative colitis (adults): Start at 1–2 g/day in divided doses with maintenance commonly around 2 g/day; specialist supervision required for escalation to 4 g/day in severe disease.
Rheumatoid arthritis (adults): Initiate at about 0.5 g/day and titrate up over weeks to approximately 2 g/day given in two to four divided doses; the commonly cited maximum is 3 g/day for selected patients under specialist review.
Juvenile rheumatoid arthritis (children ≥6 years): Typical dosing is 30–50 mg/kg/day in divided doses, up to approximately 2 g/day depending on age and weight.
Administration tips:
- Take with food and a full glass of water to reduce gastrointestinal upset.
- Split doses across the day (two to four times) for better tolerance.
- For elderly or those with renal/hepatic impairment start at the lower end of the dosing range and monitor closely.
Treatment duration expectations:
Ulcerative colitis induction responses are commonly seen within three to six weeks, with maintenance continuing for months to years as relapse prevention.
Rheumatoid arthritis benefits typically start within six to twelve weeks and ongoing therapy is continued where benefit and tolerability are established.
Dosage table by indication
| Indication | Initial dose | Usual maintenance | Max dose |
|---|---|---|---|
| Ulcerative colitis (adult) | 1–2 g/day divided | 2 g/day | 4 g/day |
| Rheumatoid arthritis (adult) | 0.5 g/day, titrate | ~2 g/day | 3 g/day |
| Juvenile RA (≥6 yrs) | 30–50 mg/kg/day | Up to ~2 g/day | As guided by specialist |
Interactions overview
Which drug combinations should trigger extra vigilance?
Sulfasalazine can reduce folate levels and has clinically important interactions with methotrexate due to additive myelosuppression risk, necessitating closer blood monitoring when these drugs are combined.
Interactions with anticoagulants such as warfarin may alter INR and require dose adjustments and monitoring.
Concurrent use with other drugs that cause bone‑marrow suppression, and with certain antibiotics such as trimethoprim, can increase haematological risks.
Agents that alter gastric pH or gastric transit may theoretically affect delayed‑release EN‑tabs, so check formulation history when switching PPI or antacid therapy.
Food and drink notes: There are no absolute food bans, but alcohol should be limited while liver monitoring is ongoing, and large caffeine or strong‑tannin intakes may worsen gastrointestinal side effects.
Pharmacist safety check:
- Confirm current medicines including anticoagulants, methotrexate and recent antibiotics.
- Review recent blood results and monitoring schedule.
- Alert prescriber if combined myelotoxic drugs or INR instability are present.
Comparable medicines and prescribing preferences
When might a prescriber choose mesalazine or another DMARD instead?
For ulcerative colitis, mesalazine agents such as Asacol or Pentasa are commonly used alternatives and tend to have fewer systemic side effects in patients without sulfonamide allergy.
In rheumatoid arthritis, alternatives or complements include methotrexate, leflunomide and hydroxychloroquine, with methotrexate often the anchor DMARD in combination regimens.
Pros of sulfasalazine: long track record and oral dosing.
Cons of sulfasalazine: early gastrointestinal side effects, sulfonamide allergy risk and the requirement for routine blood and liver monitoring.
Prescribing preferences on the NHS depend on indication, allergy history and tolerability.
Comparison summary
| Medicine | Primary indication | Tolerability | Monitoring burden |
|---|---|---|---|
| Sulfasalazine | UC, RA, JIA | GI effects, urine discolouration; sulfonamide allergy risk | Baseline and regular FBC/LFT/renal monitoring |
| Mesalazine | UC | Generally fewer systemic effects | Lower systemic monitoring; formulation‑specific checks |
| Methotrexate | RA, JIA | Hepatotoxicity and bone‑marrow risks | Frequent blood monitoring and folic acid supplementation |
Frequently asked questions
Q: How long until it works?
A: For ulcerative colitis many patients notice improvement within three to six weeks, while for rheumatoid arthritis benefits commonly appear within six to twelve weeks.
Q: What monitoring is needed?
A: Baseline full blood count, liver and renal tests are required, then checks at two, four and eight to twelve weeks, followed by three‑monthly monitoring while stable.
Q: Can I drink alcohol or drive while taking it?
A: Avoid heavy alcohol while liver tests are stabilising and until you have specialist advice; only drive if you are not experiencing dizziness or visual disturbance.
Q: What if I miss a dose?
A: Take as soon as you remember unless the next dose is due soon; do not double the next dose.
When to seek help:
- High temperature, sore throat or mouth ulcers.
- Unexplained bruising or bleeding.
- New rash, jaundice or persistent vomiting.
Guidelines for proper use and UK pharmacist counselling
What should a pharmacist cover at the dispensing point?
Confirm the indication and the exact brand or formulation supplied, for example whether the patient has received immediate‑release sulfasalazine tablets or delayed‑release EN‑tabs.
Review contraindications and current medicines, with a focussed check for methotrexate, anticoagulants and antibiotics such as trimethoprim.
Explain the dosing schedule clearly and highlight administration tips: take with food, split doses and drink a full glass of water with each dose.
Document the monitoring schedule and remind patients about the need for blood tests at baseline, at two to twelve weeks and then typically every three months.
Advise on common expected effects such as yellow‑orange urine and reversible oligospermia in men, and provide clear stopping rules: stop and seek urgent review for fever, persistent sore throat, new rash, jaundice or severe gastrointestinal symptoms.
Encourage patients to report side effects to the MHRA Yellow Card scheme and use NHS tools such as the NHS App for blood test reminders and repeat prescriptions.
Pharmacist counselling checklist
- Confirm formulation and dosing schedule.
- Review allergies, pregnancy plans and interacting medicines.
- Explain monitoring timetable and how results will be communicated.
- Advise on common side effects and urgent red flags.
- Signpost to NHS and patient support resources.
Delivery across the United Kingdom
| City | Region | Delivery Time |
|---|---|---|
| London | Greater London | 9–21 days |
| Birmingham | West Midlands | 9–21 days |
| Manchester | Greater Manchester | 9–21 days |
| Glasgow | Scotland | 9–21 days |
| Edinburgh | Scotland | 9–21 days |
| Liverpool | Merseyside | 9–21 days |
| Bristol | South West | 9–21 days |
| Leeds | West Yorkshire | 9–21 days |
| Sheffield | South Yorkshire | 9–21 days |
| Newcastle | Tyne and Wear | 9–21 days |
| Brighton | East Sussex | 9–21 days |
| Plymouth | Devon | 9–21 days |
| Cardiff | Wales | 9–21 days |



