
Spironolactone
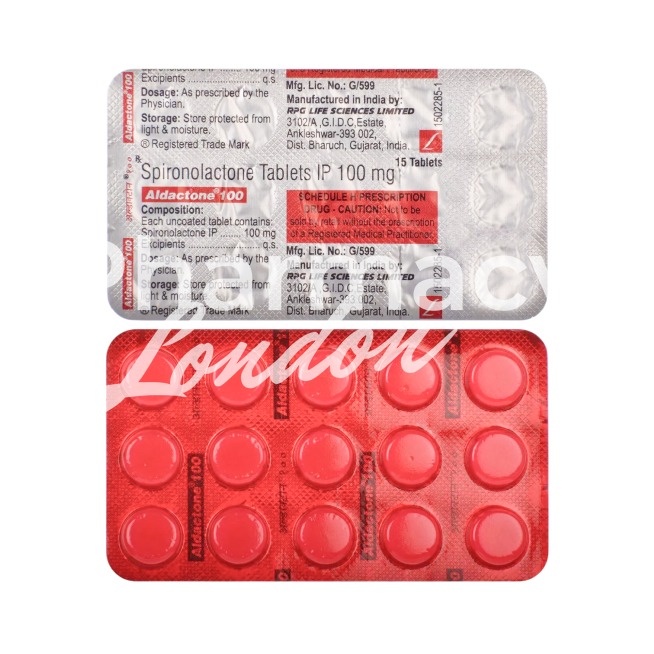
In brief
- Spironolactone (Aldactone and generics) is a prescription-only (Rx) medicine in the UK and should be dispensed with a doctor’s prescription.
- Spironolactone is used for oedema (heart failure, cirrhosis, nephrotic syndrome), hypertension, primary aldosteronism, hypokalaemia prevention, and off‑label for acne and hirsutism; it is an aldosterone antagonist/potassium‑sparing diuretic that blocks aldosterone receptors in the distal nephron (reducing sodium reabsorption and potassium excretion) and has anti‑androgenic effects.
- Usual adult doses vary by indication: oedema 25–200 mg/day (commonly ~100 mg/day); hypertension 25–100 mg/day; heart‑failure adjunct 12.5–50 mg/day; acne/hirsutism 50–200 mg/day; paediatric dosing is weight‑based and specialist‑led (eg 1–3 mg/kg/day where used).
- Administered orally, most commonly as tablets (25 mg, 50 mg, 100 mg); combination tablets with hydroflumethiazide are also available; oral suspension is less common and may be compounded by pharmacies.
- Onset: the diuretic/antikaliuretic effect usually begins within 24–72 hours (peak effect often in 2–3 days); anti‑androgenic benefits for acne/hirsutism take longer, commonly 3–6 months to become apparent.
- Duration of action: clinical diuretic effect can persist for 24–72 hours due to active metabolites (daily dosing is typical); cosmetic/endocrine effects continue only while treatment is maintained and may take months to develop.
- Alcohol: avoid excessive alcohol while taking spironolactone — alcohol can worsen low blood pressure, dehydration and dizziness and may increase the risk of adverse effects.
- The most common side effects include gastrointestinal upset (nausea, vomiting, diarrhoea) and electrolyte disturbances such as hyperkalaemia; other frequent effects include drowsiness, menstrual irregularities, gynaecomastia and skin rash.
- Would you like to try spironolactone without a prescription?
Basic spironolactone information
- INN (international nonproprietary name): spironolactone
- Brand names available in the United Kingdom: Aldactone; Aldactide (with hydroflumethiazide); generic spironolactone products
- ATC code: C03DA01 (potassium-sparing agent; aldosterone antagonist).
- Forms and strengths: tablets 25 mg, 50 mg, 100 mg; oral suspension (less common); combination tablets with hydroflumethiazide (co-flumactone 25 mg/25 mg, 50 mg/50 mg).
- Manufacturers in the United Kingdom: Pfizer (Aldactone); various generic manufacturers.
- Registration status in the United Kingdom: Prescription-only medicine (POM).
- OTC / Rx classification: Prescription only (Rx); dispensed with a doctor's prescription.
Legal status and availability in the UK
Spironolactone is a prescription-only medicine across the UK.
In our online pharmacy, spironolactone is available without a prescription, with discreet delivery to the United Kingdom in 9–21 days.
Clinical effectiveness in the UK
How well does spironolactone work in routine NHS practice?
On the NHS, spironolactone is widely used as an adjunctive therapy in heart failure, in line with NICE guidance.
It is also prescribed for cirrhotic ascites, resistant hypertension and selected endocrine indications where the clinical team judges benefit outweighs risk.
With appropriate monitoring—baseline potassium and renal function, repeated at one week, one month and then quarterly—spironolactone reduces oedema and improves symptoms in heart failure with reduced ejection fraction (HFrEF).
Prescribers should consult the local formulary for preferred brand and monitoring requirements.
Indications and expanded uses (MHRA, NHS and off‑label)
What is spironolactone authorised to treat, and where is it used off‑label?
UK licensed indications include oedema due to heart failure, cirrhosis and nephrotic syndrome; primary hyperaldosteronism; adjunct therapy in specified resistant hypertension; and mortality benefit settings in heart failure when used with ACEi/ARB and loop diuretics.
Common doses by indication include heart failure adjunctive dosing of 12.5–50 mg daily and oedema dosing usually around 100 mg daily with a range of 25–200 mg daily depending on response and specialist oversight.
Off‑label NHS and private clinic use includes female acne and hirsutism (typical ranges 50–200 mg daily) under dermatology oversight.
Use in paediatrics or pregnancy is specialist-initiated only; local formularies often require caution and explicit documentation for off‑label dermatology use.
- Approved uses: oedema (heart failure, cirrhosis, nephrotic syndrome); primary hyperaldosteronism; adjunct in certain resistant hypertension; heart-failure mortality benefit settings.
- Off‑label uses: female acne and hirsutism (dermatology-managed); specialist paediatric use only.
- Checklist for documentation/consent:
- Confirm indication and discuss expected time to benefit (3–6 months for dermatology).
- Record baseline renal function and potassium.
- Document contraceptive advice for women of childbearing potential when used off‑label for acne.
- Obtain explicit consent for off‑label use and note monitoring schedule in records.
Composition and brand landscape
Which brands and formulations of spironolactone do prescribers and pharmacists encounter in the UK market?
Spironolactone (INN) is available in the UK as Aldactone and as generics, with common tablet strengths of 25 mg, 50 mg and 100 mg and packaging in blister packs or bottles.
ATC classification is C03DA01, confirming its place as a potassium-sparing aldosterone antagonist.
| Brand / form | Strengths | Combo variants | Typical pack sizes |
|---|---|---|---|
| Aldactide | 25 mg/25 mg, 50 mg/50 mg | With hydroflumethiazide | Varied (blister packs / bottles) |
| Aldactone | 25 mg, 50 mg, 100 mg | None | Varied |
| Generic spironolactone | 25 mg, 50 mg, 100 mg | Co-flumactone (with hydroflumethiazide) | Blister packs or bottles |
Contraindications and special precautions
Who should not take spironolactone, and what checks are essential before starting?
Absolute contraindications include acute renal insufficiency, anuria, Addison’s disease (adrenal insufficiency), known hypersensitivity to spironolactone or excipients, and pre‑existing hyperkalaemia.
Relative contraindications that demand close monitoring include renal impairment (particularly CrCl <30 mL/min), significant hepatic dysfunction, pregnancy and lactation caution, elderly frailty and diabetes with nephropathy.
MHRA-style caution and NHS guidance emphasise baseline serum potassium and renal function checks and ongoing monitoring, dose reduction or avoidance in severe impairment, and careful co-prescribing decisions with ACE inhibitors, ARBs and potassium supplements.
- Pre‑prescription checklist:
- Baseline eGFR/creatinine and serum potassium results available.
- Medication reconciliation: ACEi/ARB, NSAIDs, potassium supplements, potassium-sparing diuretics flagged.
- Pregnancy screen or contraception advice for women of childbearing potential when appropriate.
- Document absolute contraindications and obtain specialist advice if relative contraindications present.
Advise patients about lifestyle considerations: dizziness can occur so caution with activities is sensible; alcohol may potentiate hypotension; there are no major interactions with tea or coffee.
Dosage guidelines (NHS‑aligned)
What doses are normally used and how should treatment be started and monitored?
Dosing depends on indication: for heart failure adjunctive therapy, typical doses are 12.5–50 mg once daily.
For oedema the usual adult dose is around 100 mg daily with a typical range of 25–200 mg daily under specialist supervision.
Resistant hypertension dosing usually ranges from 25–100 mg daily; off‑label acne and hirsutism are commonly treated in the 50–200 mg daily range under dermatology follow-up.
Paediatric dosing is specialist-only and generally 1–3 mg/kg/day divided; in the elderly start low and titrate based on response and labs.
| Indication / group | Typical dose range | Monitoring notes |
|---|---|---|
| Heart failure (adult) | 12.5–50 mg/day | Baseline and repeat electrolytes/renal at 1 week, 1 month, then quarterly |
| Oedema | 25–200 mg/day (commonly ~100 mg/day) | Specialist oversight at higher doses; monitor weight and labs |
| Resistant hypertension | 25–100 mg/day | Monitor BP and electrolytes |
| Acne / hirsutism (off‑label) | 50–200 mg/day | Review effect at 3–6 months; contraception discussion for women |
Patient advice for missed doses: take as soon as you remember unless close to the next dose; do not double-up doses.
Overdose signs may include severe hyperkalaemia, drowsiness, confusion and gastrointestinal upset and require emergency attention.
Interactions overview
Which medicines and over‑the‑counter items commonly interact with spironolactone?
The principal interaction concern is additive hyperkalaemia when spironolactone is combined with ACE inhibitors, ARBs, potassium supplements and other potassium-sparing agents such as amiloride and triamterene.
NSAIDs can reduce renal perfusion and have been associated with renal adverse events when co‑prescribed, which may compound the risk of hyperkalaemia.
Hepatic metabolism of active metabolites means potent liver enzyme modulators warrant clinical caution, although CYP interactions are less prominent than the potassium-related interactions.
| Interacting drug / group | Type of interaction | Clinical action |
|---|---|---|
| ACE inhibitors / ARBs | Pharmacodynamic (hyperkalaemia, renal function) | Monitor K+ and renal function closely; adjust dose as needed |
| Potassium supplements / salt substitutes | Increase serum potassium | Avoid or closely monitor; counsel patients not to self‑supplement |
| Amiloride / Triamterene | Synergistic potassium retention | Avoid co‑prescribing where possible; monitor if essential |
| NSAIDs | Reduced renal perfusion, risk of renal injury | Review necessity; monitor renal function |
Medication reconciliation at each review is essential and pharmacists should educate patients to report any new medicines from secondary care or OTC purchases.
Comparable medicines and prescribing preferences
What are the common alternatives to spironolactone and when are they chosen?
Eplerenone is a selective aldosterone antagonist that generally has fewer anti‑androgenic effects and is used when hormonal side effects from spironolactone are problematic.
Amiloride and triamterene are potassium‑sparing diuretics with different effectiveness and side‑effect profiles and are sometimes considered in resistant hypertension regimens.
Thiazide diuretics remain part of the broader toolkit for resistant hypertension but are not potassium‑sparing.
| Agent | Pros | Cons | Prescribing notes |
|---|---|---|---|
| Spironolactone | Proven HFrEF benefit | Anti‑androgenic side effects, hyperkalaemia risk | First‑line adjunct for many HFrEF pathways |
| Eplerenone | Fewer hormonal effects | Licensed mainly for heart failure | Consider if spironolactone side effects unacceptable |
| Amiloride / Triamterene | Potassium‑sparing alternative | Less potent for aldosterone blockade | Used selectively, sometimes in combos |
When switching agents consider washout timing and monitoring plans; document rationale and monitor electrolytes closely after any change.
FAQ — common NHS patient questions
What do patients most often ask about spironolactone, and what should they do?
- Will spironolactone make me go to the loo more? It can increase urine output, especially if you have fluid overload; if you notice troublesome frequency or dizziness, contact your pharmacist or GP.
- Do I need blood tests? Yes — baseline renal function and potassium are required, with repeats at one week, one month and then periodically; call your GP surgery for arranged tests or speak to the pharmacist if unsure.
- Can I take it with my ACE inhibitor? Often yes, but this combination raises hyperkalaemia risk so more frequent blood tests are needed; contact your prescriber immediately if you feel palpitations or muscle weakness.
- What about fertility or pregnancy? Use in pregnancy and breastfeeding is specialist-led; women of childbearing potential prescribed spironolactone for acne should be given contraception advice and a clear discussion about risks.
- When should I seek urgent help? If you develop severe weakness, palpitations, fainting, severe dizziness or signs of dehydration, contact NHS 111, your GP or attend A&E without delay.
Guidelines for proper use and pharmacist counselling
How should pharmacists and prescribers manage spironolactone safely in the NHS setting?
Confirm the indication and check the absolute contraindications before supply and document the reason for treatment in the patient record.
Arrange baseline eGFR/creatinine and serum potassium and provide a clear monitoring schedule to the patient and prescribing team.
Pharmacists should reinforce adherence, counsel on signs of hyperkalaemia such as muscle weakness and palpitations, advise against OTC potassium supplements and review concurrent prescriptions for ACEi/ARB/NSAIDs.
- Counselling points:
- Explain expected timeline for benefit (dermatology: 3–6 months; heart failure: symptomatic benefit may be sooner).
- Provide written monitoring schedule and contact details for arranging blood tests.
- Advise immediate contact with GP or 111 for red‑flag symptoms (severe weakness, palpitations, fainting).
Report suspected adverse reactions to the MHRA Yellow Card scheme and signpost patients to the NHS website for balanced information on side effects and monitoring.
Delivery across the United Kingdom
| City | Region | Delivery time |
|---|---|---|
| London | England | 9–21 days |
| Birmingham | England | 9–21 days |
| Manchester | England | 9–21 days |
| Glasgow | Scotland | 9–21 days |
| Liverpool | England | 9–21 days |
| Leeds | England | 9–21 days |
| Sheffield | England | 9–21 days |
| Bristol | England | 9–21 days |
| Edinburgh | Scotland | 9–21 days |
| Cardiff | Wales | 9–21 days |
| Newcastle upon Tyne | England | 9–21 days |
| Belfast | Northern Ireland | 9–21 days |
| Southampton | England | 9–21 days |



