
Tacrolimus
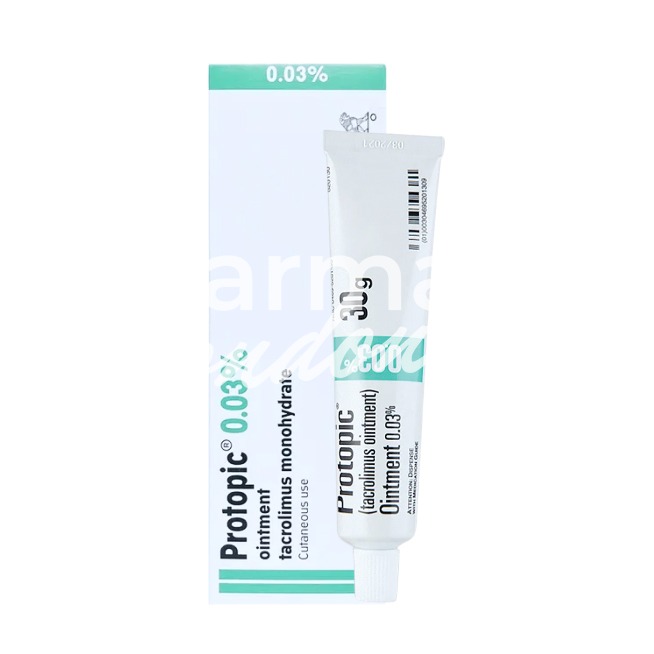
In brief
- In our pharmacy tacrolimus is available; in the UK it is a prescription-only medicine (Rx) for all systemic and topical forms.
- Tacrolimus is used as a systemic immunosuppressant to prevent organ transplant rejection and topically to treat atopic dermatitis and other inflammatory skin conditions; it is a calcineurin inhibitor that suppresses T‑cell activation and reduces cytokine production (eg, IL‑2).
- Usual systemic doses in adults are about 0.1–0.2 mg/kg/day orally divided every 12 hours (cardiac transplants often start lower); paediatric doses are typically 0.15–0.2 mg/kg/day; topical ointment is applied as a thin layer twice daily (0.03% or 0.1%, 0.03% preferred in younger patients).
- Forms of administration include oral capsules (immediate and prolonged-release), intravenous injection (5 mg/ml vial), and topical ointment (0.03% and 0.1%).
- Blood concentrations peak within 1–3 hours after oral dosing and topical relief of itching/inflammation may begin within 48–72 hours, though full clinical benefit for systemic immunosuppression can take days to weeks.
- Duration of action depends on formulation: immediate‑release products are dosed every 12 hours (effective ~12 hours), prolonged‑release formulations are once daily (up to 24 hours); immunosuppressive effects persist while treatment continues.
- Avoid excessive alcohol while taking tacrolimus — alcohol can increase liver strain and may worsen side effects; alcohol is particularly discouraged with systemic therapy and in patients with hepatic impairment.
- The most common side effect is tremor; other frequent adverse effects include headache, hypertension, nausea, renal dysfunction and increased infection risk.
- Would you like to try tacrolimus without a prescription?
Basic tacrolimus information
- INN (international nonproprietary name): Tacrolimus
- Brand names available in the United Kingdom: Prograf® (capsules, vials), Advagraf® (prolonged‑release capsules), Protopic® (ointment 0.03% and 0.1%); generic tacrolimus products are also available.
- ATC code: L04AD02 (systemic immunosuppressant, calcineurin inhibitor); D11AH01 (topical, non‑corticosteroid dermatological)
- Forms and strengths: capsules 0.5mg, 1mg, 5mg; prolonged-release capsules 0.5mg, 1mg, 3mg, 5mg; Injection/IV 5mg/ml; Ointment 0.03% and 0.1% (10g/30g/60g tubes).
- Manufacturers in the United Kingdom: Astellas Pharma (Prograf®, Protopic®, Advagraf®); generics from Sandoz, Mylan and Accord Healthcare.
- OTC / Rx classification: Prescription only (Rx) for all systemic and topical forms.
Legal status and availability in the UK
In our online pharmacy, tacrolimus is available without a prescription, with discreet delivery to the United Kingdom in 9–21 days.
Clinical effectiveness in the UK
How effective is tacrolimus in everyday NHS practice?
Tacrolimus is a cornerstone of solid‑organ transplant maintenance.
Immediate‑release tacrolimus (Prograf® or generic immediate‑release capsules) is commonly given twice daily in renal centres.
Once‑daily prolonged‑release Advagraf® is used where adherence is a concern and to simplify dosing.
Therapeutic drug monitoring is standard of care due to tacrolimus’ narrow therapeutic index and highly variable pharmacokinetics.
Topical tacrolimus ointment (0.03% and 0.1%) is widely used in secondary care for moderate to severe atopic dermatitis when topical corticosteroids are unsuitable.
Topical treatment often reduces itch and improves sleep.
Local burning on topical application and worries about long‑term safety are common challenges for dermatology patients.
- Key NHS outcome metrics: Improved graft survival, reduced acute rejection, routine TDM adherence, improved Dermatology Life Quality Index scores for topical users.
| Use case | Effective outcome | Monitoring need |
|---|---|---|
| Systemic (transplant) | Lower acute rejection, sustained graft function | Frequent trough‑level monitoring, renal function and glucose |
| Topical (eczema) | Reduced severity and flare frequency | Minimal systemic monitoring unless signs of systemic exposure |
Indications and expanded uses (MHRA and NHS practice)
When is tacrolimus prescribed by UK clinicians?
- MHRA-approved uses
- Systemic tacrolimus for prevention of organ rejection in renal, hepatic and cardiac transplants.
- Topical tacrolimus ointment for atopic dermatitis where conventional therapies are unsuitable.
- Common off-label uses in NHS practice
- Topical tacrolimus for lichen planus and refractory vitiligo in specialist dermatology clinics.
- Steroid‑sparing regimens in chronic dermatological disease managed by secondary care.
| Indication | Form | Typical duration |
|---|---|---|
| Renal/hepatic transplant | Oral capsules or IV | Lifelong maintenance |
| Cardiac transplant | Oral capsules | Lifelong maintenance |
| Atopic dermatitis | Topical ointment 0.03%/0.1% | 2–6 week acute courses; intermittent long‑term prevention |
Composition and brand landscape (UK emphasis)
What products will a UK patient see on a prescription form?
The active ingredient across brands is tacrolimus (INN).
Key branded products in the UK include Prograf® for immediate‑release capsules and vials, Advagraf® for prolonged‑release capsules, and Protopic® for topical ointment.
Generic tacrolimus products, for example from Sandoz, Mylan and Accord Healthcare, are also used by hospital trusts.
| Brand | Formulation | Strengths | Typical NHS scenario |
|---|---|---|---|
| Prograf® | Immediate‑release capsules, IV vials | 0.5mg, 1mg, 5mg; 5mg/ml IV | Early post‑transplant dosing and trough‑guided regimens |
| Advagraf® | Prolonged‑release capsules | 0.5mg, 1mg, 3mg, 5mg | Once‑daily switch for adherence concerns |
| Protopic® | Ointment | 0.03%, 0.1% in 10g/30g/60g tubes | Secondary care dermatology for moderate–severe AD |
| Generics (e.g. Adoport) | Capsules | 0.5mg, 1mg, 5mg | Trust formulary choice |
- Storage and transport: store capsules and ointments below 25°C in original packaging and protect from moisture and light.
- IV products require refrigeration at 2–8°C and should not be frozen.
Contraindications and special precautions
Who should not receive tacrolimus, and who needs extra caution?
Absolute contraindication is hypersensitivity to tacrolimus or any excipients listed in the SmPC.
High‑risk groups include patients with pre‑existing renal or hepatic impairment, those with uncontrolled infections, pregnant or breastfeeding individuals unless benefits outweigh risks, and elderly patients with comorbidities.
Concurrent use of nephrotoxic agents such as aminoglycosides and frequent NSAID use increases risk and requires close review.
Driving and machinery operation should be discussed if tremor, dizziness or visual disturbance occur on treatment.
- Absolute versus relative contraindications
- Absolute contraindication means the drug must not be given under any circumstance due to risk of severe reaction.
- Relative contraindication means benefits may outweigh risks with specialist supervision and extra monitoring.
- Pharmacist counselling checklist: confirm hypersensitivity history, review renal and hepatic function, check concurrent medications for nephrotoxins, counsel on infection signs and metabolic monitoring.
Dosage guidelines (NHS‑recommended regimens)
How are doses chosen and adjusted in practice?
Typical adult oral initiation for renal or hepatic transplant recipients ranges from 0.1–0.2 mg/kg/day divided twice daily.
Cardiac transplant initial dosing is typically lower, around 0.075 mg/kg/day divided twice daily.
Paediatric dosing is higher on a mg/kg basis, commonly 0.15–0.2 mg/kg/day, with close therapeutic drug monitoring.
Advagraf® prolonged‑release capsules are used for once‑daily dosing to improve adherence.
Topical Protopic® 0.03% or 0.1% should be applied as a thin layer twice daily for 2–6 weeks per flare, with 0.03% preferred below 16 years.
Reduce systemic doses in hepatic impairment and consider lower starting doses in the elderly.
Never stop systemic tacrolimus abruptly in transplant patients because of graft rejection risk.
| Indication | Form | Adult dose | Paediatric dose | Monitoring notes |
|---|---|---|---|---|
| Renal/hepatic transplant | Oral capsules | 0.1–0.2 mg/kg/day divided q12h | 0.15–0.2 mg/kg/day divided q12h | Trough levels, renal function, glucose, potassium |
| Cardiac transplant | Oral capsules | 0.075 mg/kg/day divided q12h | 0.1–0.2 mg/kg/day | Close cardiovascular and trough monitoring |
| Atopic dermatitis | Topical ointment | Thin layer twice daily (0.03%/0.1%) | 0.03% preferred for <16 years | Local reaction monitoring; systemic monitoring rarely required |
Interactions overview (drugs, food, MHRA reports)
Which medicines and foods change tacrolimus levels?
Tacrolimus is metabolised by CYP3A4 and CYP3A5, so potent inhibitors can raise blood levels and potent inducers can lower them.
Common interacting drug classes include azole antifungals, macrolide antibiotics, calcium‑channel blockers, some anticonvulsants, and rifampicin.
Grapefruit and grapefruit juice should be avoided because they increase tacrolimus exposure.
Interaction-related toxicity can manifest as nephrotoxicity and neurotoxicity; suspected reactions should be reported via the MHRA Yellow Card scheme.
| Drug/agent | Effect on tacrolimus levels | Recommended action |
|---|---|---|
| Azole antifungals (e.g. ketoconazole) | Increase levels (CYP3A inhibition) | Reduce tacrolimus dose; increase TDM frequency |
| Macrolides (e.g. erythromycin) | Increase levels | Avoid if possible; monitor troughs closely |
| Rifampicin | Reduce levels (CYP3A induction) | Avoid or increase tacrolimus dose with close monitoring |
| Grapefruit | Increase levels | Advise avoidance |
CYP3A4 inhibitors and inducers are the most clinically important interaction group for tacrolimus.
Comparable medicines and prescribing preferences
Which alternatives do clinicians consider and why?
Ciclosporin (Sandimmun®) is a calcineurin inhibitor comparator with a different adverse‑effect profile including gingival hyperplasia and hirsutism.
Sirolimus (Rapamune®) offers mTOR inhibition and is used when an alternative mechanism is preferred.
Pimecrolimus (Elidel®) is a topical alternative in dermatology for some patients with atopic dermatitis.
| Agent | Mechanism | Monitoring needs | Common adverse effects |
|---|---|---|---|
| Tacrolimus | Calcineurin inhibitor | Trough‑level TDM, renal function, glucose | Nephrotoxicity, tremor, hyperglycaemia |
| Ciclosporin | Calcineurin inhibitor | Trough‑level TDM, blood pressure, lipids | Gingival hyperplasia, hirsutism |
| Sirolimus | mTOR inhibitor | Lipids, full blood count, renal function | Hyperlipidaemia, delayed wound healing |
| Pimecrolimus | Topical calcineurin inhibitor | Minimal systemic monitoring | Local irritation |
- Pros/cons checklist: tacrolimus offers lower rejection rates than ciclosporin but requires vigilant TDM; monitoring needs inform NHS prescribing choices.
Frequently asked questions
-
Will tacrolimus make me more likely to get infections?
Yes, immunosuppression increases infection risk.
Report fevers, new coughs or other signs of infection promptly to your transplant or dermatology team.
Avoid live vaccines unless advised by your specialist.
-
Can I switch between Prograf® and Advagraf®?
Switching is possible but requires clinician oversight and therapeutic drug monitoring.
Bioavailability and trough targets may differ between immediate‑release and prolonged‑release formulations.
-
How often are blood tests needed?
Early post‑transplant monitoring is frequent — daily to weekly until stable.
Once stable, testing intervals are extended but remain regular for life.
Topical users rarely need systemic monitoring unless there are signs of systemic exposure.
-
Can I buy tacrolimus over the counter?
No, tacrolimus is a prescription‑only medicine in the UK.
Topical formulations normally require a prescription from a GP or dermatologist.
Guidelines for proper use (pharmacist counselling and NHS support)
What should pharmacists tell patients at the counter?
Confirm the indication and the formulation dispensed.
Explain the need for therapeutic drug monitoring with systemic tacrolimus and arrange repeat blood tests where required.
Advise patients to take oral tacrolimus at consistent times and to avoid grapefruit and grapefruit juice.
Demonstrate thin‑layer application for topical tacrolimus and warn about a transient burning sensation on first applications.
Advise against occlusion or use on infected skin without clinician review.
- Monitoring checklist for pharmacists: trough tacrolimus level, renal function (serum creatinine), fasting glucose, serum potassium, blood pressure and signs of neurotoxicity.
NHS support options: register for transplant clinic reminders, access SmPC documents via MHRA resources, and use NHS patient portals for test results and e‑prescription delivery.
Delivery across the United Kingdom
| City | Region | Delivery Time |
|---|---|---|
| London | England | 9–21 days |
| Birmingham | England | 9–21 days |
| Manchester | England | 9–21 days |
| Glasgow | Scotland | 9–21 days |
| Liverpool | England | 9–21 days |
| Leeds | England | 9–21 days |
| Bristol | England | 9–21 days |
| Sheffield | England | 9–21 days |
| Edinburgh | Scotland | 9–21 days |
| Cardiff | Wales | 9–21 days |
| Newcastle | England | 9–21 days |
| Belfast | Northern Ireland | 9–21 days |
| Leicester | England | 9–21 days |
| Plymouth | England | 9–21 days |



