
Tegretol
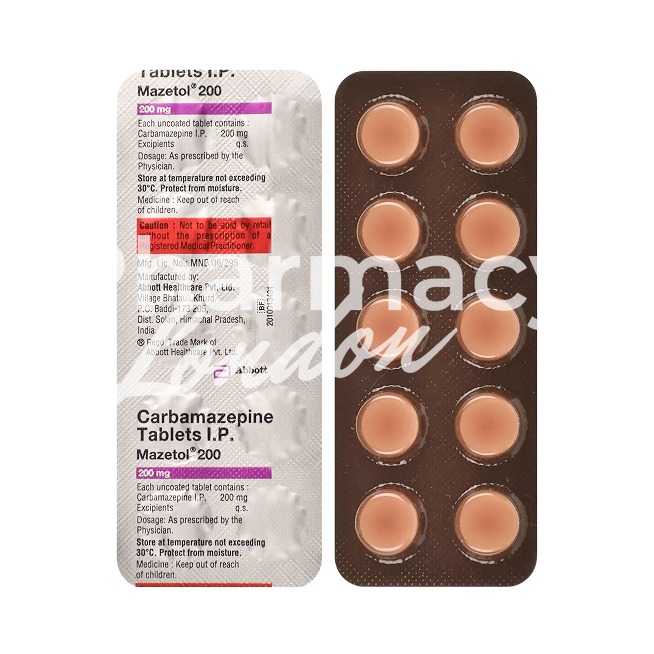
In brief
- Tegretol is a prescription‑only medicine (POM) in the UK and should be obtained from a pharmacy with a valid prescription.
- Tegretol (carbamazepine) is used to treat epilepsy (partial seizures, generalised tonic–clonic and mixed types), trigeminal neuralgia and other neuropathic pain conditions, and in some settings for bipolar disorder; it works mainly by blocking voltage‑gated sodium channels, stabilising hyperexcited neuronal membranes and reducing synaptic transmission (it is also a hepatic CYP enzyme inducer).
- Typical adult doses: epilepsy initial 200 mg once or twice daily with common maintenance 800–1,200 mg/day (divided doses); trigeminal neuralgia often starts 100 mg once or twice daily with maintenance 400–800 mg/day; bipolar dosing commonly 400–600 mg/day initially, adjustable to 400–1,200 mg/day as needed; children often start at ~10–20 mg/kg/day in divided doses—titrate to the lowest effective dose.
- Administered orally: immediate‑release tablets (100 mg, 200 mg, 400 mg), Retard (prolonged‑release) tablets (200 mg, 400 mg) and oral liquid (100 mg/5 mL); no routine injectable formulation—do not split sustained‑release tablets.
- Onset: immediate‑release formulations can begin to have measurable effects within a few hours (commonly 2–8 hours); controlled‑release forms act more slowly; full therapeutic levels and clinical stabilisation may take days to weeks due to auto‑induction of metabolism.
- Duration of action: immediate‑release effects typically last around 8–12 hours (hence divided dosing), while retard/CR formulations provide prolonged action often covering 12–24 hours; note auto‑induction shortens apparent half‑life at steady state.
- Alcohol warning: avoid alcohol while taking Tegretol—alcohol increases drowsiness, dizziness and ataxia, can worsen impaired coordination and cognition and may interfere with seizure control.
- The most common side effects are drowsiness (sedation) and dizziness.
- Would you like to try Tegretol without a prescription?
Basic Tegretol information
- INN (international nonproprietary name): Carbamazepine.
- Brand names available in the United Kingdom: Tegretol; Tegretol Retard.
- ATC code: N03AF01.
- Forms and strengths: tablets 100 mg, 200 mg and 400 mg; Retard (prolonged‑release) tablets 200 mg and 400 mg; oral liquid 100 mg/5 mL; no injectable formulations for routine use.
- Manufacturers in the United Kingdom: Originator Novartis and multiple generics from Teva, Sandoz, Mylan, Zentiva, Stada, Egis and Adamed.
- Registration status in the United Kingdom: Approved by the MHRA and available on prescription.
- OTC / Rx classification: Prescription‑only.
Legal status and availability in the UK
In our online pharmacy, Tegretol is available without a prescription, with discreet delivery to the United Kingdom in 9–21 days.
Clinical effectiveness in the UK
Want to know how people in the NHS actually do on Tegretol?
Many patients with focal epilepsy achieve good seizure control once therapeutic levels are reached.
Slow titration and pharmacist follow‑up help patients stay on treatment.
Adherence challenges in community prescribing are commonly linked to early dizziness, sedation and the need for stepwise titration.
Common adverse effects are dizziness, sedation and mild rash; laboratory abnormalities are monitored routinely.
Monitoring practice across many NHS trusts includes baseline FBC, LFTs and serum sodium at initiation and after dose changes.
Indications and expanded uses
Is Tegretol right for my condition?
MHRA‑approved uses include partial (focal) seizures, generalised tonic–clonic seizures and trigeminal neuralgia.
Carbamazepine is also licensed for prophylaxis of bipolar disorder in patients unresponsive to lithium; other uses, such as acute mania when valproate is unsuitable and some neuropathic pain states, are off‑label specialist practice.
- MHRA‑approved: Epilepsy (partial and generalised tonic–clonic), trigeminal and glossopharyngeal neuralgia, and prophylaxis of bipolar disorder unresponsive to lithium.
- Off‑label / specialist: Acute mania in select cases and certain neuropathic pain presentations.
| Indication | Typical starting dose | Typical maintenance |
|---|---|---|
| Epilepsy (Adult) | 200mg once or twice daily | 800–1200mg/day |
| Trigeminal Neuralgia | 100–200mg/day | 400–800mg/day |
| Bipolar Disorder (Specialist) | 400–600mg/day | 400–1200mg/day |
GPs should document off‑label discussions and monitor response carefully when a specialist recommends carbamazepine.
Patients moving between NHS and private clinics benefit from carrying clear records of indications and monitoring plans.
Composition and brand landscape
Which brand will I pick up from the pharmacy?
Carbamazepine is available as Tegretol and Tegretol Retard in the United Kingdom alongside multiple generics supplied by major manufacturers such as Teva, Sandoz, Mylan and Zentiva.
| Brand | Manufacturer | Forms available | Notes |
|---|---|---|---|
| Tegretol | Novartis | 100mg, 200mg, 400mg | Originator; Retard for sustained release |
| Generic Carbamazepine | Teva / Sandoz / Mylan / Zentiva | 100mg, 200mg, 400mg | 200mg scored versions can be split |
For epilepsy, the MHRA advises that patients taking carbamazepine should be kept on a specific manufacturer’s product, so switching between brands is avoided; contact the prescriber if any issues arise after a change.
Contraindications and special precautions
Who should not take Tegretol?
- Absolute contraindications: Known allergy to carbamazepine or tricyclic compounds, history of bone‑marrow depression, prior Stevens–Johnson syndrome/TEN due to carbamazepine, and concomitant MAOI use.
- Relative cautions: Moderate–severe liver or renal impairment, cardiac conduction disorders, elderly patients (higher hyponatraemia risk), pregnancy unless no alternative and history of blood dyscrasias.
Patients of Han Chinese or Thai origin should be considered for HLA‑B*1502 genetic risk assessment where clinically appropriate, as part of risk minimisation for SJS/TEN.
Lifestyle restrictions include avoiding heavy alcohol during initiation and titration and exercising caution when driving until stability is confirmed.
Pharmacists should counsel on pregnancy planning and the need to report any new rash immediately.
Dosage guidelines
How should I take Tegretol for epilepsy or nerve pain?
| Indication | Initial dose | Typical maintenance |
|---|---|---|
| Epilepsy (Adult) | 200mg once or twice daily | 800–1200mg/day in divided doses |
| Trigeminal Neuralgia | 100–200mg/day | 400–800mg/day |
| Children | 10–20mg/kg/day in 2–3 divided doses | Titrate to effective dose |
| Elderly | Start low, go slow | Titrate carefully due to sensitivity |
Retard or sustained‑release formulations must not be split.
Missed dose advice: take as soon as remembered unless near the next dose and never double up.
Dose adjustments are required in hepatic impairment and when interacting drugs are present; consider therapeutic drug monitoring in complex cases.
Interactions overview
Will Tegretol affect my other medicines?
Carbamazepine is a potent inducer of multiple CYP enzymes, especially CYP3A4, and causes many clinically significant interactions.
Major interactions include reduced efficacy of hormonal contraception, lowered plasma levels of some anticoagulants and direct oral anticoagulants, and altered levels of antipsychotics and antidepressants.
CYP inhibitors such as azole antifungals and certain macrolide antibiotics can raise carbamazepine levels and increase toxicity risk.
| Drug class | Effect |
|---|---|
| Oral Contraceptives | Reduced efficacy; advise additional contraception |
| Warfarin / DOACs | Levels may fall; monitor anticoagulation |
| SSRIs / Antipsychotics | Variable interactions; monitor plasma levels and side‑effects |
| Azole Antifungals / Macrolides | Can increase carbamazepine levels; risk of toxicity |
Patients must tell prescribers and pharmacists about all medicines, including over‑the‑counter products and herbal preparations such as St John’s wort.
Interaction‑related adverse effects can be serious, so monitoring and counselling are essential; report suspected side effects via the Yellow Card scheme.
Comparable medicines and preferences
Are there better options for my condition?
NHS guidance lists several alternatives to carbamazepine depending on the clinical context.
| Indication | First / second line alternatives | Pros / cons |
|---|---|---|
| Trigeminal Neuralgia | Oxcarbazepine; Gabapentinoids | Oxcarbazepine has fewer CYP interactions; gabapentinoids less effective for classic TN pain |
| Focal Epilepsy | Lamotrigine; Phenytoin | Lamotrigine has better cognitive profile; phenytoin has different side‑effect set |
| Women of childbearing potential | Lamotrigine preferred when possible; valproate avoided if alternatives exist | Valproate has high teratogenic risk; specialist review required |
Choice on the NHS is stratified by sex, pregnancy potential, comorbidity and concomitant medicines, and specialist review is common when switching between agents.
Frequently asked questions
Can I drive on Tegretol?
Avoid driving while experiencing dizziness or impaired consciousness.
Notify the DVLA and your insurer if you have a seizure or persistent side‑effects that affect alertness.
Is carbamazepine safe in pregnancy?
Carbamazepine carries teratogenic risk and should be reviewed with a specialist before conception.
What if I miss a dose?
Take as soon as you remember unless it is near the next dose; do not double up.
Can I stop suddenly?
No; withdrawal should be gradual under medical supervision to avoid seizure recurrence.
Will the pharmacy switch brands?
For epilepsy, the MHRA advises keeping patients on the same manufacturer’s product, so prescriptions usually specify the brand or manufacturer; ask your prescriber or pharmacist if your tablets look different.
Guidelines for proper use
What should pharmacists tell patients at the first dispense?
- Explain the indication and dosing schedule clearly, including how to take Retard versus immediate‑release tablets.
- Warn about early side‑effects such as dizziness and drowsiness, and instruct to report any rash immediately.
- Advise on contraception reliability and the need for additional methods while taking carbamazepine.
- Arrange baseline blood tests (FBC, LFTs, sodium) and a monitoring schedule with the GP or specialist.
Provide written information and confirm understanding at the first supply, using NHS repeat dispensing or electronic messaging to remind patients about laboratory follow‑up.
Storage advice: store at room temperature between 15–30°C in the original packaging and avoid splitting sustained‑release tablets.
Delivery across the United Kingdom
| City | Region | Delivery time |
|---|---|---|
| London | Greater London | 9–21 days |
| Birmingham | West Midlands | 9–21 days |
| Manchester | Greater Manchester | 9–21 days |
| Glasgow | Scotland | 9–21 days |
| Liverpool | Merseyside | 9–21 days |
| Leeds | West Yorkshire | 9–21 days |
| Edinburgh | Scotland | 9–21 days |
| Bristol | South West England | 9–21 days |
| Newcastle Upon Tyne | North East England | 9–21 days |
| Sheffield | South Yorkshire | 9–21 days |
| Nottingham | Nottinghamshire | 9–21 days |
| Southampton | Southampton | 9–21 days |
| Cardiff | Wales | 9–21 days |
Final practical notes
Keep a record of the exact brand and batch you receive and report concerns to your pharmacist or prescriber.
Contact the MHRA Yellow Card scheme to report suspected adverse reactions.
When in doubt, ask for pharmacist counselling and request a follow‑up appointment with the GP or specialist for monitoring and dose review.



