
Trazodone
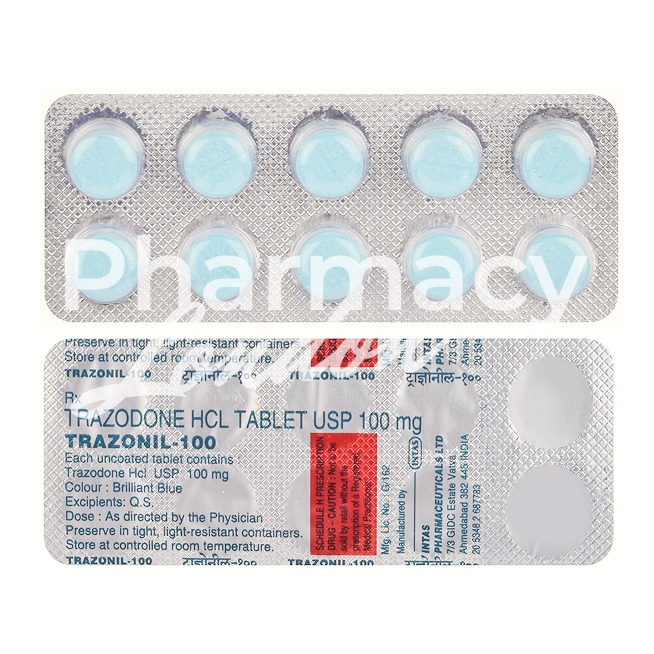
In brief
- In our pharmacy, you can buy trazodone without a prescription, with delivery in 9–21 days throughout the United Kingdom; discreet and anonymous packaging. (Note: trazodone is a prescription-only medicine in the UK — consult a healthcare professional.)
- Trazodone is used mainly to treat major depressive disorder and is often used off-label for insomnia; its mechanism includes serotonin reuptake inhibition and antagonism of 5‑HT2 receptors.
- Usual doses: for depression 150 mg/day initially (can be increased to 300 mg/day; hospital inpatients up to 600 mg/day); for insomnia commonly 25–100 mg at bedtime, individualised per patient.
- Administered orally as capsules (50 mg, 100 mg), tablets (150 mg) or oral solution.
- Onset: sedative effects often begin within 30–60 minutes; antidepressant benefit typically takes 2–4 weeks of treatment to become apparent.
- Duration of action: sedative effects usually last several hours (commonly ~6–8 hours); antidepressant effects require continuous dosing.
- Alcohol warning: avoid alcohol — concurrent use increases sedation, risk of respiratory depression and other CNS effects.
- The most common side effect is sedation/drowsiness (other frequent effects include dizziness, dry mouth, nausea and orthostatic hypotension).
- Would you like to try trazodone without a prescription?
Basic trazodone information
- INN (international nonproprietary name): Trazodone
- Brand names available in the United Kingdom: generic trazodone products
- ATC code: N06AX05
- Forms and strengths: capsules 50 mg and 100 mg; tablets 150 mg; oral solution
- Manufacturers in the United Kingdom: various generic manufacturers (e.g. Mylan)
- Registration status in the United Kingdom: Prescription-only medicine (POM)
- OTC / Rx classification: Prescription only (Rx)
Legal status and availability in the UK
In our online pharmacy, trazodone is available without a prescription, with discreet delivery to the United Kingdom in 9–21 days.
Clinical effectiveness in the UK
Will trazodone work for patients treated in NHS services?
Trazodone is effective for moderate–severe depression at antidepressant doses, typically 150–300 mg/day titrated as needed.
Clinical experience indicates an early improvement in sleep and sometimes a subjective early lift in mood compared with some SSRIs.
Patients do report higher early sedation and dizziness rates than with many SSRIs.
Outcome measures checklist
- PHQ‑9 for mood‑severity tracking.
- Sleep diary to capture sleep latency and continuity.
- Blood pressure checks for orthostatic changes at baseline and early review.
Onset of benefit — quick comparison
| Outcome | Typical onset with trazodone | Typical onset with SSRIs |
|---|---|---|
| Sleep onset | Within nights to 1 week at 25–100 mg at bedtime | Variable; often slower, may rely on sedating side effects |
| Mood improvement | 2–4 weeks at antidepressant doses (150–300 mg/day) | 2–6 weeks depending on agent |
Monitoring and safety reminders for UK clinicians include baseline blood pressure, review for orthostatic symptoms at 2–4 weeks, and serum sodium checks in older adults because of SIADH risk.
Report suspected adverse drug reactions such as hyponatraemia, arrhythmias or priapism via the MHRA Yellow Card scheme.
Indications and expanded uses
What is trazodone officially for, and what do GPs and psychiatrists actually prescribe it for?
In the UK, trazodone is licensed for depressive illness (including depression accompanied by anxiety) and for anxiety.
Off‑label uses commonly seen in UK primary care and private psychiatry include insomnia (low nocturnal doses 25–100 mg) and adjunctive use for treatment‑resistant depression.
Approved uses
- Depressive illness, including depression accompanied by anxiety.
- Anxiety.
Off‑label uses
- Insomnia — low‑dose nocturnal use 25–100 mg (widespread practice though not universally recommended by all NHS trusts).
- Adjunctive therapy — in specialist settings for treatment‑resistant depression.
Evidence and typical dosing summary
| Indication | Level of evidence | Typical dosing |
|---|---|---|
| Depression | Moderate (licensed; cohort and small RCT data) | 150 mg/day initially, up to 300 mg/day (600 mg/day in hospital inpatients) |
| Insomnia (off‑label) | Low‑to‑moderate (small RCTs for sleep latency) | 25–100 mg at bedtime |
When prescribing off‑label, document shared decision‑making and provide explicit counselling to the patient.
Composition and brand landscape
Which ingredient is active and which brands or generics are commonly seen?
The active ingredient is trazodone hydrochloride (INN: trazodone; ATC N06AX05).
Generics are supplied in the UK by several manufacturers.
| Brand | Manufacturer | Strengths | Formulation |
|---|---|---|---|
| Generic trazodone | Various manufacturers | 50 mg, 100 mg capsules; 150 mg tablets | Capsules, tablets, oral solution |
For dispensing, confirm excipients and whether tablets are scored for safe dose splitting, and check MHRA product licences and local NHS formularies for preferred generics.
Contraindications and special precautions
Who should not receive trazodone, and who needs extra care?
Absolute contraindications include known hypersensitivity to trazodone, recent myocardial infarction, and acute intoxication with alcohol or other CNS depressants.
Special precautions apply in cardiac disease because of arrhythmia and QT prolongation risk, significant hepatic or renal impairment, history of priapism, seizure disorders, bipolar disorder, angle‑closure glaucoma and in the elderly at increased risk of falls.
Pregnancy and breastfeeding data are limited and use should be considered only if benefits outweigh risks after specialist discussion.
- Do not prescribe if: known hypersensitivity; recent myocardial infarction; current acute CNS depressant intoxication.
- Caution/monitor: cardiac disease, hepatic/renal impairment, history of priapism, seizure history, bipolar disorder, elderly at fall risk.
Advise patients not to drive or operate machinery until they know how trazodone affects them, and to avoid alcohol.
Dosage guidelines
How should trazodone be dosed and adjusted in everyday NHS practice?
Standard adult antidepressant dosing starts at 150 mg/day in divided doses (or as a single dose at bedtime) and is titrated according to response up to 300 mg/day; hospital inpatients may receive up to 600 mg/day.
For insomnia, low nocturnal off‑label doses of 25–100 mg at bedtime are commonly used.
Elderly patients should start low, for example 50 mg at night for insomnia, with slow titration and orthostatic monitoring.
| Group / indication | Starting dose | Titration / max notes |
|---|---|---|
| Adult depression | 150 mg/day | Increase to 300 mg/day if needed; hospital inpatients up to 600 mg/day |
| Insomnia (off‑label) | 25–100 mg at bedtime | Individualised; document shared decision‑making |
| Elderly | Start low (often 50 mg at night) | Slow titration; monitor BP and falls risk |
| Hepatic/renal impairment | Lower initial dose | Extend titration intervals to avoid accumulation |
When discontinuing, taper gradually to lower withdrawal risk and document the plan in the medical record.
Interactions overview
Which medicines and substances create risk with trazodone?
Do not use trazodone with MAO inhibitors because of serotonin syndrome risk.
Combined use with other serotonergic agents such as SSRIs, SNRIs or triptans increases serotonin syndrome risk and should prompt careful review.
Concomitant CNS depressants including benzodiazepines, opioids and alcohol increase sedation and respiratory depression risk.
QT‑prolonging medicines and some antiarrhythmics warrant ECG monitoring when combined with trazodone.
| Interaction | Clinical action |
|---|---|
| MAO inhibitors | Avoid; risk of serotonin syndrome |
| SSRIs / SNRIs / Triptans | Use caution; monitor for serotonin syndrome |
| Benzodiazepines / Opioids / Alcohol | Monitor for increased sedation; avoid alcohol |
| QT‑prolonging drugs | Consider ECG monitoring; use caution |
Reported adverse reactions include hyponatraemia, arrhythmias and priapism; clinicians should report suspected adverse reactions via the Yellow Card scheme.
Comparable medicines and prescribing preferences
What are common NHS alternatives when trazodone is unsuitable?
Common alternatives include SSRIs such as sertraline, escitalopram and fluoxetine for primary depression, mirtazapine for depression with marked insomnia, and amitriptyline for neuropathic pain and sleep at low doses.
| Drug | Typical dose | Key advantages | Key risks |
|---|---|---|---|
| Trazodone | 150–300 mg/day (depression); 25–100 mg at night (insomnia) | Sedating; less sexual dysfunction vs SSRIs | Orthostatic hypotension; rare priapism |
| Sertraline (SSRI) | 50–200 mg/day | Well‑evidenced for depression and anxiety | Sexual dysfunction; GI side effects |
| Mirtazapine | 15–45 mg at night | Good for insomnia and appetite; effective antidepressant | Weight gain; daytime sedation |
Use local formularies and patient preference to guide choice and consider comorbidities such as cardiac disease or seizure risk when selecting therapy.
FAQ
Will trazodone help my sleep?
Low nightly doses of 25–100 mg commonly improve sleep onset, but this is off‑label and should be discussed with your GP or pharmacist.
Is trazodone safe long‑term?
For depression, treatment usually continues for at least six months after remission but requires periodic review for side effects including hyponatraemia and falls risk.
Can I drink alcohol while taking it?
Avoid alcohol while taking trazodone because it increases sedation, dizziness and respiratory depression risk.
What if I miss a dose?
Take it as soon as you remember unless it is almost time for the next dose; do not double up.
- When to call NHS 111 or your GP: severe dizziness or fainting; an erection lasting longer than 4 hours (priapism); signs of serotonin syndrome (high temperature, agitation, rapid heart rate, tremor).
Guidelines for proper use
What should a pharmacist cover when handing out trazodone?
Explain the indication clearly (depression versus low‑dose sleep use) and set expectations about timelines: sleep benefit may appear quickly while mood benefit takes weeks.
Advise on orthostatic precautions, avoidance of alcohol and not driving until effects are known.
Review other medicines for interactions, confirm absence of recent myocardial infarction or priapism history, and document counselling in pharmacy records.
Tapering and monitoring
Taper the dose gradually under GP supervision to avoid withdrawal symptoms and prepare a written taper schedule for the patient where appropriate.
Monitoring recommendations include baseline blood pressure, review at 2–4 weeks, serum sodium check for older adults if clinically indicated, and ECG if there is cardiac risk.
Signpost patients to NHS 111, local GP portals and mental‑health crisis lines for escalation, and ensure follow‑up arrangements before repeat supply.
Delivery across the United Kingdom
| City | Region | Delivery Time |
|---|---|---|
| London | England | 9–21 days |
| Birmingham | England | 9–21 days |
| Glasgow | Scotland | 9–21 days |
| Manchester | England | 9–21 days |
| Leeds | England | 9–21 days |
| Liverpool | England | 9–21 days |
| Bristol | England | 9–21 days |
| Newcastle Upon Tyne | England | 9–21 days |
| Sheffield | England | 9–21 days |
| Edinburgh | Scotland | 9–21 days |
| Cardiff | Wales | 9–21 days |
| Belfast | Northern Ireland | 9–21 days |
| Leicester | England | 9–21 days |



