
Cabergoline
In brief
- Cabergoline is a prescription-only medicine (POM) in the UK.
- Cabergoline is used to treat hyperprolactinaemic disorders (for example prolactinomas and other causes of high prolactin) and as an adjunct in Parkinson’s disease; it is a dopamine D2 receptor agonist that reduces pituitary prolactin secretion.
- Usual dosing for hyperprolactinaemia starts at 0.25 mg twice weekly, titrating by 0.25 mg (two doses per week) every 4 weeks to a typical maintenance dose of up to 1–2 mg per week (rare cases up to 4.5 mg/week); for Parkinson’s adjunctive use doses often start around 0.5 mg daily with slow titration.
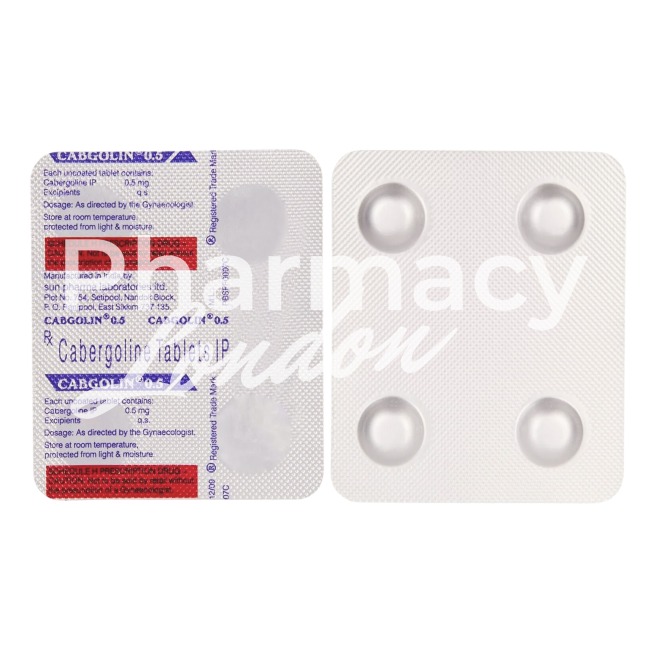
- The drug is given orally as tablets (common strengths 0.25 mg, 0.5 mg and 1 mg) in blister or strip packs.
- Prolactin levels often begin to fall within 24–72 hours of the first dose, though symptomatic and tumour-size responses may take several weeks.
- Cabergoline has a long duration of action (long half-life, typically measured in days — often around 60–70 hours), permitting twice-weekly or weekly dosing in many patients.
- Alcohol should be avoided or minimised while taking cabergoline because it can worsen dizziness, sedation and orthostatic hypotension.
- The most common side effect is nausea; other frequently reported effects include headache, dizziness, constipation, fatigue and orthostatic hypotension.
- Would you like to try cabergoline without a prescription?
Basic cabergoline information
- INN (international nonproprietary name): Cabergoline
- Brand names available in the United Kingdom: Dostinex, Cabaser and generic cabergoline
- ATC code: G02CB03 (genito-urinary system and sex hormones → other gynaecologicals → prolactin inhibitors)
- Forms and strengths: tablet 0.25 mg, 0.5 mg, 1 mg (blister or strip packs, typical pack sizes 2–8)
- Manufacturers: various generic manufacturers (for example Teva, Sandoz, Aurobindo)
- Registration status in the United Kingdom: prescription-only medicine
- OTC / Rx classification: Prescription only (Rx)
Legal status and availability in the UK
In our online pharmacy, cabergoline is available without a prescription, with discreet delivery to the United Kingdom in 9‑21 days.
Clinical effectiveness in the UK
How quickly will symptoms improve on cabergoline?
Symptoms commonly improve within weeks to months of starting cabergoline.
Common clinical improvements include resumption of menses, improved fertility indices, and reduced galactorrhoea.
Imaging follow‑up commonly shows microadenoma shrinkage after treatment initiation.
Compared with bromocriptine, cabergoline needs less frequent dosing and is better tolerated, which means fewer early treatment discontinuations.
- Typical outcomes: return of regular menses, improved libido, fewer headaches, reduced nipple discharge.
- Fertility outcomes: improved menstrual regularity and improved chances of conception when prolactin normalises.
Definitions useful for patients
- Biochemical response: Prolactin measured in the blood returning to normal reference range.
- Radiological response: Reduction in tumour size on MRI or CT imaging.
- Quality‑of‑life indicators: Symptom relief such as restored fertility, reduced galactorrhoea and improved energy.
Indications and expanded uses — MHRA‑approved versus off‑label
What is cabergoline officially for, and when might it be used beyond those indications?
The primary MHRA‑approved indication is hyperprolactinaemia, including prolactinomas and related pituitary adenomas.
Adjunctive use in Parkinson’s disease remains a specialist option at higher doses, usually under neurology care rather than routine endocrine prescribing.
Occasional off‑label use for other endocrine disturbances requires high evidence thresholds and specialist oversight.
| MHRA‑approved indications | Common off‑label uses |
|---|---|
| Hyperprolactinaemia (prolactinomas, pituitary adenomas) | Selected endocrine disorders under specialist care (case‑by‑case) |
| Adjunct in Parkinson’s disease (specialist neurology dosing) | Rare experimental uses in tertiary centres with informed consent |
Checklist for clinicians and patients before off‑label use
- Confirm lack of established alternatives and document rationale.
- Obtain explicit informed consent explaining known benefits and risks.
- Agree monitoring plan and escalation routes with the patient.
Composition and brand landscape — UK availability and generics
Which strengths and brands should patients expect, and will their tablets look different?
Cabergoline tablets are commonly available in 0.25 mg, 0.5 mg and 1 mg strengths.
Generic cabergoline is made by several manufacturers, including Sun Pharmaceuticals, Cipla, Teva, Aurobindo and Sandoz among others.
Brand names include Dostinex and Cabaser.
Tablet appearance may vary between suppliers.
| Brand name | Notes |
|---|---|
| Dostinex | Used for hyperprolactinaemia |
| Cabaser | Used for Parkinson’s adjunct therapy |
| Generic cabergoline | Manufacturers include Teva, Sandoz, Aurobindo, Sun Pharma, Cipla |
Pill appearance counselling tip: explain to patients that tablets may vary in colour, shape or markings between manufacturers, and advise checking pack leaflets and consulting the dispensing pharmacist if uncertain.
Contraindications and special precautions — who needs caution?
Who must not take cabergoline and what checks are needed before starting?
Absolute contraindications include known hypersensitivity to cabergoline or other ergot derivatives, uncontrolled hypertension, a history of fibrotic disorders (for example pulmonary or cardiac valvular fibrosis), and pregnancy unless benefits clearly outweigh risks.
Relative contraindications warrant careful assessment and monitoring; these include existing cardiac or valvular disorders, severe renal or hepatic impairment, and a history of psychiatric illness.
Regulatory guidance recommends echocardiography for patients expected to receive long‑term or high‑dose therapy because of the possible valvular risk with prolonged exposure.
Absolute versus relative contraindications
- Absolute: Condition where cabergoline should not be used (hypersensitivity, uncontrolled hypertension, known fibrotic disease, pregnancy unless essential).
- Relative: Conditions requiring extra caution and monitoring (cardiac disease, renal/hepatic impairment, psychiatric history).
Pre‑treatment assessment checklist for patients
- Baseline blood pressure measurement.
- Cardiac history and consideration of baseline echocardiogram if prolonged therapy expected.
- Review of psychiatric history and current psychotropic medicines.
- Discussion about pregnancy planning and effective contraception while on therapy unless otherwise advised by the specialist.
Dosage guidelines — regimens and adjustments
How is cabergoline started and adjusted in routine NHS practice?
Standard starting regimens for hyperprolactinaemia are low‑frequency dosing, commonly 0.25 mg twice weekly with stepwise titration every four weeks as needed to normalise prolactin.
Maintenance doses typically range up to 1–2 mg per week, with rare resistant cases requiring higher totals up to 4.5 mg per week in specialist centres.
Parkinson’s adjunct dosing starts higher (for example 0.5 mg daily) and is titrated slowly by neurology specialists.
Elderly patients are usually started at lower doses and titrated cautiously to reduce the risk of orthostatic hypotension and psychiatric adverse events.
Renal impairment rarely requires routine dose change except in severe disease, while hepatic impairment prompts caution because cabergoline undergoes hepatic metabolism.
Stepwise initiation and titration
- Start 0.25 mg twice weekly for hyperprolactinaemia.
- Recheck prolactin after 4–8 weeks and increase by 0.25 mg twice weekly if required.
- Aim for biochemical normalisation before deciding on long‑term maintenance dose.
Monitoring frequency
- Clinical and biochemical review typically every 3–6 months in NHS shared‑care pathways.
- Elderly patients: more cautious and frequent review for hypotension and psychiatric symptoms.
Interactions overview — drugs and food
Which medicines or habits should patients flag to the pharmacist?
Pharmacodynamic interactions include additive hypotension with antihypertensives and altered dopaminergic effects when combined with antipsychotics or other central dopamine‑active drugs.
Caution is also needed with psychotropic medicines, and orthostatic events are more likely when alcohol is consumed or with concurrent hypotensive drugs.
There are no major food interactions specified, though alcohol may increase dizziness or sedation.
High‑risk drug classes
- Antihypertensives (increased risk of symptomatic hypotension).
- Antipsychotics and other dopamine antagonists (may reduce cabergoline efficacy or lead to complex interactions).
- Other dopaminergic agents used for Parkinson’s disease (specialist co‑management required).
| Concomitant medicine | Possible effect |
|---|---|
| Beta‑blockers / ACE inhibitors | Enhanced orthostatic hypotension risk |
| Antipsychotics | Potential antagonism or psychiatric stability concerns |
| Alcohol | May worsen dizziness, sedation and orthostatic symptoms |
Patient checklist for everyday precautions
- Tell your pharmacist about all prescribed and over‑the‑counter medicines.
- Avoid sudden standing and rise slowly if feeling lightheaded.
- Limit alcohol while starting or increasing dose.
Comparable medicines and preferences — bromocriptine, quinagolide
Should a clinician pick cabergoline or an alternative dopamine agonist?
Bromocriptine and quinagolide are viable alternatives for hyperprolactinaemia, but cabergoline is frequently preferred for many patients because of its longer half‑life, less frequent dosing and superior gastrointestinal tolerability.
Choice for Parkinson’s disease is different and usually depends on specialist neurology assessment, as dopaminergic profiles and target doses vary.
Pros and cons
- Cabergoline: longer half‑life, twice‑weekly dosing for hyperprolactinaemia, better GI tolerability for many patients.
- Bromocriptine: daily dosing, more GI side effects reported, sometimes used where cabergoline contraindicated.
- Quinagolide: non‑ergot alternative with once‑daily dosing.
Decision aid for clinicians and patients
- Consider patient tolerance of GI side effects and preferred dosing frequency.
- Review contraindications such as fibrotic disease and cardiac history.
- Follow local formulary preferences when selecting a generic or branded option.
Frequently asked questions
How soon will prolactin fall and can I get pregnant on cabergoline?
-
How long until prolactin levels normalise?
Biochemical normalisation commonly takes weeks to a few months, with checks typically at 4–8 weeks after initiation and then periodically.
-
Will cabergoline help with fertility?
Yes, many patients experience return of menses and improved fertility indices once prolactin normalises, although individual outcomes vary.
-
What are the long‑term safety checks?
Routine clinical and biochemical monitoring every 3–6 months is standard practice, with echocardiography reserved for prolonged or high‑dose therapy.
-
How do I report side effects?
Report suspected adverse reactions via the MHRA Yellow Card scheme and contact your GP or endocrine clinic for urgent concerns.
Definitions of technical terms
- Prolactin: A hormone produced by the pituitary gland that can affect menstrual cycles and lactation.
- Microadenoma: A pituitary tumour smaller than 10 mm.
Guidelines for proper use — pharmacist counselling and NHS portal tips
What should the pharmacist tell a patient when dispensing cabergoline?
Best practice is clear counselling on the dosing schedule, side‑effect management and a monitoring plan agreed with the prescriber.
Pharmacists should reconcile medications using the Summary Care Record, check for interacting drugs and advise on practical matters such as missed doses and driving.
Pharmacist counselling checklist
- Explain twice‑weekly dosing schedules and what to do if a dose is missed.
- Advise about orthostatic hypotension and rising slowly from sitting or lying positions.
- Discuss alcohol moderation especially while starting or increasing dose.
- Flag psychiatric symptoms (e.g. low mood, hallucinations) and give clear escalation routes.
- Encourage Yellow Card reporting for suspected adverse drug reactions.
| Follow‑up | Typical timeline |
|---|---|
| Blood pressure check | At baseline and during dose increases or if symptomatic |
| Prolactin level | 4–8 weeks after start, then every 3–6 months |
| Echocardiogram | Consider if long‑term or high‑dose therapy expected |
Patients should be signposted to NHS portals for local endocrine clinic contact details and for validated written information on the medicine.
Delivery across the United Kingdom
| City | Region | Delivery Time |
|---|---|---|
| London | Greater London | 9–21 days |
| Birmingham | West Midlands | 9–21 days |
| Manchester | Greater Manchester | 9–21 days |
| Glasgow | Scotland | 9–21 days |
| Leeds | West Yorkshire | 9–21 days |
| Liverpool | Merseyside | 9–21 days |
| Edinburgh | Scotland | 9–21 days |
| Bristol | South West England | 9–21 days |
| Sheffield | South Yorkshire | 9–21 days |
| Newcastle Upon Tyne | North East England | 9–21 days |
| Nottingham | Nottinghamshire | 9–21 days |
| Leicester | Leicestershire | 9–21 days |
| Plymouth | South West England | 9–21 days |
| Swansea | Wales | 9–21 days |



