
Clopidogrel
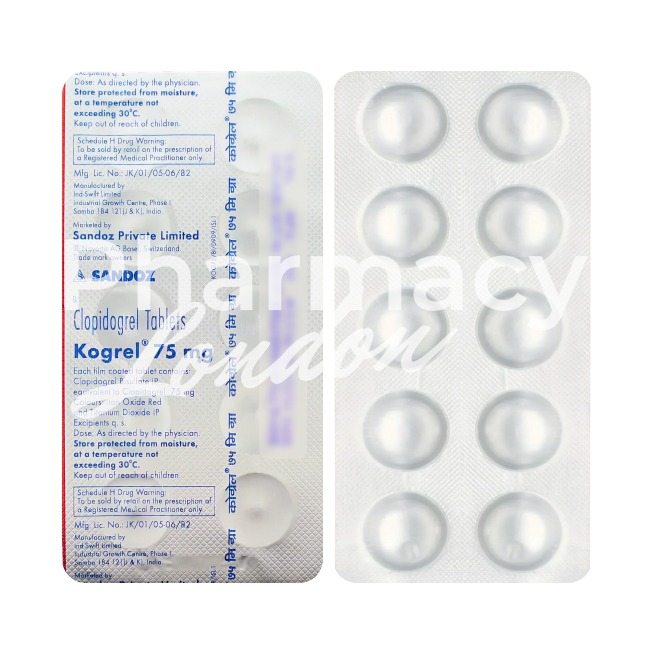
In brief
- In our pharmacy, you can buy clopidogrel without a prescription, with delivery in 9–21 days throughout the United Kingdom. Discreet and anonymous packaging.
- Clopidogrel is used to prevent blood clots in acute coronary syndromes, after percutaneous coronary intervention (stenting), and for secondary prevention of stroke, myocardial infarction and peripheral arterial disease; it is a thienopyridine antiplatelet prodrug that, after hepatic activation, irreversibly blocks the P2Y12 ADP receptor on platelets to reduce platelet aggregation.
- The usual dosage is a maintenance dose of 75 mg once daily; for acute coronary syndromes or before/after PCI a loading dose of 300–600 mg once may be given, followed by 75 mg daily.
- The form of administration is oral tablets (film‑coated) — commonly 75 mg for maintenance and 300 mg for loading.
- The effect begins within about 2 hours after a loading dose; with no loading dose, antiplatelet effects develop more slowly over 3–7 days as steady state is reached.
- The duration of action reflects irreversible platelet inhibition for the lifespan of affected platelets — typically around 7–10 days; clinically significant antiplatelet effect diminishes over about 5–7 days after stopping.
- Avoid excessive alcohol while taking clopidogrel — alcohol can increase the risk of gastrointestinal bleeding and bruising, so drink with caution and discuss alcohol use with a clinician if you are at bleeding risk.
- The most common side effects are bruising and minor bleeding (nosebleeds, bleeding gums), diarrhoea, abdominal pain and dyspepsia; less common are rash, headache and dizziness; serious but rare reactions include gastrointestinal or intracranial haemorrhage, neutropenia and thrombotic thrombocytopenic purpura.
- Would you like to try clopidogrel without a prescription?
Basic clopidogrel information
- INN (international nonproprietary name): Clopidogrel.
- Brand names available in the United Kingdom: Plavix; generic clopidogrel (e.g. Teva, Mylan, Krka).
- ATC code: B01AC04 — Antithrombotic agents, platelet aggregation inhibitors excluding heparin.
- Forms and strengths: tablets 75 mg (maintenance) and 300 mg (loading dose) are the primary strengths.
- Manufacturers in the United Kingdom: Sanofi (Plavix) and generic manufacturers.
- Registration status in the United Kingdom: not specified.
- OTC / Rx classification: Prescription-only medicine (Rx).
Legal status and availability in the UK
Our online pharmacy offers discreet delivery across the United Kingdom and can dispatch prescription medicines with appropriate validation and secure packaging.
Clinical effectiveness in the UK
Patients commonly ask whether clopidogrel actually prevents further strokes and heart attacks.
Clopidogrel is effective for secondary prevention of ischaemic stroke, myocardial infarction and for post‑stent antiplatelet therapy when used in line with guidance.
In routine practice, the 75 mg once‑daily maintenance regimen, with a 300–600 mg loading dose for ACS/PCI where indicated, achieves meaningful reductions in recurrent events compared with aspirin monotherapy for many patients.
Absolute benefits depend on baseline vascular risk, so individualised assessment remains essential.
Bruising, minor bleeding and gastrointestinal upset are frequent complaints.
Those adverse effects are common causes of reduced adherence in primary care settings unless actively managed.
Adherence to clopidogrel can decline over several months without pharmacist reinforcement; repeat dispensing and community pharmacist follow‑ups can help.
When counselling, pharmacists should proactively address side effects and practical barriers to adherence.
Indications and expanded uses — MHRA‑approved and off‑label practice
Patients often ask what clopidogrel is licensed for and when clinicians might use it differently.
Clopidogrel is licensed primarily for acute coronary syndromes and percutaneous coronary intervention, secondary prevention of ischaemic stroke and treatment in peripheral arterial disease.
Typical protocols use a loading dose of 300–600 mg for ACS/PCI followed by 75 mg once daily maintenance.
Long‑term therapy is common after stent placement for at least 12 months depending on stent type and bleeding risk.
Some UK specialist centres undertake off‑label or tailored strategies such as combination regimens for complex peripheral vascular disease and short‑term dual antiplatelet therapy de‑escalation guided by bleeding risk.
Clopidogrel is not approved for paediatric use and is generally avoided in pregnancy unless advised by specialist obstetric cardiology due to bleeding concerns.
Clinicians and pharmacists should use a simple checklist to decide: indication present, bleeding risk assessed, interaction review complete, and plan for duration documented.
Documentation that the prescription is for a licensed indication or a justified specialist decision helps with governance and patient safety.
Composition and brand landscape — active ingredient, generics, UK brands
Patients worry when their branded Plavix is substituted for a generic; pharmacists need to reassure them about formulation equivalence.
The active ingredient is clopidogrel (INN) and the ATC code is B01AC04.
The original brand is Plavix (Sanofi); generic clopidogrel tablets from several manufacturers are widely used in the UK.
Standard forms sold are 75 mg tablets with 300 mg available for loading doses in some product lines.
Packaging varies by supplier, and some generics appear in NHS prescribing systems under different supplier names, which can cause patient confusion.
Pharmacists should explain that generics meet regulatory bioequivalence standards and that substitution is routine to manage supply.
Remind patients that the INN clopidogrel identifies the active medicine regardless of brand.
Contraindications and special precautions — high‑risk groups and daily life restrictions
People often ask which conditions mean clopidogrel is unsafe for them.
Absolute contraindications are active pathological bleeding such as peptic ulceration or intracranial haemorrhage, and known hypersensitivity to clopidogrel or any excipient.
Use caution in patients with bleeding disorders, recent major surgery, severe liver impairment and those on concomitant anticoagulation because of additive bleeding risk.
Elderly patients do not require formal dose reduction but need closer monitoring for bleeding complications.
Pregnancy and breastfeeding need specialist risk assessment and are generally avoided unless managed by specialist teams.
Give clear lifestyle advice: avoid high‑risk activities if bruising or bleeding occurs, and seek medical help for serious nosebleeds or prolonged bleeding.
Driving and DVLA guidance should be discussed if side effects such as dizziness, syncope or visual disturbance occur.
Alcohol can increase bleeding risk so advise patients to avoid binge drinking and discuss regular intake during consultations.
Dosage guidelines — NHS‑recommended regimens and adjustments
Patients ask how much clopidogrel to take and what to do if a dose is missed.
NHS standard dosing is 75 mg once daily for maintenance, with a 300–600 mg loading dose for ACS/PCI where indicated.
Typical duration is at least 12 months after stenting, tailored by stent type and bleeding risk, and indefinite for secondary prevention of stroke or PAD when appropriate.
No routine dose adjustment is required for mild to moderate renal impairment, but use caution in severe renal disease and monitor for bleeding.
Hepatic impairment warrants cautious use as severe liver disease increases the risk of bleeding.
Children are not approved to take clopidogrel.
If a dose is missed the patient should take it as soon as remembered unless it is almost time for the next dose, and they must not double up.
In overdose there is no specific antidote and management is supportive; platelet transfusion may be considered in severe bleeding.
Interactions overview — drugs and food
Many patients want to know which drugs reduce clopidogrel’s effect or raise bleeding risk.
Clopidogrel is a prodrug requiring CYP metabolism, with CYP2C19 playing a prominent role in activation.
CYP2C19 inhibitors, including some proton‑pump inhibitors, can reduce clopidogrel activation and hence its antiplatelet effect.
Concomitant anticoagulants, SSRIs/SNRIs, NSAIDs and other antiplatelets increase bleeding risk and require careful review at dispensing.
Alcohol can potentiate bleeding; herbal supplements such as St John’s Wort may alter metabolism and should be discussed.
Suspected bleeding events and hypersensitivity reactions should be reported via the MHRA Yellow Card scheme.
Consider CYP2C19 genotyping in high‑risk patients where local cardiac pathways recommend it to predict reduced response to clopidogrel.
When counselling, pharmacists should provide a brief interactions checklist and advise patients to tell any clinician they are taking clopidogrel tablets.
Comparable medicines and prescribing preferences — NHS alternatives
Many patients want to know if a stronger antiplatelet would be better than clopidogrel.
Common alternatives on NHS formularies include ticagrelor (Brilique) and prasugrel (Efient) for higher‑risk ACS patients, while aspirin remains a frequently used comparator for single‑agent prevention.
Ticagrelor and prasugrel generally offer greater and more consistent platelet inhibition than clopidogrel, and some trials show reduced ischaemic events, but they also increase bleeding and have different side‑effect profiles such as dyspnoea with ticagrelor.
NHS cardiology teams increasingly use risk‑stratified pathways: potent agents for early high‑risk ACS, then consider de‑escalation to clopidogrel for maintenance in lower‑risk or bleeding‑prone patients.
Pharmacists can support prescribers by summarising pros and cons for patients: efficacy trade‑off, bleeding risk, side effects and supply considerations.
Where appropriate, document the rationale for selecting clopidogrel versus ticagrelor or prasugrel and ensure the patient understands duration and follow‑up.
FAQ — common NHS patient questions
Can I stop clopidogrel if I bruise?
No; patients should not stop clopidogrel without consulting their GP or pharmacist because minor bruising is common but severe bleeding requires urgent attention.
Is clopidogrel safe with my PPI?
Some proton‑pump inhibitors can reduce activation by CYP2C19; discuss options such as pantoprazole or the timing and choice of PPI with your prescriber, and consider genotype testing where recommended.
Can I drink alcohol?
Moderate alcohol can increase bleeding risk; avoid binge drinking and seek advice if there is a history of peptic ulcer disease or liver disease.
What if I miss a dose?
Take the dose as soon as remembered unless it is almost time for the next dose; do not double up.
Emergency signs: prolonged bleeding, large‑area bruising, sudden severe headache or vomiting blood — contact NHS 111, your GP or attend A&E depending on severity.
Guidelines for proper use — pharmacist counselling and NHS support tools
Patients often want a short checklist of what the pharmacist will tell them when starting clopidogrel.
Counselling should cover why clopidogrel is prescribed, the dosing schedule (75 mg daily; 300–600 mg loading dose for ACS/PCI), expected benefits and common side effects such as bruising and gastrointestinal upset.
Use teach‑back to confirm understanding and offer practical adherence aids such as dosette boxes, NHS repeat dispensing or electronic prescription notifications through the NHS App.
Flag potential interactions in the summary care record and advise patients on peri‑operative planning: do not stop clopidogrel before dental or surgical procedures without clinician advice.
Provide written patient information and safety netting that lists signs of serious bleeding and clear NHS contact points.
Where available, refer patients to local Medicines Use Reviews or community pharmacy follow‑ups to reinforce adherence and manage side effects.
Delivery across the United Kingdom
| City | Region | Delivery Time |
|---|---|---|
| London | Greater London | 9–21 days |
| Birmingham | West Midlands | 9–21 days |
| Manchester | Greater Manchester | 9–21 days |
| Glasgow | Scotland | 9–21 days |
| Leeds | West Yorkshire | 9–21 days |
| Liverpool | Merseyside | 9–21 days |
| Bristol | South West England | 9–21 days |
| Edinburgh | Scotland | 9–21 days |
| Newcastle Upon Tyne | North East England | 9–21 days |
| Sheffield | South Yorkshire | 9–21 days |
| Cardiff | Wales | 9–21 days |
| Belfast | Northern Ireland | 9–21 days |
| Plymouth | South West England | 9–21 days |



