
Dostinex
In brief
- In our pharmacy, you can buy Dostinex without a prescription, with delivery in 9–21 days throughout the United Kingdom. Discreet and anonymous packaging.
- Dostinex (cabergoline) is used to treat hyperprolactinaemia and prolactin-secreting pituitary adenomas, and to manage menstrual and fertility disorders related to high prolactin; it is a dopamine D2 receptor agonist that inhibits prolactin secretion from the pituitary gland.
- The usual dose is 0.5 mg per week to start (single or divided dose), titrated by 0.5 mg/week as needed; common maintenance dosing is up to 1 mg twice weekly, with typical maximum around 2 mg/week (higher doses used in some cases under supervision).
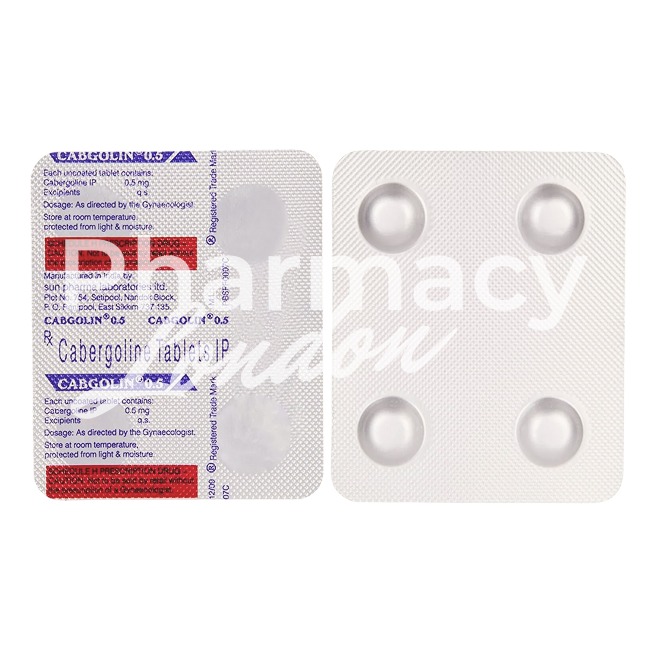
- The form of administration is oral tablet, commonly 0.5 mg (also available as 0.25 mg or 1 mg in some generics), supplied in bottles or blister packs.
- The effect on plasma levels begins within 1–4 hours (Tmax); biochemical reduction in prolactin is often seen within 2–3 days after starting treatment.
- The duration of action is prolonged (half-life ≈ 60–70 hours), allowing once- or twice-weekly dosing and sustained prolactin suppression over several days to a week.
- Avoid or limit alcohol while taking Dostinex, as alcohol can worsen dizziness, sedation and the risk of orthostatic hypotension.
- The most common side effects are nausea, dizziness and headache (other effects include fatigue, constipation, abdominal pain, orthostatic hypotension and, less commonly, psychiatric symptoms).
- Would you like to try Dostinex without a prescription?
Basic Dostinex information
- INN (international nonproprietary name): Cabergoline
- Brand names available in the United Kingdom: Dostinex; Cabaser; generics labelled as cabergoline
- ATC code: G02CB03
- Forms and strengths: tablet (oral) 0.5 mg in bottles or blister packs (common pack sizes 2, 8 or 30 tablets); some generics are available in other strengths
- Manufacturers in the United Kingdom: Pfizer (Dostinex) and multiple generic manufacturers
- Registration status in the United Kingdom: licensed for prescription use; Rx-only medicine
- OTC / Rx classification: Prescription-only medicine (Rx) in the United Kingdom
Legal status and availability in the UK
In our online pharmacy, Dostinex is available without a prescription, with discreet delivery to the United Kingdom in 9–21 days.
Clinical effectiveness in the United Kingdom
What does cabergoline achieve in routine NHS practice and what problems do patients run into?
Cabergoline achieves biochemical control in the majority of patients treated for hyperprolactinaemia.
Treatment typically starts on a low weekly dose with gradual titration, commonly beginning at 0.5 mg/week and increasing in 0.5 mg/week steps to a usual maintenance up to 2 mg/week.
Restored menstrual regularity, improved fertility and reduced galactorrhoea are commonly seen after several weeks to months of treatment.
Common real‑world challenges include adherence to twice‑weekly or weekly dosing schedules, gastrointestinal side effects causing early discontinuation, and variable access to routine echocardiography for long‑term users.
- Prolactin normalisation rates: the majority achieve normalisation within 6–12 months when adherent to cabergoline.
- Fertility outcomes: ovulation and conception are often restored following prolactin control.
- Discontinuation rates: early discontinuation most often due to nausea or dizziness.
Individualised treatment is recommended, with echocardiographic monitoring when long‑term or higher‑dose therapy is planned.
Indications and expanded uses
People often ask whether cabergoline is approved for their condition and whether other uses are common in the UK.
MHRA‑approved indications for cabergoline cover treatment of hyperprolactinaemia and prolactin‑secreting pituitary adenomas.
Use in Parkinson's disease is seen less often in the UK and involves higher‑strength formulations such as Cabaser.
Clinicians commonly use cabergoline to restore fertility and resolve menstrual disorders caused by high prolactin, under endocrinology or gynaecology supervision.
- Approved uses: treatment of hyperprolactinaemia and prolactin‑secreting pituitary adenomas.
- Other uses: Parkinson's disease (specialist use with higher‑strength formulations such as Cabaser).
Start doses commonly begin at 0.5 mg/week with a maximum for routine hyperprolactinaemia usually around 2 mg/week, and specialist care may use higher doses up to 4.5 mg/week in resistant cases.
The decision to start therapy should always reflect symptom burden and reproductive plans.
Composition and brand landscape
Which brands and pack sizes should patients expect to find at the pharmacy counter?
Active ingredient: cabergoline (INN).
Dostinex (Pfizer) remains a widely known brand in the UK, typically available as 0.5 mg tablets supplied in bottles or blister packs.
Generics labelled as cabergoline are widely available and pack sizes commonly include 2, 8 and 30 tablets.
ATC classification is G02CB03 across product information.
| Brand | Supplier | Common pack sizes | Supply route |
|---|---|---|---|
| Dostinex | Pfizer | 2, 8, 30 tablets | NHS prescription or private prescription |
| Cabaser | Pfizer (specialist formulations) | Varies | Specialist/neurology prescribing |
| Generic cabergoline | Multiple manufacturers | 2, 8, 30 tablets; occasional 0.25 mg or 1 mg | NHS or private supply; generic substitution common |
Pharmacies dispense Dostinex or generic cabergoline on presentation of an NHS or private prescription.
Patients are advised to check MHRA medicines information and local formularies for preferred generic alternatives when availability changes.
Contraindications and special precautions
Who should not take cabergoline, and what screening is needed before starting?
Absolute contraindications include uncontrolled hypertension, known hypersensitivity to cabergoline or ergot derivatives, history of cardiac valvular fibrotic disease and certain peripartum histories such as previous pre‑eclampsia.
Relative contraindications that require specialist liaison and monitoring include significant cardiac, hepatic or renal dysfunction and severe psychiatric disorders.
Pregnancy and breastfeeding require specialist risk‑benefit discussions; lactation is contraindicated while on cabergoline.
- Absolute contraindications: uncontrolled hypertension; hypersensitivity to cabergoline/ergot derivatives; known valvular heart disease; history of pre‑eclampsia in peripartum context.
- Relative contraindications: cardiac, hepatic or renal impairment; severe psychotic disorders; pregnancy only if benefit outweighs risk.
Practical UK notes for prescribers: baseline cardiovascular assessment is recommended where indicated, including ECG and echocardiogram for patients anticipated to need long‑term or high‑dose therapy.
Adverse events suspected in the UK should be reported via the MHRA Yellow Card scheme, and patients should be cautioned about driving or operating machinery until they know how cabergoline affects them.
Dosage guidelines and adjustments
How should cabergoline be dosed safely in everyday NHS practice?
Treatment typically starts at 0.5 mg/week, given as a single weekly dose or divided into twice‑weekly doses, and titrates by 0.5 mg/week increments as needed.
Usual maintenance dosing commonly reaches up to 2 mg/week for hyperprolactinaemia, with higher specialist doses used rarely up to 4.5 mg/week in resistant cases.
Treatment is not recommended in children as dosing is not established, and elderly patients require increased vigilance for adverse events although specific dosing adjustment is not standardised.
Severe hepatic impairment calls for lower starting doses and close monitoring, while renal impairment does not usually require a specific dose change unless severe dysfunction is present.
| Indication | Start dose | Usual maintenance | Maximum |
|---|---|---|---|
| Hyperprolactinaemia | 0.5 mg/week | Up to 2 mg/week | 2 mg/week (specialist up to 4.5 mg/week) |
| Prolactinoma | As above | As above | As above |
- Missed dose: take as soon as remembered unless close to the next dose; do not double doses.
- Overdose advice: seek immediate medical attention for severe nausea, hypotension, confusion or hallucinations; symptomatic treatment advised.
Clear electronic prescribing instructions in NHS systems and patient leaflets help adherence to weekly or twice‑weekly regimens.
Interactions overview
Which medicines and habits increase risks when taking cabergoline?
Cabergoline interacts primarily with other dopaminergic agents and hypotensive medicines, and it may worsen psychiatric effects if given with antipsychotics.
Alcohol and sedatives can accentuate dizziness and orthostatic hypotension, and concurrent use with strong CYP3A4 modifiers should be managed cautiously despite limited definitive interaction data.
High‑risk drug classes include antipsychotics, antihypertensives and strong CYP3A4 inhibitors or inducers, and prescribers should document concomitant medicines in NHS records.
| Drug/class | Interaction | Action |
|---|---|---|
| Antipsychotics | May reduce cabergoline efficacy and worsen psychiatric symptoms | Specialist review and close psychiatric monitoring |
| Antihypertensives | Increased risk of orthostatic hypotension | Monitor blood pressure, advise caution on standing |
| CYP3A4 modifiers | Potentially altered cabergoline exposure | Use caution and monitor clinical response |
Encourage patients to report suspected interactions via the MHRA Yellow Card and for pharmacists to check local interaction checkers before dispensing Dostinex or generic cabergoline tablets.
Comparable medicines and prescribing preferences
What are the options when cabergoline is unsuitable, and why do clinicians usually pick it first?
Bromocriptine and quinagolide are the principal alternatives to cabergoline for hyperprolactinaemia in the UK.
Bromocriptine is an older dopamine agonist that typically requires daily dosing and can be more emetogenic; it has been widely used historically.
Quinagolide (Norprolac) is a non‑ergot option considered when cabergoline and bromocriptine are unsuitable.
- Cabergoline: weekly dosing, high efficacy, generally preferred for convenience and tolerability.
- Bromocriptine: daily dosing, more nausea.
- Quinagolide: non‑ergot alternative used in select cases.
NHS formularies often favour cabergoline for many patients, reserving alternatives for intolerance or contraindications, and the final choice should reflect patient preference and local formulary guidance.
Frequently asked questions
How quickly will cabergoline lower prolactin?
Many patients see biochemical improvements within weeks, while clinical symptom improvement may take several weeks to months.
Can I drive while taking it?
Avoid driving until you know whether cabergoline causes dizziness or syncope for you.
Is it safe in pregnancy?
Discuss with your specialist; cabergoline is usually stopped when pregnancy is confirmed unless there is a compelling reason to continue under endocrine supervision.
What about heart checks?
Long‑term or high‑dose users may require echocardiographic monitoring on specialist advice to assess valvular function.
How long should treatment continue?
Treatment is often continued until prolactin has been normal for at least six months, after which reassessment is usual.
Where can I report side effects?
Report suspected adverse reactions to the MHRA Yellow Card scheme and contact NHS 111 or your GP for urgent concerns.
Guidelines for proper use, pharmacist counselling and NHS support
What should a pharmacist cover when dispensing Dostinex or generic cabergoline?
Confirm indication and prescription type (NHS vs private), check absolute contraindications such as uncontrolled hypertension and known valvular disease, and review current medicines to flag interactions.
Explain starting dose and titration, advise on common side effects including nausea and orthostatic hypotension, and counsel on missed‑dose and overdose instructions.
- Storage: store between 20–25°C; protect from moisture and light.
- Missed dose: take as soon as remembered unless it is close to the next dose; do not double doses.
- Overdose: seek immediate medical attention for severe symptoms such as hypotension, hallucinations or severe vomiting.
Provide a short pharmacist script covering dose, side‑effects, driving warnings and Yellow Card reporting, and document the medicine in NHS records as appropriate.
Direct patients to NHS 111, their GP or local endocrine clinic for problems and encourage use of NHS patient portals for follow‑up queries.
Delivery across the United Kingdom
| City | Region | Delivery Time |
|---|---|---|
| London | England | 9–21 days |
| Birmingham | England | 9–21 days |
| Manchester | England | 9–21 days |
| Leeds | England | 9–21 days |
| Glasgow | Scotland | 9–21 days |
| Liverpool | England | 9–21 days |
| Bristol | England | 9–21 days |
| Newcastle | England | 9–21 days |
| Sheffield | England | 9–21 days |
| Nottingham | England | 9–21 days |
| Brighton | England | 9–21 days |
| Belfast | Northern Ireland | 9–21 days |
| Cardiff | Wales | 9–21 days |
| Southampton | England | 9–21 days |
| Plymouth | England | 9–21 days |



