
Euthyrox
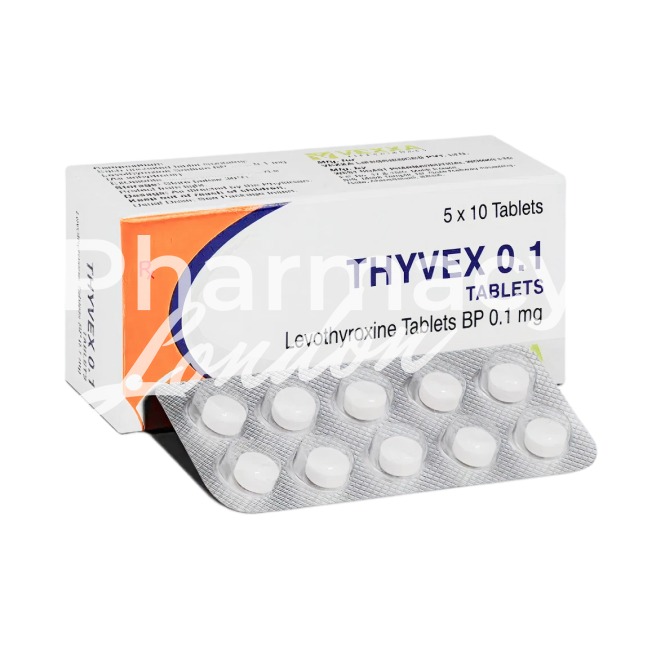
In brief
- Euthyrox is a prescription-only (Rx) medicine in the UK and should be obtained with a valid prescription and medical supervision.
- Euthyrox (levothyroxine sodium) is used to treat hypothyroidism, to provide thyroid hormone replacement and for TSH suppression in some thyroid cancer regimens; it is synthetic thyroxine (T4) which is converted peripherally to active T3 and acts on nuclear thyroid hormone receptors to regulate metabolism and gene expression.
- Usual adult dosing starts at 25–50 mcg once daily and is titrated every 4–6 weeks; full replacement is typically around 1.6 mcg/kg/day once daily; doses are individualised (higher when suppressing TSH in thyroid cancer, lower starting doses for the elderly and children).
- Administered orally as tablets (widely available in multiple strengths, colour‑coded) and as an oral liquid; take once daily on an empty stomach, typically 30–60 minutes before breakfast.
- Biochemical effects begin within days, but patients usually notice symptomatic improvement over 2–6 weeks; TSH and clinical response are normally reassessed every 4–6 weeks when adjusting dose.
- Euthyrox has a long duration of action with a serum half‑life of about 7 days in euthyroid adults, allowing once‑daily dosing and steady state/maximum effect over 4–6 weeks of consistent therapy.
- Avoid excessive alcohol; while moderate alcohol does not directly contraindicate levothyroxine, heavy drinking and liver disease can affect overall health and hormone metabolism, so discuss alcohol use with your clinician.
- The most common side effects reflect over‑replacement and include palpitations, nervousness, tremor, insomnia and increased appetite (symptoms similar to hyperthyroidism).
- Would you like to try Euthyrox without a prescription?
Basic Euthyrox information
- INN (international nonproprietary name): Levothyroxine sodium.
- Brand names available in the United Kingdom: Eltroxin, Euthyrox, Levothyroxine.
- ATC code: H03AA01.
- Forms and strengths: oral tablets commonly in strengths from 25 to 300 mcg (examples include 25, 50, 75, 88, 100, 112, 125, 137, 150, 175, 200, 300 mcg), and oral liquid formulations.
- Manufacturers in the United Kingdom: Merck KGaA supplies Euthyrox; generic manufacturers also supply levothyroxine tablets.
- Registration status in the United Kingdom: Prescription-only medicine (POM).
- OTC / Rx classification: Prescription only (Rx).
- Standard dosages per condition: Initial adult dosing commonly 25–50 mcg once daily with titration every 4–6 weeks; full replacement around 1.6 mcg/kg/day.
- Dosage adjustments: Neonates and children use weight-based dosing (neonates may require 10–15 mcg/kg/day for severe disease); elderly often start 12.5–25 mcg/day.
- Storage and transport: Store at 20–25°C, protected from light, moisture and heat; transport in original packaging.
- Absolute contraindications: Untreated thyrotoxicosis, untreated adrenal insufficiency, acute myocardial infarction, hypersensitivity to levothyroxine or excipients.
- Missed dose / overdose advice: Take missed dose as soon as remembered unless near next dose; never double dose; overdose may cause chest pain, rapid heartbeat and tremor and requires urgent care.
Legal status and availability in the UK
Levothyroxine is a prescription‑only medicine (POM) in the UK.
In our online pharmacy, Euthyrox is available without a prescription, with discreet delivery to the United Kingdom in 9–21 days.
Clinical effectiveness in the UK
Patients want to know whether levothyroxine works as expected in NHS practice.
Levothyroxine sodium remains the standard replacement for primary hypothyroidism across NHS primary and secondary care.
Most patients achieve good biochemical control, with TSH within target, when prescribing is consistent by brand or generic.
Variability in TSH control tends to increase after formulation switches without monitoring.
Improvements commonly include more energy, stabilised weight and clearer cognition, though a subset have persistent symptoms despite normal TSH and need endocrine review.
TSH checks are recommended every 4–6 weeks during titration and then annually or as clinically indicated.
Community pharmacists are central to counselling on empty‑stomach administration and checking for interactions.
Indications and expanded uses
Patients and clinicians often ask which uses are approved and which are off‑label.
- Approved indications: primary and secondary hypothyroidism, myxoedema management, and adjunctive therapy in thyroid cancer when TSH suppression is indicated.
- Common off‑label practices: use of liquid levothyroxine in malabsorption (coeliac disease, post‑bariatric) or with polypharmacy affecting absorption.
- Off‑label considerations: low‑dose trials for subclinical hypothyroidism in symptomatic patients with raised TSH are used cautiously in some NHS and private clinics.
Checklist for clinicians:
- Confirm licensed indications are met and document baseline TSH.
- Consider liquid levothyroxine where absorption is likely impaired.
- Exclude untreated adrenal insufficiency or thyrotoxicosis before starting replacement.
- Titrate dose every 4–6 weeks based on TSH.
Composition and brand landscape
People often ask which brand to pick and whether generics differ.
Active ingredient across products is levothyroxine sodium (INN) and the ATC classification is H03AA01.
UK brands and generics include Eltroxin, Euthyrox and various levothyroxine generics supplied by local manufacturers and Merck KGaA.
Tablets are commonly colour‑coded by strength to reduce dispensing errors and common NHS strengths run from 25 to 150 mcg in routine supply.
Many prescribers favour naming a brand or requesting ‘do not substitute’ where patients are sensitive to formulation changes to preserve stable TSH control.
| Brand / generic | Manufacturer | Typical pack sizes |
|---|---|---|
| Eltroxin | Local suppliers | Varies by strength; standard tablet packs |
| Euthyrox | Merck KGaA | Blister packs and bottles |
| Levothyroxine generics | Local generic manufacturers | Various pack sizes |
Contraindications and special precautions
Patients with heart disease or other conditions need tailored advice before starting levothyroxine.
- Absolute contraindications: Untreated thyrotoxicosis, untreated adrenal insufficiency, acute myocardial infarction, hypersensitivity to levothyroxine or excipients.
- High‑risk groups: Elderly patients, those with cardiovascular disease, patients with osteoporosis risk, and those with diabetes.
- Pregnancy: Dose adjustments are commonly required and closer monitoring is indicated.
Short decision tree for GPs:
- Screen for adrenal insufficiency and thyrotoxicosis before initiating levothyroxine.
- If elderly or with CVD start 12.5–25 mcg/day and monitor ECG if rapid titration considered.
- For long‑term high doses arrange periodic bone health review.
Dosage guidelines
Patients want clear practical dosing by group and what to do if doses are missed.
Adults: Initial doses often 25–50 mcg daily with titration every 4–6 weeks by TSH; full replacement typically around 1.6 mcg/kg/day.
Elderly / cardiovascular disease: Start lower (12.5–25 mcg/day) with slower titration and clinical monitoring.
Children and neonates: Weight‑based dosing applies; neonates with severe disease may require 10–15 mcg/kg/day.
Pregnancy: Expect dose increases and trimesterly monitoring is common practice.
Secondary hypothyroidism: Monitor free T4 rather than TSH and individualise therapy.
Missed dose advice: take as soon as remembered unless close to next dose; do not double up.
| Population | Typical starting dose |
|---|---|
| Adults (general) | 25–50 mcg once daily; titrate to 1.6 mcg/kg/day |
| Elderly / CVD | 12.5–25 mcg once daily |
| Neonates (severe) | 10–15 mcg/kg/day |
| Pregnancy | Increase from baseline as required; monitor each trimester |
Interactions overview
Many patients worry about food and medicines that reduce levothyroxine absorption.
Key food interactions: take levothyroxine on an empty stomach 30–60 minutes before breakfast; milk, soy, high‑fibre meals, coffee and strong tea can reduce absorption.
Common drug interactions: calcium, iron supplements, aluminium‑containing antacids, sucralfate, bile acid sequestrants and some proton‑pump inhibitors can impair absorption and should be separated by at least four hours where possible.
Enzyme inducers: carbamazepine and rifampicin may increase levothyroxine requirements by increasing metabolism.
Brand consistency: pharmacists should counsel on consistent brand use and tablet appearance.
| Interacting agent | Effect | Management tip |
|---|---|---|
| Calcium / iron | Reduced absorption | Separate doses by ≥4 hours |
| Antacids / sucralfate | Bind levothyroxine | Delay administration or separate dosing |
| Carbamazepine / rifampicin | Increase metabolism | Monitor TSH and increase dose if needed |
Comparable medicines and prescribing preferences
Patients sometimes ask about T3 or combination therapy when symptoms persist.
Alternatives include liothyronine (T3) and combination T4/T3 therapy, which are used selectively and usually after endocrinology referral.
Desiccated thyroid extract is not recommended in the NHS due to variable potency and is not licensed in the UK.
| Medicine | Mechanism | Indications | Key risks |
|---|---|---|---|
| Levothyroxine | T4 replacement | Primary replacement therapy | Overtreatment: cardiac and bone risks |
| Liothyronine | T3 replacement | Selected cases; short‑acting | Arrhythmia, bone loss risk if misused |
| Combination T4/T3 | Both hormones | Selected symptomatic patients after specialist review | Increased adverse effects; limited robust evidence of superiority |
Prescribing preference in primary care: prioritise consistent formulation, clear monitoring plans and small incremental adjustments to avoid swings in TSH and symptoms.
Frequently asked questions
1. When should I take Euthyrox/levothyroxine?
Take it on an empty stomach 30–60 minutes before breakfast for best absorption, and separate from calcium or iron by at least four hours.
2. What if my TSH is normal but I still feel unwell?
Discuss with your GP or an endocrinologist to check adherence, timing of blood tests, recent brand switches and other health issues; consider PROMs assessment or specialist review.
3. Can I switch brands or use generics?
Consistency is important; if a switch is necessary check TSH 6–8 weeks afterwards and consult your pharmacist or GP about monitoring.
4. Are there pregnancy considerations?
Yes, doses often need increasing in pregnancy and more frequent TSH monitoring is standard practice.
Guidelines for proper use
Pharmacist counselling should be practical, clear and documented on the patient medication record.
Stepwise counselling script:
- Confirm the product is levothyroxine sodium (INN) and note the brand supplied.
- Advise taking the tablet 30–60 minutes before breakfast and to keep to the same brand where possible.
- Warn about interactions with calcium, iron and certain antacids and recommend ≥4‑hour separation.
- Explain missed‑dose policy: take if not near the next dose and never double up.
- Highlight monitoring milestones: baseline TSH, checks every 6–8 weeks during titration, then annually or as clinically required.
Monitoring milestones:
- Baseline TSH before or at initiation where possible.
- TSH 6–8 weeks after any dose or formulation change.
- Annual review once stable, more often in pregnancy or with interacting medicines.
Provide printed patient leaflets, refer to PROMs when available and encourage reporting side effects via MHRA Yellow Card if needed.
Delivery across the United Kingdom
| City | Region | Delivery Time |
|---|---|---|
| London | England | 9–21 days |
| Birmingham | England | 9–21 days |
| Manchester | England | 9–21 days |
| Glasgow | Scotland | 9–21 days |
| Edinburgh | Scotland | 9–21 days |
| Leeds | England | 9–21 days |
| Liverpool | England | 9–21 days |
| Bristol | England | 9–21 days |
| Sheffield | England | 9–21 days |
| Newcastle Upon Tyne | England | 9–21 days |
| Nottingham | England | 9–21 days |
| Leicester | England | 9–21 days |
| Coventry | England | 9–21 days |
| Cardiff | Wales | 9–21 days |
| Belfast | Northern Ireland | 9–21 days |



