
Medrol
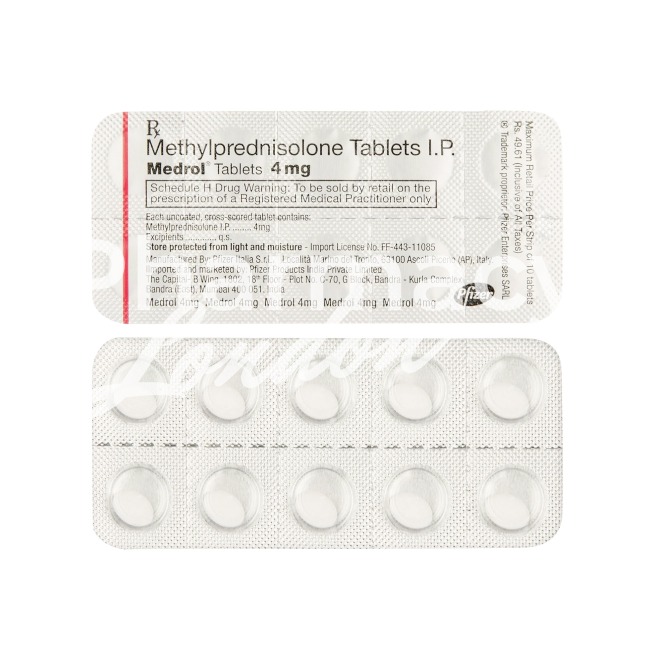
In brief
- In our pharmacy, you can buy Medrol without a prescription, with delivery in 9–21 days throughout the United Kingdom. Discreet and anonymous packaging.
- Medrol (methylprednisolone) is used to treat inflammatory and autoimmune conditions (such as rheumatoid arthritis, severe allergies, asthma exacerbations, inflammatory bowel disease and multiple sclerosis relapses) and as an immunosuppressant; it is a glucocorticoid that binds glucocorticoid receptors to reduce inflammation and suppress immune responses.
- Usual dosages vary by indication: oral maintenance or anti-inflammatory dosing commonly 4–48 mg per day (divided or as a single morning dose); acute courses often 24–48 mg/day with tapering; adrenal replacement 4–12 mg/day; severe relapses may require high IV doses (e.g. 500–1000 mg/day for 3–5 days). Children are dosed by weight (commonly 0.5–1.7 mg/kg/day).
- Forms of administration include oral tablets (2, 4, 8, 16, 32 mg), injectable formulations for IV use (sodium succinate), and intramuscular suspensions (Depo-Medrol) for longer-acting effect.
- Onset of effect: oral Medrol usually begins to relieve symptoms within 1–4 hours (systemic effects may be noticeable within hours); IV administration produces a faster onset (minutes to hours) for acute control.
- Duration of action: methylprednisolone is an intermediate-acting corticosteroid; biological effects typically last about 18–36 hours, which is why once-daily dosing is common for many indications.
- Alcohol warning: avoid excessive alcohol while taking Medrol—alcohol can increase the risk of gastrointestinal irritation/bleeding and may worsen hyperglycaemia and mood effects; discuss alcohol use with a clinician if on long-term therapy.
- The most common side effect is increased appetite (often leading to weight gain); other frequent effects include insomnia, mood changes, elevated blood glucose, indigestion and sodium retention.
- Would you like to try Medrol without a prescription?
Basic Medrol information
- INN (international nonproprietary name): Methylprednisolone.
- Brand names available in the United Kingdom: Medrol, Solu‑Medrol, Depo‑Medrol.
- ATC code: H02AB04.
- Forms and strengths: tablets 2 mg, 4 mg, 8 mg, 16 mg, 32 mg; injectable vials 40 mg, 125 mg, 500 mg, 1 g (sodium succinate); IM suspension 40 mg/ml and 80 mg/ml (Depo‑Medrol).
- Manufacturer: Pfizer.
- Registration status in the United Kingdom: prescription-only medicine (POM).
- OTC / Rx classification: Prescription-only medicine (Rx).
Legal status and availability in the UK
In our online pharmacy, Medrol is available without a prescription, with discreet delivery to the United Kingdom in 9–21 days.
Clinical effectiveness in the UK
Patients commonly ask how quickly they will feel better after starting methylprednisolone.
| Indication | Typical dose | Expected timeline |
|---|---|---|
| Asthma / acute allergy | 24–48mg/day orally | Improvement in 24–72 hours |
| Rheumatological flares | 4–48mg/day orally | Pain relief in 24–72 hours |
| Severe autoimmune relapse (secondary care) | IV 500–1000mg/day pulse | Clinical response within days |
Effectiveness must be balanced against adverse effects.
Long-term use requires closer glucose monitoring and increases the risk of osteoporosis.
The lowest effective dose is recommended, with frequent review for steroid‑related complications.
Indications and expanded uses
Patients want to know what Medrol is licensed for and where off‑label use may occur.
- Acute asthma exacerbation
- Oral 24–48mg/day; community and inpatient use depending on severity.
- Severe allergic reactions
- Oral 24–48mg/day or IV in hospital for severe cases.
- Rheumatoid arthritis and other inflammatory flares
- Oral 4–48mg/day; short courses or maintenance as clinician decides.
- Inflammatory bowel disease flares
- Oral regimens tailored to severity; monitored in secondary care when prolonged.
- Neurological relapses (severe)
- IV pulse therapy 500–1000mg/day for 3–5 days in hospital.
| Indication | Typical NHS regimen | Monitoring needs |
|---|---|---|
| Asthma | Oral 24–48mg/day short course | Observe glucose in diabetics; GP follow‑up |
| Rheumatology flares | 4–48mg/day oral | Bone health review for prolonged use |
| MS relapse | IV 500–1000mg/day for 3–5 days | Secondary‑care monitoring for infection and mood changes |
MHRA classifies methylprednisolone as prescription‑only.
Off‑label use in secondary care requires documented rationale and informed consent in NHS or private settings.
Composition and brand landscape
People often ask whether branded Medrol differs from generics in effect.
The active pharmaceutical ingredient is methylprednisolone (INN).
Brand names include Medrol, Solu‑Medrol (injectable) and Depo‑Medrol (suspension).
Generic methylprednisolone is also made by manufacturers such as Teva, Mylan and Actavis.
| Brand | Form | Typical strengths | Manufacturer |
|---|---|---|---|
| Medrol | Tablet | 4 mg, 16 mg | Pfizer (originator) |
| Solu‑Medrol | Injectable (sodium succinate) | 40 mg, 125 mg, 500 mg, 1 g | Pfizer |
| Depo‑Medrol | IM suspension | 40 mg/ml, 80 mg/ml | Pfizer |
| Generic methylprednisolone | Tablets / vials | 2–32mg tablets; injectable vials | Teva, Mylan, Actavis |
Tablets are stored at 15–30°C and injectables per label with some requiring refrigeration.
Contraindications and special precautions
Patients commonly ask what makes methylprednisolone unsafe for some people.
Absolute contraindications include systemic fungal infections and known hypersensitivity to methylprednisolone or excipients.
Avoid live attenuated vaccines during high‑dose therapy.
- Relative contraindications requiring active management include diabetes, hypertension, peptic ulcer disease, osteoporosis, glaucoma, latent infections (for example TB or herpes) and psychiatric history.
- Common side effects to warn patients about are increased appetite, weight gain, insomnia, mood changes and elevated blood sugar.
Patient‑facing precautions: avoid live vaccines while immunosuppressed, notify the prescriber before elective surgery and report signs of infection promptly.
Daily life precautions include cautious driving if experiencing dizziness, limiting alcohol to reduce GI risk and seeking advice if mood or sleep are affected.
Baseline assessments for prolonged therapy include blood pressure, blood glucose and bone health checks.
Dosage guidelines
One common question is how dosage varies between conditions and age groups.
Dosing depends on indication and patient factors.
Typical oral dosing ranges from 4–48mg/day for inflammatory disease.
Acute allergy or asthma often uses 24–48mg/day with a taper for short courses.
Maintenance replacement for adrenal insufficiency is approximately 4–12mg/day.
| Indication | Typical oral dose | Duration | Notes |
|---|---|---|---|
| Acute flare (arthritis) | 4–48mg/day | 5–14 days or longer if needed | Use lowest effective dose; monitor bone health if prolonged |
| Asthma / allergy | 24–48mg/day | Short course, then taper | Community management often sufficient for ≤14 days |
| Severe autoimmune relapse | IV 500–1000mg/day | 3–5 days | Secondary‑care administration and monitoring required |
- Paediatric adjustments
- Dosage is weight based (commonly 0.5–1.7mg/kg/day) and follows NHS paediatric protocols.
- Elderly
- Use the lowest effective dose with close monitoring for osteoporosis and glucose disruption.
Missed dose advice: take as soon as remembered unless near the next dose; do not double up.
Overdose is rarely fatal but may cause Cushingoid features and electrolyte imbalance and requires urgent medical attention.
Interactions overview
Pharmacists need quick checklists for drug interactions when dispensing Medrol.
Key interactions include enzyme inducers such as rifampicin and phenytoin which can lower steroid levels.
CYP3A4 inhibitors may raise systemic methylprednisolone exposure.
Concomitant NSAID use increases gastrointestinal bleeding risk.
Warfarin monitoring can be affected and dose adjustments may be needed.
Alcohol can exacerbate indigestion and should be limited while taking corticosteroid tablets.
For people on glucose‑lowering treatments anticipate closer glucose monitoring and temporary medication changes during steroid therapy.
Always check electronic interaction alerts via NHS prescribing systems before issuing treatment.
Comparable medicines and preferences
Clinicians choose between steroids based on potency, duration and patient comorbidity.
| Drug | Relative potency | Typical NHS use | Key advantage / disadvantage |
|---|---|---|---|
| Methylprednisolone (Medrol) | Intermediate | Oral and IV for flares and pulse therapy | Useful for IV pulse therapy |
| Prednisolone | Similar (clinically preferred oral in UK) | Widespread oral use in primary care | Easy oral dosing; often first‑line in community |
| Dexamethasone | Higher potency per mg | Specific protocols and antiemetic use | Longer‑acting; higher adrenal suppression risk per dose |
| Hydrocortisone | Lower | Adrenal replacement therapy | Preferred for replacement rather than anti‑inflammatory effect |
Choice is driven by local formulary, clinician preference and patient comorbidity such as diabetes sensitivity.
Secondary care often prefers IV methylprednisolone pulse therapy for severe relapses, while primary care commonly uses prednisolone for oral management.
Frequently asked questions
Will Medrol make my blood sugar rise?
Yes, elevated blood sugar is a recognised moderate effect and patients with diabetes will need closer glucose monitoring and may require treatment adjustments.
Can I stop suddenly after a short course?
Short courses (generally 14 days or less) often do not require tapering, but longer or high‑dose therapy needs a planned taper to reduce risk of adrenal insufficiency.
Is methylprednisolone safe in pregnancy?
Use only if the expected benefit justifies the potential risk; consult the obstetric team and note that live vaccinations for the neonate may be impacted if high doses were used close to delivery.
How should I store tablets and injectables?
Store tablets at 15–30°C in a dry place.
Store injectables as per the product label, with some formulations requiring refrigeration.
Where should I report side effects?
Report suspected adverse reactions via the MHRA Yellow Card scheme and seek urgent advice from NHS 111 or a pharmacist for worrying symptoms.
Guidelines for proper use
Pharmacist counselling should begin with confirming the indication and dose on the prescription.
Explain timing: a single morning dose is often recommended to mimic the natural cortisol rhythm.
Warn about common side effects such as increased appetite, sleep disturbance and mood changes.
Advise on infection risk and give clear guidance on vaccine timing, especially live vaccines.
Provide a written taper plan when appropriate and recommend baseline monitoring for prolonged therapy: blood pressure, blood glucose and bone assessment.
| Monitoring action | Recommended timeline |
|---|---|
| Baseline BP / glucose | Prior to prolonged therapy and periodically thereafter |
| Bone health assessment | If therapy extends beyond 3 months or cumulative dose is high |
| Mood and sleep review | Within 1–2 weeks of starting higher doses |
For outpatient IV or high‑dose courses ensure clear handover to the GP and community pharmacist with documented follow‑up.
Encourage MHRA Yellow Card reporting for any suspected adverse reactions and use NHS electronic checks for drug interactions.
Delivery across the United Kingdom
| City | Region | Delivery Time |
|---|---|---|
| London | England | 9–21 days |
| Birmingham | England | 9–21 days |
| Manchester | England | 9–21 days |
| Glasgow | Scotland | 9–21 days |
| Edinburgh | Scotland | 9–21 days |
| Leeds | England | 9–21 days |
| Liverpool | England | 9–21 days |
| Bristol | England | 9–21 days |
| Sheffield | England | 9–21 days |
| Newcastle Upon Tyne | England | 9–21 days |
| Belfast | Northern Ireland | 9–21 days |
| Cardiff | Wales | 9–21 days |
| Nottingham | England | 9–21 days |
| Coventry | England | 9–21 days |
| Leicester | England | 9–21 days |



