
Tolvaptan
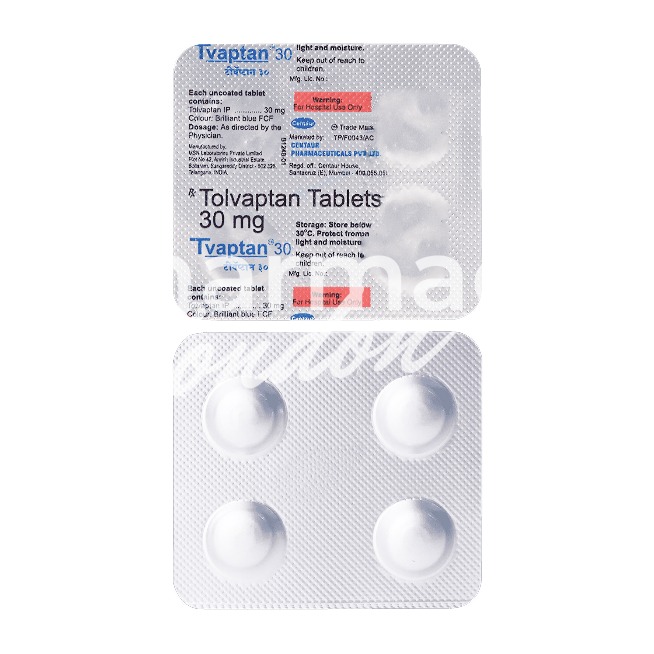
In brief
- In the UK, tolvaptan is a prescription-only medicine supplied via pharmacies and specialist clinics.
- Tolvaptan is used to treat hyponatraemia secondary to SIADH and to slow kidney decline in adults with autosomal dominant polycystic kidney disease (ADPKD). It is a selective vasopressin V2 receptor antagonist (an aquaretic) that increases free water excretion and, in ADPKD, reduces cAMP-mediated cyst growth.
- Usual doses: for ADPKD start 45 mg in the morning plus 15 mg in the afternoon, titrating as tolerated up to 90/30 mg daily; for hyponatraemia start 15 mg once daily and titrate as needed up to 60 mg/day. Not licensed for children; elderly dosing should be cautious.
- Oral administration as film-coated tablets (available in 15 mg, 30 mg, 45 mg, 60 mg and 90 mg strengths).
- Onset: aquaretic effects and increased urine output typically begin within 1–4 hours, with serum sodium commonly starting to rise within 6–24 hours of initiation.
- Duration of action: clinical effects persist approximately 12–24 hours (half-life around 12 hours), which supports once-daily dosing for hyponatraemia and split dosing regimens for ADPKD as prescribed.
- Alcohol warning: avoid excessive alcohol while taking tolvaptan as it may worsen dehydration and increase risk of adverse effects; alcohol may also compound liver and renal risks—discuss alcohol use with your prescriber.
- The most common side effect is thirst (dry mouth and increased urination are also frequent).
- Would you like to try tolvaptan without a prescription?
Basic tolvaptan information
- INN (international nonproprietary name): tolvaptan.
- Brand names available in the United Kingdom: Jinarc; Tolvaptan Accord.
- ATC code: C03XA01.
- Forms and strengths: oral tablets 15 mg, 30 mg, 45 mg, 60 mg, 90 mg in blister packs.
- Manufacturers in the United Kingdom: Accord Healthcare; Otsuka Pharmaceutical Co., Ltd.
- Registration status in the United Kingdom: Registered with MHRA; prescription-only (Rx).
- OTC / Rx classification: Prescription-only (Rx), not over-the-counter.
Legal status and availability in the UK
In our online pharmacy, tolvaptan is available without a prescription, with discreet delivery to the United Kingdom in 9–21 days.
Clinical effectiveness in the United Kingdom
People want to know what happens to kidney function once they start treatment.
In UK renal centres, tolvaptan is prescribed within specialist ADPKD pathways and started by nephrologists after risk–benefit assessment.
Treatment slows renal decline for eligible adults with rapidly progressing disease when adherence is maintained.
Aquaresis symptoms (thirst and frequent urination) can affect daily life and sleep.
Short‑term use in hospital for euvolaemic hyponatraemia gives reliable sodium correction when started with inpatient monitoring and a clear fluid plan.
Multidisciplinary implementation includes nephrologist assessment, pharmacist counselling, and GP or community follow‑up for prescriptions and monitoring arrangements.
- Outcomes: slowed eGFR decline and reduced TKV growth.
- Patient symptoms versus adherence: common aquaresis can lead to early discontinuation.
Indications and reported uses
Patients often ask whether tolvaptan is only for polycystic kidneys.
MHRA‑registered indications: use in adults with autosomal dominant polycystic kidney disease to slow renal progression, and treatment of hyponatraemia secondary to SIADH.
Licensed initiation and titration schedules for ADPKD and regimens for hyponatraemia are described in product information and specialist protocols.
Off‑label use is uncommon in UK renal practice and is specialist‑led.
Prescription‑only status and the requirement for baseline and ongoing hepatic monitoring restrict routine community prescribing.
- Licensed uses: ADPKD disease modification in adults; hyponatraemia secondary to SIADH.
- Reported off‑label patterns: rare and specialist‑led; not routine in community practice.
Composition and brand landscape
People ask whether different packs contain the same drug.
The active ingredient is tolvaptan, a selective vasopressin V2 receptor antagonist, classified under ATC code C03XA01.
In the UK the main brands are Jinarc (originator, Otsuka) and Tolvaptan Accord (generic supply via Accord Healthcare).
Tablets are commonly available in 15mg, 30mg and 45mg strengths in the UK.
| Brand | Manufacturer | Available strengths | Typical NHS supply route |
|---|---|---|---|
| Jinarc | Otsuka | 15mg, 30mg, 45mg | Hospital and specialist clinic supplies; community dispensing on prescription |
| Tolvaptan Accord | Accord Healthcare | 15mg, 30mg, 45mg | Community pharmacy dispensing on prescription |
Pharmacists should note that INN dosing is identical irrespective of brand and that packaging is blister style labelled Rx only.
Contraindications and special precautions
Patients ask who should not take tolvaptan.
Absolute contraindications include severe hepatic impairment, hypovolaemia, anuria and hypersensitivity to tolvaptan or excipients.
Special precautions include avoiding use in significant liver disease because of the risk of serious hepatic injury.
Elderly patients require lower starting doses and closer monitoring for dehydration and sodium shifts.
Pregnancy and breastfeeding safety are unestablished and tolvaptan is generally avoided in these groups.
Daily‑life restrictions are practical: expect increased diuresis, plan fluid intake, take doses to minimise nocturia and be cautious with driving if sleep is disrupted.
Alcohol should be discussed because it can worsen dehydration and potentially add hepatic stress.
- Checklist for contraindications: severe liver impairment; hypovolaemia or anuria; known hypersensitivity.
- What to tell patients: plan toilet access, carry water, adjust dose timing to reduce night‑time waking, avoid heavy drinking.
Dosage guidelines and monitoring
People want clear rules about starting, titration and blood tests.
For ADPKD, the licensed initiation is 45mg in the morning and 15mg in the afternoon, with titration up to 90mg/30mg as tolerated.
For hyponatraemia the usual starting dose is 15mg once daily with titration as needed up to a maximum of 60mg per day.
Tolvaptan is not licensed for children; safety is not established.
Start elderly patients at lower doses and monitor for orthostatic effects and hydration status.
Baseline assessments should include liver function tests, serum sodium, eGFR and volume status.
Liver function monitoring is frequent early in treatment according to specialist protocols because of hepatic risk.
| Regimen | Starting dose | Titration steps | Monitoring schedule |
|---|---|---|---|
| ADPKD | 45mg morning, 15mg afternoon | Increase stepwise to 90mg/30mg as tolerated | Baseline LFTs, Na, eGFR; frequent early LFT checks per protocol |
| Hyponatraemia | 15mg once daily | Titrate up to 60mg/day if required | Monitor serum sodium regularly during treatment |
Missed doses should be taken the same day if remembered; avoid doubling up the next day.
In overdose, seek urgent medical attention because of dehydration and hypernatraemia risks.
Interactions overview
Patients and clinicians ask which medicines to avoid with tolvaptan.
Tolvaptan is metabolised by CYP3A4, so strong CYP3A4 inhibitors increase exposure and are discouraged.
CYP3A4 inducers may reduce efficacy and should be reviewed before starting tolvaptan.
Grapefruit juice should be avoided because it increases tolvaptan levels; alcohol can worsen dehydration and hepatic stress.
Caffeinated drinks may increase urinary frequency and therefore add to aquaresis, but are not formally contraindicated.
- Key interaction classes: strong CYP3A4 inhibitors; CYP3A4 inducers; review QT‑prolonging agents as part of a complete medication review.
Hepatic adverse events are the main safety signal; suspected reactions should be reported via the Yellow Card scheme.
Comparable medicines and NHS preferences
Patients often ask whether there is another drug that does what tolvaptan does.
There are limited direct pharmacological alternatives for ADPKD that slow disease progression.
Lixivaptan remains investigational and is not established in UK practice.
Old‑style diuretics such as furosemide or spironolactone do not modify ADPKD progression and are used for symptomatic control only.
The NHS tends to prefer tolvaptan for eligible ADPKD patients where the expected benefit outweighs hepatic risk and tolerability issues.
- Pros/cons checklist for clinicians: efficacy for disease modification versus hepatic monitoring burden and tolerability; oral route is convenient but requires specialist oversight.
Frequently asked questions
Will tolvaptan stop my kidney disease?
Tolvaptan slows progression measured by TKV increase and eGFR decline in selected adults but is not a cure and continued monitoring is required.
What side effects should I expect?
Common side effects are thirst, dry mouth, increased urination, nausea and fatigue; report jaundice or abdominal pain urgently because of liver risk.
How often are blood tests needed?
Baseline LFTs, serum sodium and eGFR are required, then frequent early LFT checks according to the specialist programme with periodic monitoring long term.
Can I get it from a community pharmacy?
It is available only on prescription; initiation typically happens in hospital or specialist clinics while community pharmacies dispense on a validated prescription with verification of monitoring arrangements.
NHS.uk and local renal‑unit contacts are primary sources for patient information and monitoring arrangements.
Guidelines for proper use and pharmacist counselling
Patients want to know exactly what their pharmacist will tell them.
Counselling should cover indication, expected benefits, common side effects and the need for liver function and sodium monitoring.
Explain the dosing schedule: the ADPKD 45/15 titration and the hyponatraemia 15–60mg regimen, and provide clear missed‑dose and overdose advice.
Use a patient‑centred approach when setting dose timing to minimise nocturia and discuss fluid balance rather than encouraging unrestricted intake.
Advise on alcohol moderation and confirm enrolment in local monitoring protocols before dispensing long runs.
Document counselling in the pharmacy record and coordinate with the GP and nephrology for monitoring results and repeat prescriptions.
- Monitoring checkpoints: baseline LFTs/Na/eGFR, early frequent LFTs, regular sodium checks during hyponatraemia treatment, periodic long‑term LFT surveillance.
- Counselling checklist for pharmacists: indication, dose, side effects, monitoring schedule, missed dose rules, when to seek urgent care.
Delivery across the United Kingdom
| City | Region | Delivery Time |
|---|---|---|
| London | England | 9–21 days |
| Birmingham | England | 9–21 days |
| Manchester | England | 9–21 days |
| Glasgow | Scotland | 9–21 days |
| Edinburgh | Scotland | 9–21 days |
| Bristol | England | 9–21 days |
| Leeds | England | 9–21 days |
| Cardiff | Wales | 9–21 days |
| Belfast | Northern Ireland | 9–21 days |
| Newcastle | England | 9–21 days |
| Southampton | England | 9–21 days |
| Nottingham | England | 9–21 days |
| Exeter | England | 9–21 days |
| Norwich | England | 9–21 days |



